Related Experiment Video
Updated: Dec 12, 2025

Stereo-Electro-Encephalo-Graphy SEEG With Robotic Assistance in the Presurgical Evaluation of Medical Refractory Epilepsy: A Technical Note
Published on: June 13, 2016
Robotic Stereotactic Assistance (ROSA) for Pediatric Epilepsy: A Single-Center Experience of 23 Consecutive Cases
Jonathon H Nelson1, Samantha L Brackett1, Chima O Oluigbo2
1Division of Anesthesiology, Pain and Perioperative Medicine, Children's National Hospital, The George Washington University School of Medicine & Health Sciences, Washington, DC 20010, USA.

Abstract:
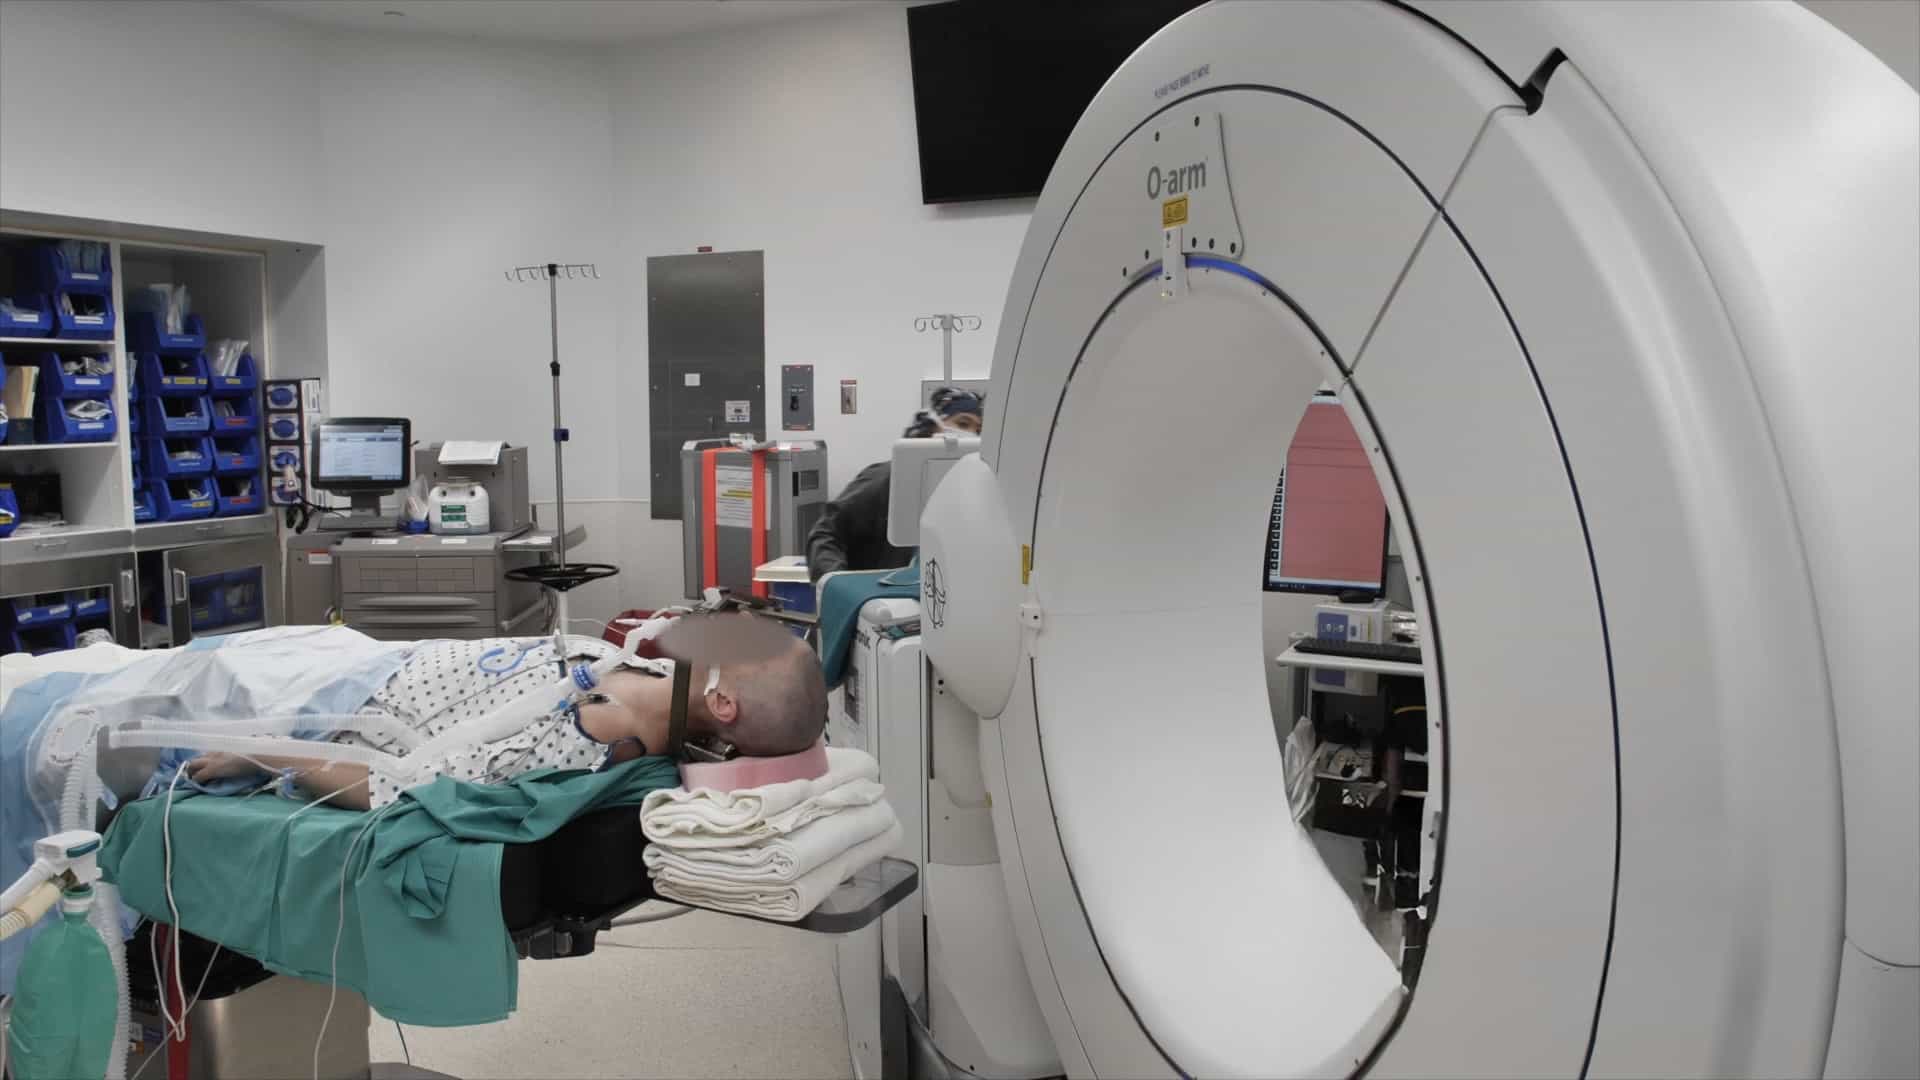
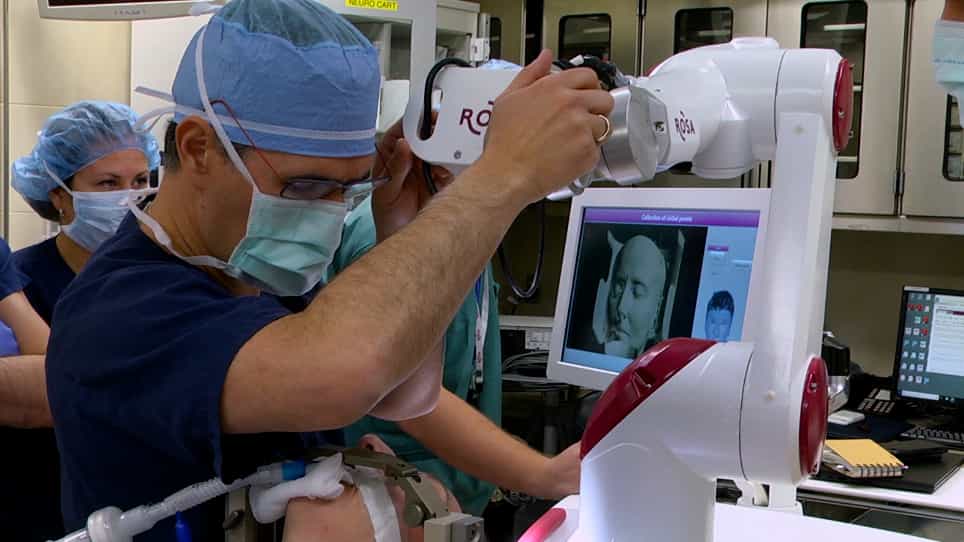
Robotic assisted neurosurgery has become increasingly utilized for its high degree of precision and minimally invasive approach. Robotic stereotactic assistance (ROSA®) for neurosurgery has been infrequently reported in the pediatric population. The goal of this case series was to describe the clinical experience, anesthetic and operative management, and treatment outcomes for pediatric patients with intractable epilepsy undergoing ROSA® neurosurgery at a single-center institution. Patients who underwent implantation of stereoelectroencephalography (SEEG) leads for intractable epilepsy with ROSA® were retrospectively evaluated between August 2016 and June 2018. Demographics, perioperative management details, complications, and preliminary seizure outcomes after resective or ablative surgery were reviewed. Nineteen children who underwent 23 ROSA® procedures for SEEG implantation were included in the study. Mean operative time was 148 min. Eleven patients had subsequent resective or ablative surgery, and ROSA® was used to assist with laser probe insertion in five patients for seizure foci ablation. In total, 148 SEEG electrodes were placed without any perioperative complications. ROSA® is minimally invasive, provides superior accuracy for electrode placement, and requires less time than traditional surgical approaches for brain mapping. This emerging technology may improve the perioperative outcomes for pediatric patients with intractable epilepsy since large craniotomies are avoided; however, long-term follow-up studies are needed.