Related Experiment Video
Updated: Dec 12, 2025
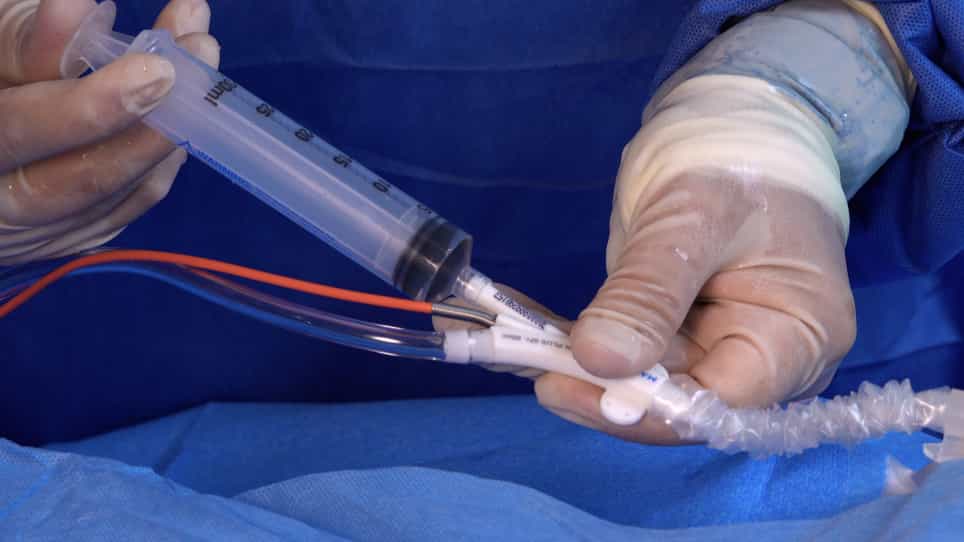

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Optimum Blood Pressure in Patients With Shock After Acute Myocardial Infarction and Cardiac Arrest
Koen Ameloot1, Pekka Jakkula2, Johanna Hästbacka2
1Department of Cardiology, Ziekenhuis Oost-Limburg, Genk, Belgium; Department of Cardiology, University Hospitals Leuven, Leuven, Belgium; Faculty of Medicine and Life Sciences, University Hasselt, Diepenbeek, Belgium.

Background:
In patients with shock after acute myocardial infarction (AMI), the optimal level of pharmacologic support is unknown. Whereas higher doses may increase myocardial oxygen consumption and induce arrhythmias, diastolic hypotension may reduce coronary perfusion and increase infarct size.
Objectives:
This study aimed to determine the optimal mean arterial pressure (MAP) in patients with AMI and shock after cardiac arrest.
Methods:
This study used patient-level pooled analysis of post-cardiac arrest patients with shock after AMI randomized in the Neuroprotect (Neuroprotective Goal Directed Hemodynamic Optimization in Post-cardiac Arrest Patients; NCT02541591) and COMACARE (Carbon Dioxide, Oxygen and Mean Arterial Pressure After Cardiac Arrest and Resuscitation; NCT02698917) trials who were randomized to MAP 65 mm Hg or MAP 80/85 to 100 mm Hg targets during the first 36 h after admission. The primary endpoint was the area under the 72-h high-sensitivity troponin-T curve.
Results:
Of 235 patients originally randomized, 120 patients had AMI with shock. Patients assigned to the higher MAP target (n = 58) received higher doses of norepinephrine (p = 0.004) and dobutamine (p = 0.01) and reached higher MAPs (86 ± 9 mm Hg vs. 72 ± 10 mm Hg, p < 0.001). Whereas admission hemodynamics and angiographic findings were all well-balanced and revascularization was performed equally effective, the area under the 72-h high-sensitivity troponin-T curve was lower in patients assigned to the higher MAP target (median: 1.14 μg.72 h/l [interquartile range: 0.35 to 2.31 μg.72 h/l] vs. median: 1.56 μg.72 h/l [interquartile range: 0.61 to 4.72 μg. 72 h/l]; p = 0.04). Additional pharmacologic support did not increase the risk of a new cardiac arrest (p = 0.88) or atrial fibrillation (p = 0.94). Survival with good neurologic outcome at 180 days was not different between both groups (64% vs. 53%, odds ratio: 1.55; 95% confidence interval: 0.74 to 3.22).
Conclusions:
In post-cardiac arrest patients with shock after AMI, targeting MAP between 80/85 and 100 mm Hg with additional use of inotropes and vasopressors was associated with smaller myocardial injury.


Related Concept Videos
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:24
Blood Pressure
 01:30
Blood Pressure
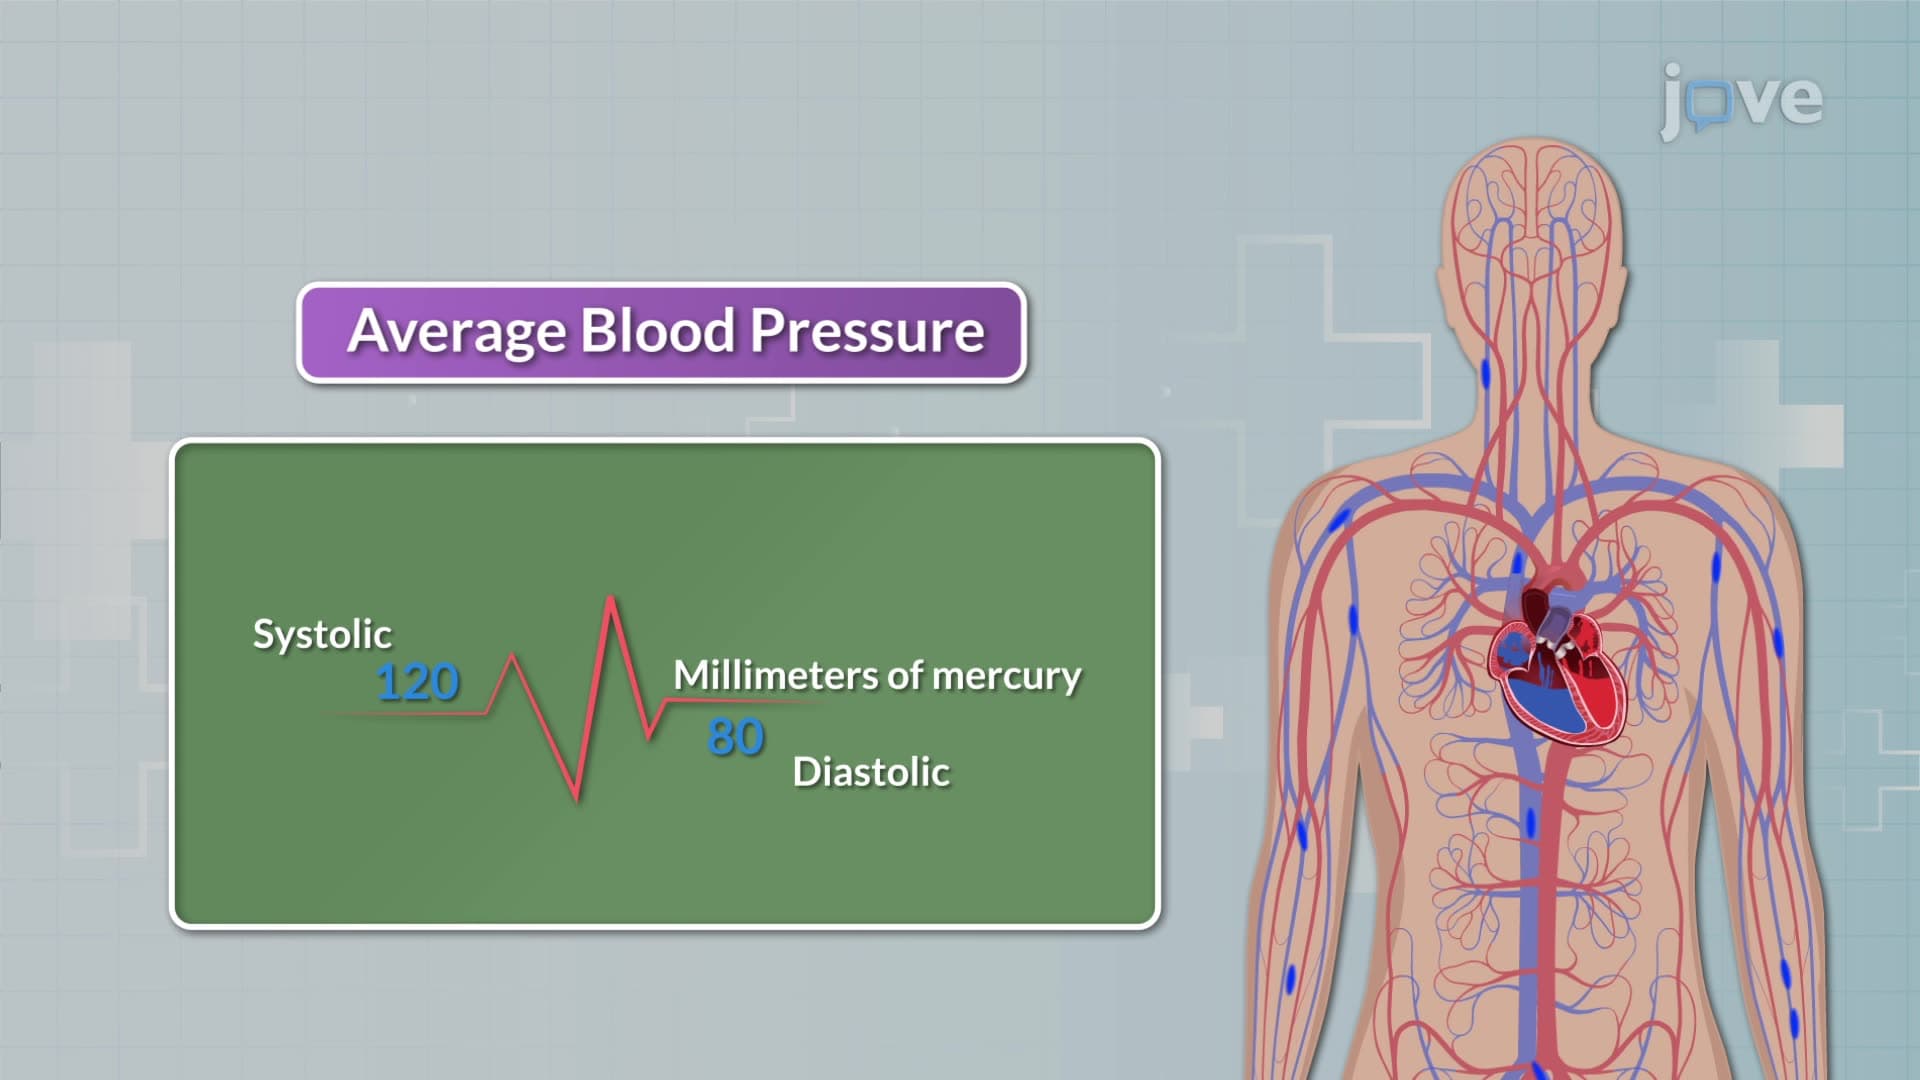
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:17
Measurement of Blood Pressure