Related Experiment Video
Updated: Dec 11, 2025
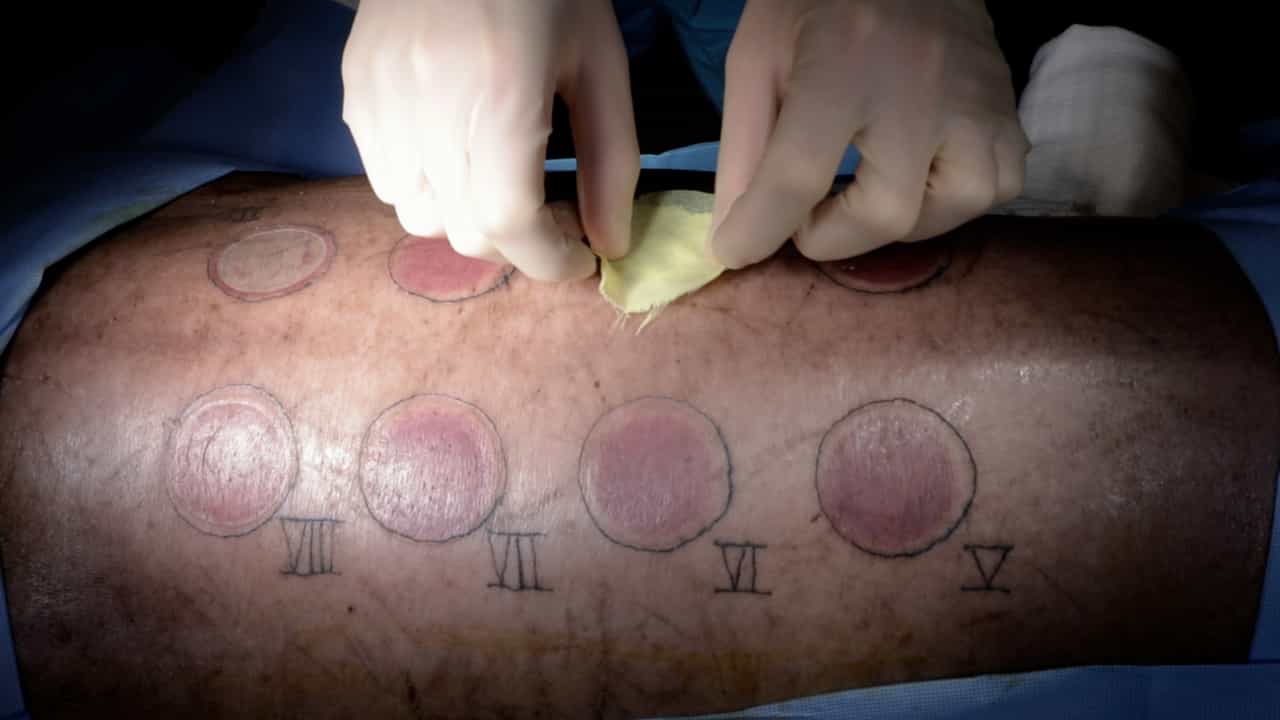
Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
Prehospital management of burns requiring specialized burn centre evaluation: a single physician-based emergency
Ludovic Maudet1,2,3, Mathieu Pasquier4,5, Olivier Pantet4,6
1Faculty of Biology and Medicine, University of Lausanne, Rue du Bugnon 21, CH-1011, Lausanne, Switzerland. ludovic.maudet@chuv.ch.

Background:
Emergency medical services regularly encounter severe burns. As standards of care are relatively well-established regarding their hospital management, prehospital care is comparatively poorly defined. The aim of this study was to describe burned patients taken care of by our physician-staffed emergency medical service (PEMS).
Methods:
All patients directly transported by our PEMS to our burn centre between January 2008 and December 2017 were retrospectively enrolled. We specifically addressed three "burn-related" variables: prehospital and hospital burn size estimations, type and volume of infusion and pain assessment and management. We divided patients into two groups for comparison: TBSA < 20% and ≥ 20%. We a priori defined clinically acceptable limits of agreement in the small and large burn group to be ±5% and ± 10%, respectively.
Results:
We included 86 patients whose median age was 26 years (IQR 12-51). The median prehospital TBSA was 10% (IQR 6-25). The difference between the prehospital and hospital TBSA estimations was outside the limits of agreement at 6.2%. The limits of agreement found in the small and large burn groups were - 5.3, 4.4 and - 10.1, 11, respectively. Crystalloid infusion was reported at a median volume of 0.8 ml/kg/TBSA (IQR 0.3-1.4) during the prehospital phase, which extrapolated over the first 8 h would equal to a median volume of 10.5 ml/kg/TBSA. The median verbal numeric rating scale on scene was 6 (IQR 3-8) and 3 (IQR 2-5) at the hospital (p < 0.001). Systemic analgesia was provided to 61 (71%) patients, predominantly with fentanyl (n = 59; 69%), followed by ketamine (n = 7; 8.1%). The median doses of fentanyl and ketamine were 1.7 mcg/kg (IQR 1-2.6) and 2.1 mg/kg (IQR 0.3-3.2), respectively.
Conclusions:
We found good agreement in burn size estimations. The quantity of crystalloid infused was higher than the recommended amount, suggesting a potential risk for fluid overload. Most patients benefited from a correct systemic analgesia. These results emphasized the need for dedicated guidelines and decision support aids for the prehospital management of burned patients.
Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...
 01:11
Secondary Healthcare System
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:26
Acute Coronary Syndrome V: Nursing Management