Greater α1-adrenergic-mediated vasoconstriction in contracting skeletal muscle of patients with type 2 diabetes
Joshua M Bock1, William E Hughes1, Kenichi Ueda2
1Department of Physical Therapy and Rehabilitation Science, Carver College of Medicine, University of Iowa, Iowa City, Iowa.

Abstract:
Patients with type 2 diabetes mellitus (T2DM) exhibit diminished exercise capacity likely attributable to reduced skeletal muscle blood flow (i.e., exercise hyperemia). A potential underlying mechanism of the impaired hyperemic response to exercise could be inadequate blunting of sympathetic-mediated vasoconstriction (i.e., poor functional sympatholysis). Therefore, we studied the hyperemic and vasodilatory responses to handgrip exercise in patients with T2DM as well as vasoconstriction to selective α-agonist infusion. Forearm blood flow (FBF) and vascular conductance (FVC) were examined in patients with T2DM (n = 30) as well as nondiabetic controls (n = 15) with similar age (59 ± 9 vs. 60 ± 9 yr, P = 0.69) and body mass index (31.4 ± 5.2 vs. 29.5 ± 4.6 kg/m2, P = 0.48). Intra-arterial infusion of phenylephrine (α1-agonist) and dexmedetomidine (α2-agonist) were used to induce vasoconstriction: [(FVCwith drug - FVCpredrug)/FVCpredrug × 100%]. Subjects completed rest and dynamic handgrip exercise (20% of maximum) trials per α-agonist. Patients with T2DM had smaller increases (Δ from rest) in FBF (147 ± 71 vs. 199 ± 63 ml/min) and FVC (126 ± 58 vs. 176 ± 50 ml·min-1·100 mmHg-1, P < 0.01 for both) during exercise compared with controls, respectively. During exercise, patients with T2DM had greater α1- (-16.9 ± 5.9 vs. -11.3 ± 3.8%) and α2-mediated vasoconstriction (-23.5 ± 7.1 vs. -19.0 ± 6.5%, P < 0.05 for both) versus controls. The magnitude of sympatholysis (Δ in %vasoconstriction between exercise and rest) for PE was lower (worse) in patients with T2DM versus controls (14.9 ± 12.2 vs. 23.1 ± 8.1%, P < 0.05) whereas groups were similar during DEX trials (24.6 ± 12.3 vs. 27.6 ± 13.4%, P = 0.47). Our data suggest patients with T2DM have attenuated hyperemic and vasodilatory responses to exercise, which could be attributable to greater α1-mediated vasoconstriction in contracting skeletal muscle.NEW & NOTEWORTHY Findings presented in this article are the first to show patients with type 2 diabetes mellitus have blunted hyperemic and vasodilatory responses to dynamic handgrip exercise. Moreover, we illustrate greater α1-adrenergic-mediated vasoconstriction may contribute to our initial observations. Collectively, these data suggest patients with type 2 diabetes may have impaired functional sympatholysis, which can contribute to their reduced exercise capacity.

Related Concept Videos
 01:31
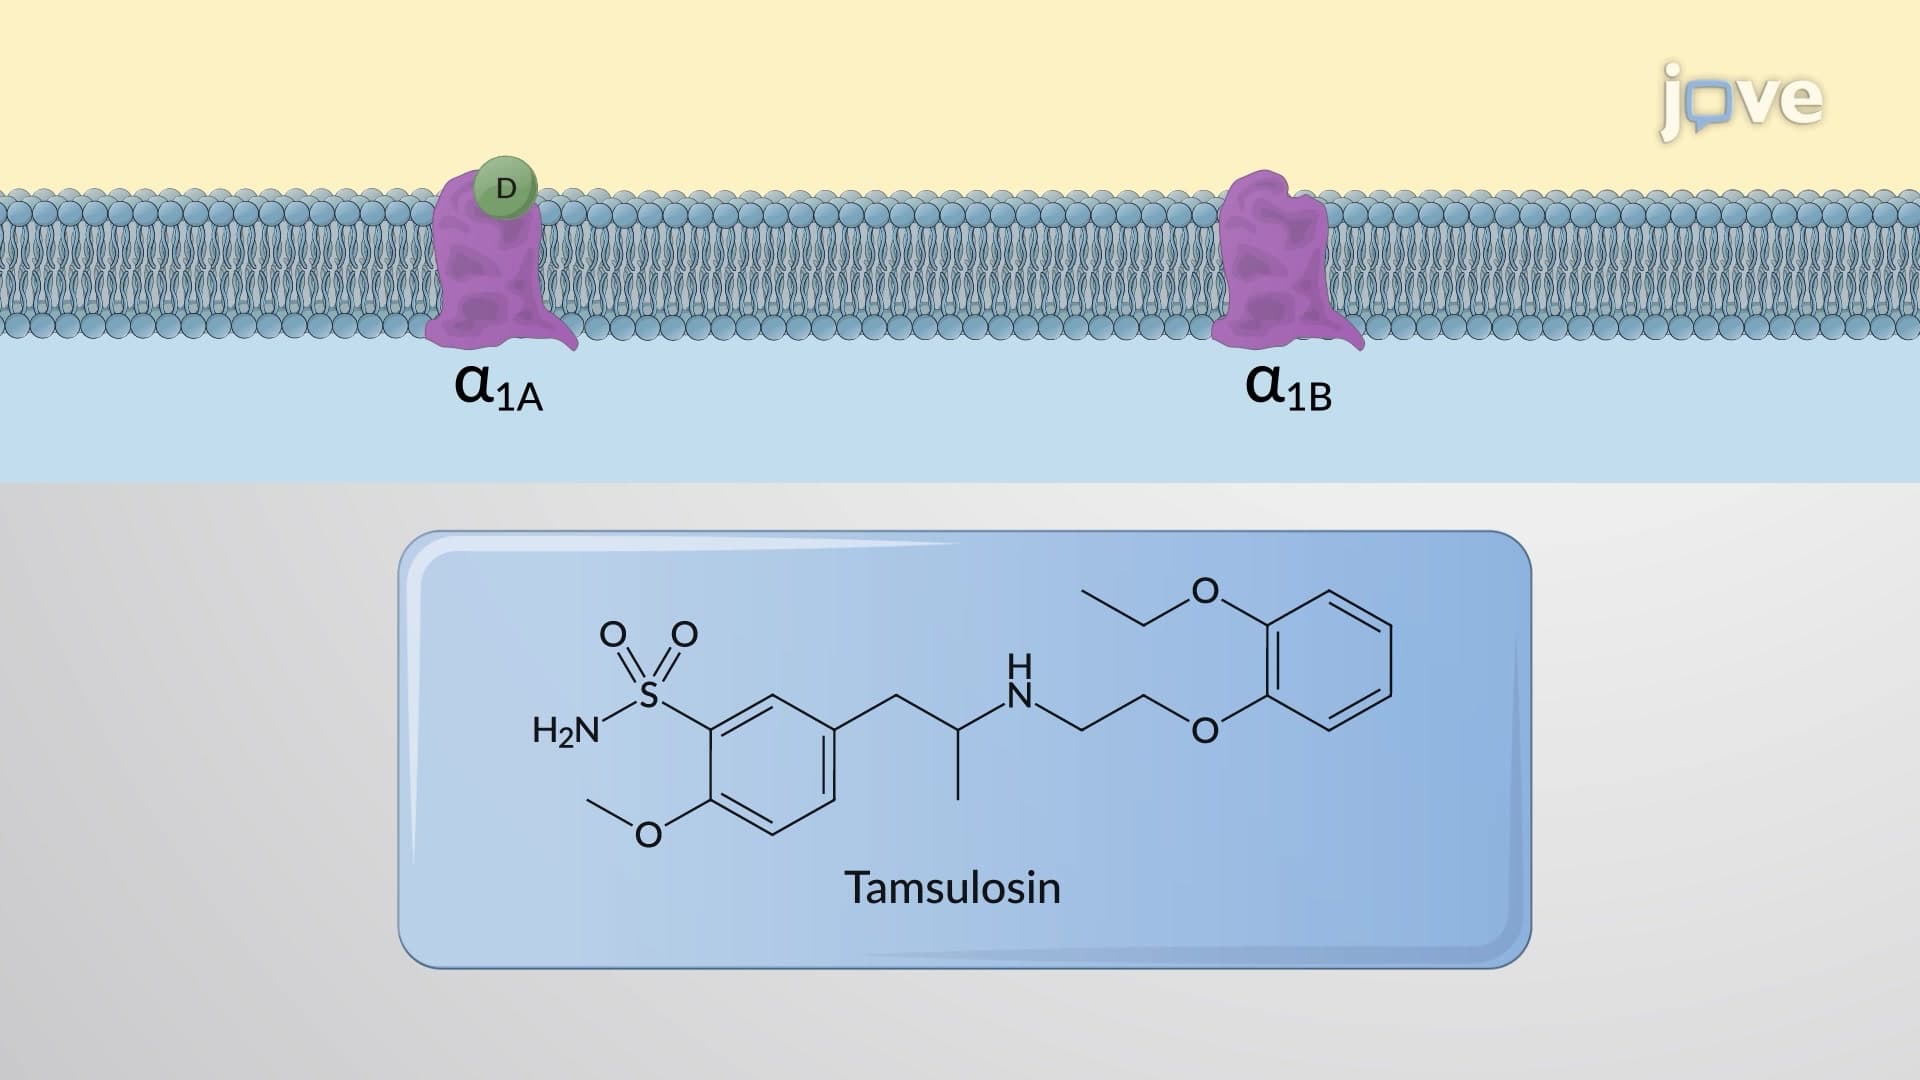
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:26
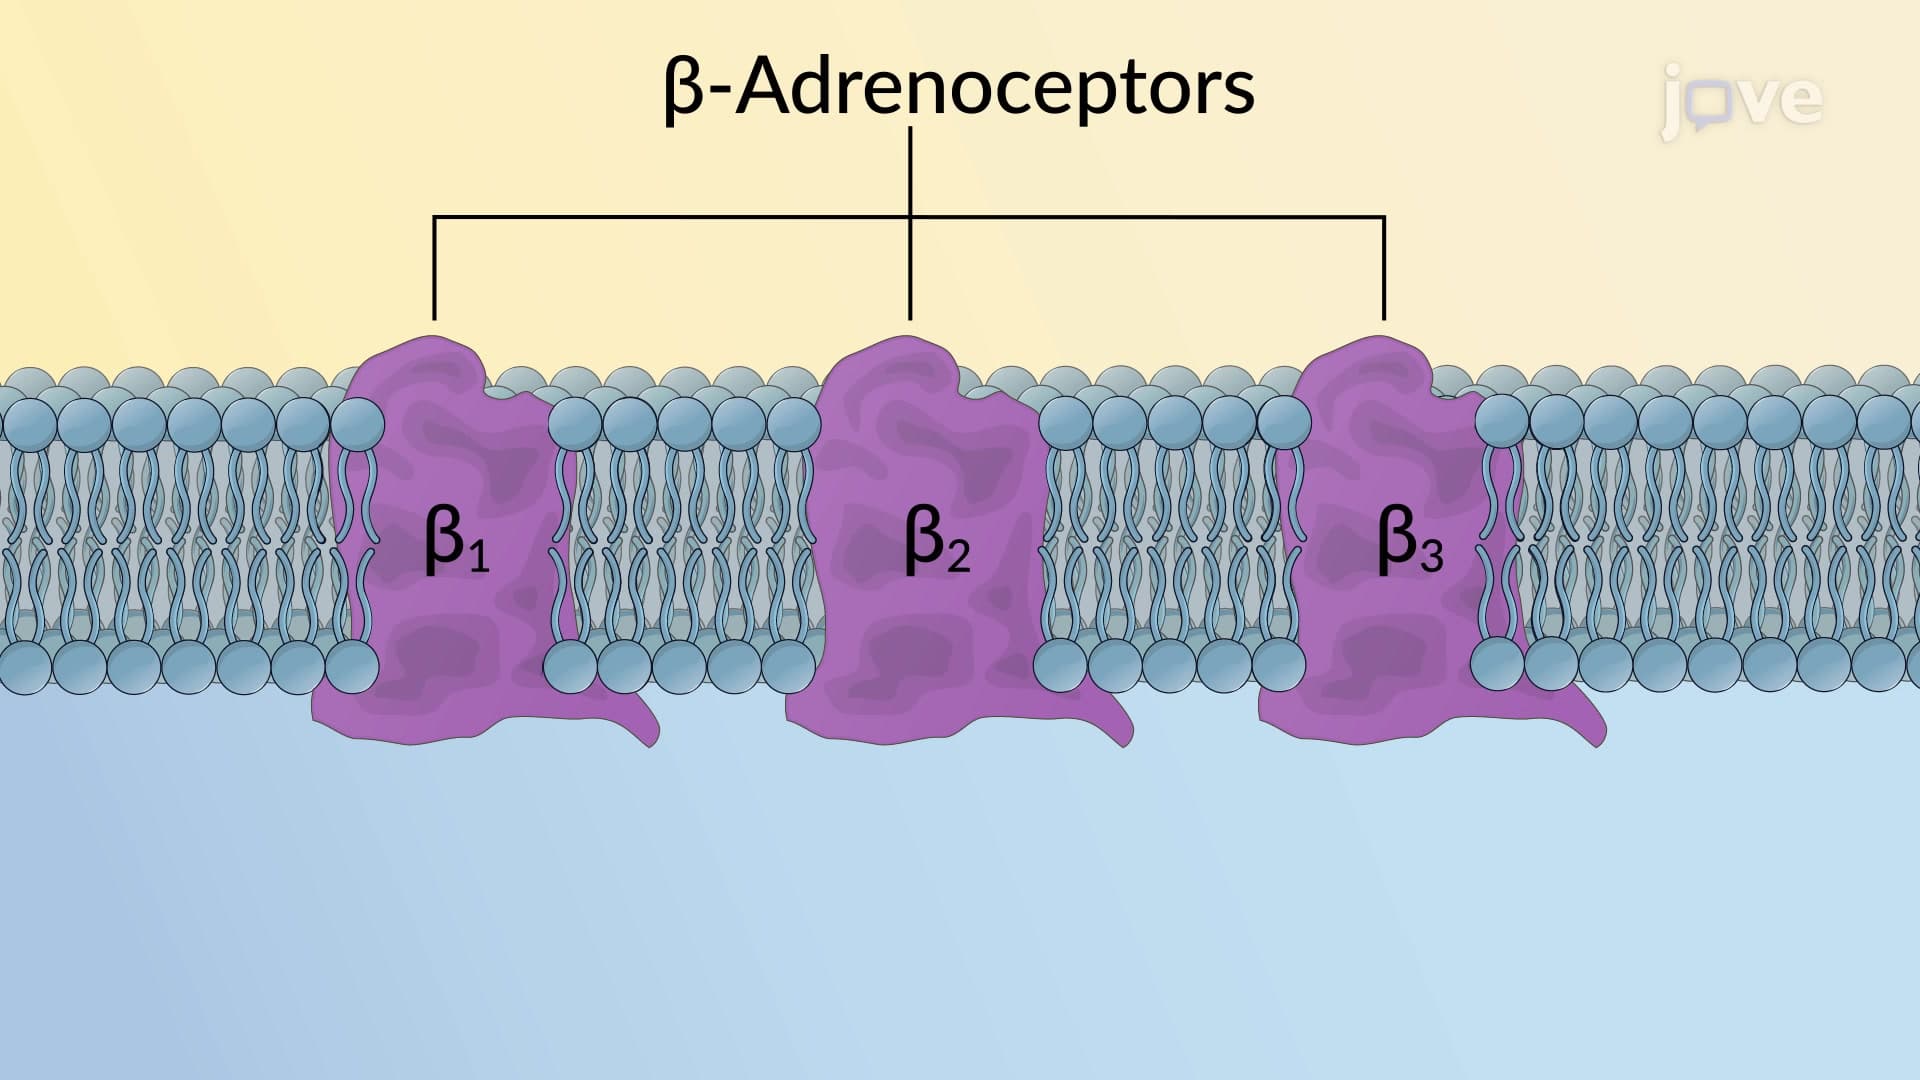
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:31
Sympathetic Signaling
Sympathetic preganglionic fibers release the neurotransmitter acetylcholine (ACh) onto the ganglionic neurons in the...