Related Experiment Video
Updated: Dec 11, 2025
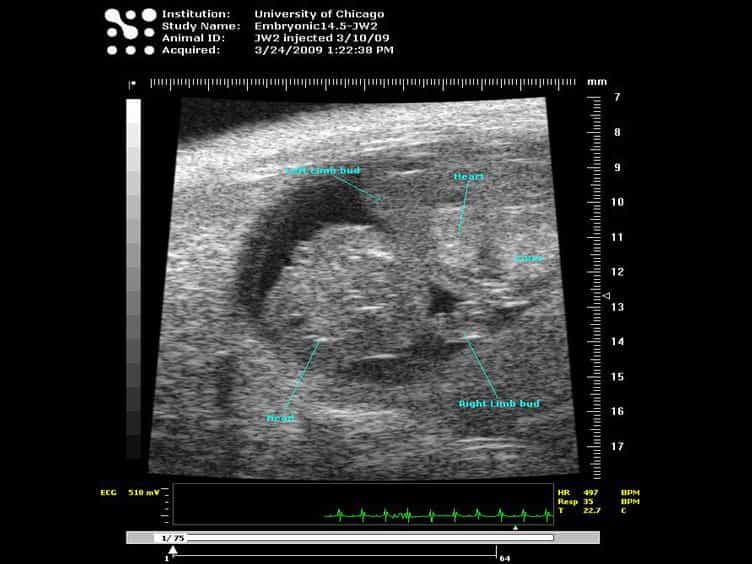
Murine Fetal Echocardiography
Published on: February 15, 2013
Diagnostic Accuracy of Fetal Echocardiography in Congenital Heart Disease
Namrita Mozumdar1, John Rowland2, Stephanie Pan2
1Department of Pediatrics, Division of Cardiology, Icahn School of Medicine at Mount Sinai, New York, New York.

Insights
Fetal echocardiography (FE) has a 13.5% diagnostic discrepancy (DD) rate, often minor or moderate. High complexity, maternal issues, and fewer exams increase DD risk, suggesting a need for review and repeat scans.
Area of Science:
- Cardiology
- Prenatal Diagnosis
- Medical Imaging
Background:
- Fetal echocardiography (FE) accuracy and diagnostic discrepancy (DD) reporting lack standardization.
- A categorization scheme from the American College of Cardiology was adapted for FE.
Purpose of the Study:
- To define the accuracy of fetal echocardiography.
- To standardize the reporting of diagnostic discrepancies in fetal echocardiography.
Main Methods:
- Retrospective single-center study of major structural congenital heart disease.
- Categorization of DDs (minor, moderate, severe) based on clinical impact.
- Multivariate regression analysis to identify factors associated with DDs.
Main Results:
- 13.5% of 222 fetuses with major structural heart disease had DDs, mostly false negatives.
- Technical limitations were the most common cause of DDs.
- High anatomic complexity, maternal comorbidities, and fewer FE exams were associated with DDs.
Conclusions:
- Fetal echocardiography has a 13.5% DD rate, predominantly minor to moderate.
- Factors influencing DDs include high anatomic complexity, maternal comorbidities, and sonographer experience.
- Regular secondary review and repeat FE, especially for complex cases, may reduce DDs.
Background:
The accuracy of fetal echocardiography (FE) is not well defined, and reporting of diagnostic discrepancies (DDs) is not standardized. The authors applied a categorization scheme developed by the American College of Cardiology Quality Metric Working Group and applied it to FE.
Methods:
A retrospective single-center study was conducted of prenatally diagnosed major structural congenital heart disease, defined as expected need for intervention within the first year of life. DDs between pre- and postnatal findings were identified and categorized. Minor DDs had no clinical impact, moderate DDs had impact without harm, and severe DDs resulted in adverse events. Multivariate regression analysis was used to determine factors associated with discrepancy.
Results:
From December 2008 to September 2017, 17,096 fetal echocardiograms were obtained, among which 222 fetuses with a median gestational age at first FE of 24 weeks were included. There were 30 DDs (13.5%), of which the majority were false negatives (56.7%). Most were minor or moderate in severity, with one severe DD. The majority were possibly preventable (90%), with the most common contributing factor being technical limitations (43.3%). The most common anatomic segment involved was the ventricular septum (23%), primarily missed septal defects. Comparing cases with DDs versus those without, those with DDs were more likely to have high anatomic complexity (16.7% vs 3.6%, P = .01), maternal comorbidities (40.0% vs 22.1%, P = .03), and a younger maternal age (median, 27 vs 30 years, P = .02). They were also more likely to have later gestation at initial FE (median, 29.5 vs 24 weeks, P = .003), to have fewer total fetal echocardiograms (median, 2 vs 3, P = .002), and to have a fellow as the initial sonographer (36.7% vs 16.7%, P = .03). There were no significant differences in maternal race/ethnicity, fetal comorbidities, and interpreting physician experience between cases with DDs and those without. On multivariate analysis, variables associated with DD included high anatomic complexity, maternal comorbidities, and fellow as initial imager. A greater number of fetal echocardiograms was associated with reduced DD.
Conclusions:
FE had a DD rate of 13.5%, mostly minor and moderate in severity. Factors associated with DD included high anatomic complexity, maternal comorbidities, fellow as the initial sonographer, and fewer fetal echocardiograms. Strategies to reduce DD could include a regular secondary review and repeat FE, particularly when anatomic complexity is high.


Related Concept Videos
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for...
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Dysrhythmias V: Evaluating Dysrhythmias