Related Experiment Video
Updated: Dec 10, 2025


A Novel Method for Involving Women of Color at High Risk for Preterm Birth in Research Priority Setting
Published on: January 12, 2018
[A retrospective analysis of single preterm birth incidence and high-risk factors based on maternal age

Objective: To compare the preterm birth rate among different age groups and analyze relative high-risk factors of preterm birth. Methods: A retrospective analysis was conducted on clinical data of single pregnant women ≥28 gestational weeks from January 2013 to May 2019 in the First Affiliated Hospital of Chongqing Medical Hospital. All involved women were divided into three groups according to age, Group 1 (aged<35 years), Group 2 (aged 35-39 years), and Group 3 (aged ≥40 years). The preterm birth rate among 3 groups was compared and their high-risk factors were analyzed. Results: There were 48 288 singleton pregnancies during the study period, of which 3 351 were preterm births, preterm birth rate was 6.94% (3 351/48 288). In Group 1, there were 42 020 women, of which 2 699 were preterm births (6.42%, 2 699/42 020); in Group 2, there were 5 061 women, of which 491 were preterm births (9.70%, 491/5 061); and in Group 3, there were 1 207 women, of which 161 were preterm births (13.34%, 161/1 207). Comparing the spontaneous preterm birth rates among the three groups, Group 1 was the lowest one and Group 3 was the highest one (3.72% vs 4.51% vs 5.88%); comparing the medical preterm birth rates among the three groups, Group 1 also was the lowest one and Group 3 also was the highest one (2.70% vs 5.20% vs 7.46%); the differences were statistically significant (P<0.05). The incidence of spontaneous and medical preterm birth according gestational weeks were compared among three groups and there were no significant differences (P>0.05). Comparing and analyzing the high-risk factors of medical preterm birth, the incidence of intrahepatic cholestasis of pregnancy and fetal distress in Group 1 were higher than those in Group 2 and 3; the incidence of placenta praevia were significantly higher in Group 2 and 3 than that in Group 1; the differences were statistically significant (P<0.05). Conclusions: Maternal age is a significant high-risk factor of both spontaneous preterm birth and medical preterm birth, and the risk of preterm birth increases with age. For medical preterm birth, compared with right-age pregnant women, placenta praevia is the high-risk factor for women in advanced maternal age(AMA), which have great effect on medical preterm birth rate of AMA.
Objective: To compare the preterm birth rate among different age groups and analyze relative high-risk factors of preterm birth. Methods: A retrospective analysis was conducted on clinical data of single pregnant women ≥28 gestational weeks from January 2013 to May 2019 in the First Affiliated Hospital of Chongqing Medical Hospital. All involved women were divided into three groups according to age, Group 1 (aged<35 years), Group 2 (aged 35-39 years), and Group 3 (aged ≥40 years). The preterm birth rate among 3 groups was compared and their high-risk factors were analyzed. Results: There were 48 288 singleton pregnancies during the study period, of which 3 351 were preterm births, preterm birth rate was 6.94% (3 351/48 288). In Group 1, there were 42 020 women, of which 2 699 were preterm births (6.42%, 2 699/42 020); in Group 2, there were 5 061 women, of which 491 were preterm births (9.70%, 491/5 061); and in Group 3, there were 1 207 women, of which 161 were preterm births (13.34%, 161/1 207). Comparing the spontaneous preterm birth rates among the three groups, Group 1 was the lowest one and Group 3 was the highest one (3.72% vs 4.51% vs 5.88%); comparing the medical preterm birth rates among the three groups, Group 1 also was the lowest one and Group 3 also was the highest one (2.70% vs 5.20% vs 7.46%); the differences were statistically significant (P<0.05). The incidence of spontaneous and medical preterm birth according gestational weeks were compared among three groups and there were no significant differences (P>0.05). Comparing and analyzing the high-risk factors of medical preterm birth, the incidence of intrahepatic cholestasis of pregnancy and fetal distress in Group 1 were higher than those in Group 2 and 3; the incidence of placenta praevia were significantly higher in Group 2 and 3 than that in Group 1; the differences were statistically significant (P<0.05). Conclusions: Maternal age is a significant high-risk factor of both spontaneous preterm birth and medical preterm birth, and the risk of preterm birth increases with age. For medical preterm birth, compared with right-age pregnant women, placenta praevia is the high-risk factor for women in advanced maternal age(AMA), which have great effect on medical preterm birth rate of AMA.


Related Concept Videos
 01:52
Regression Toward the Mean
 02:57
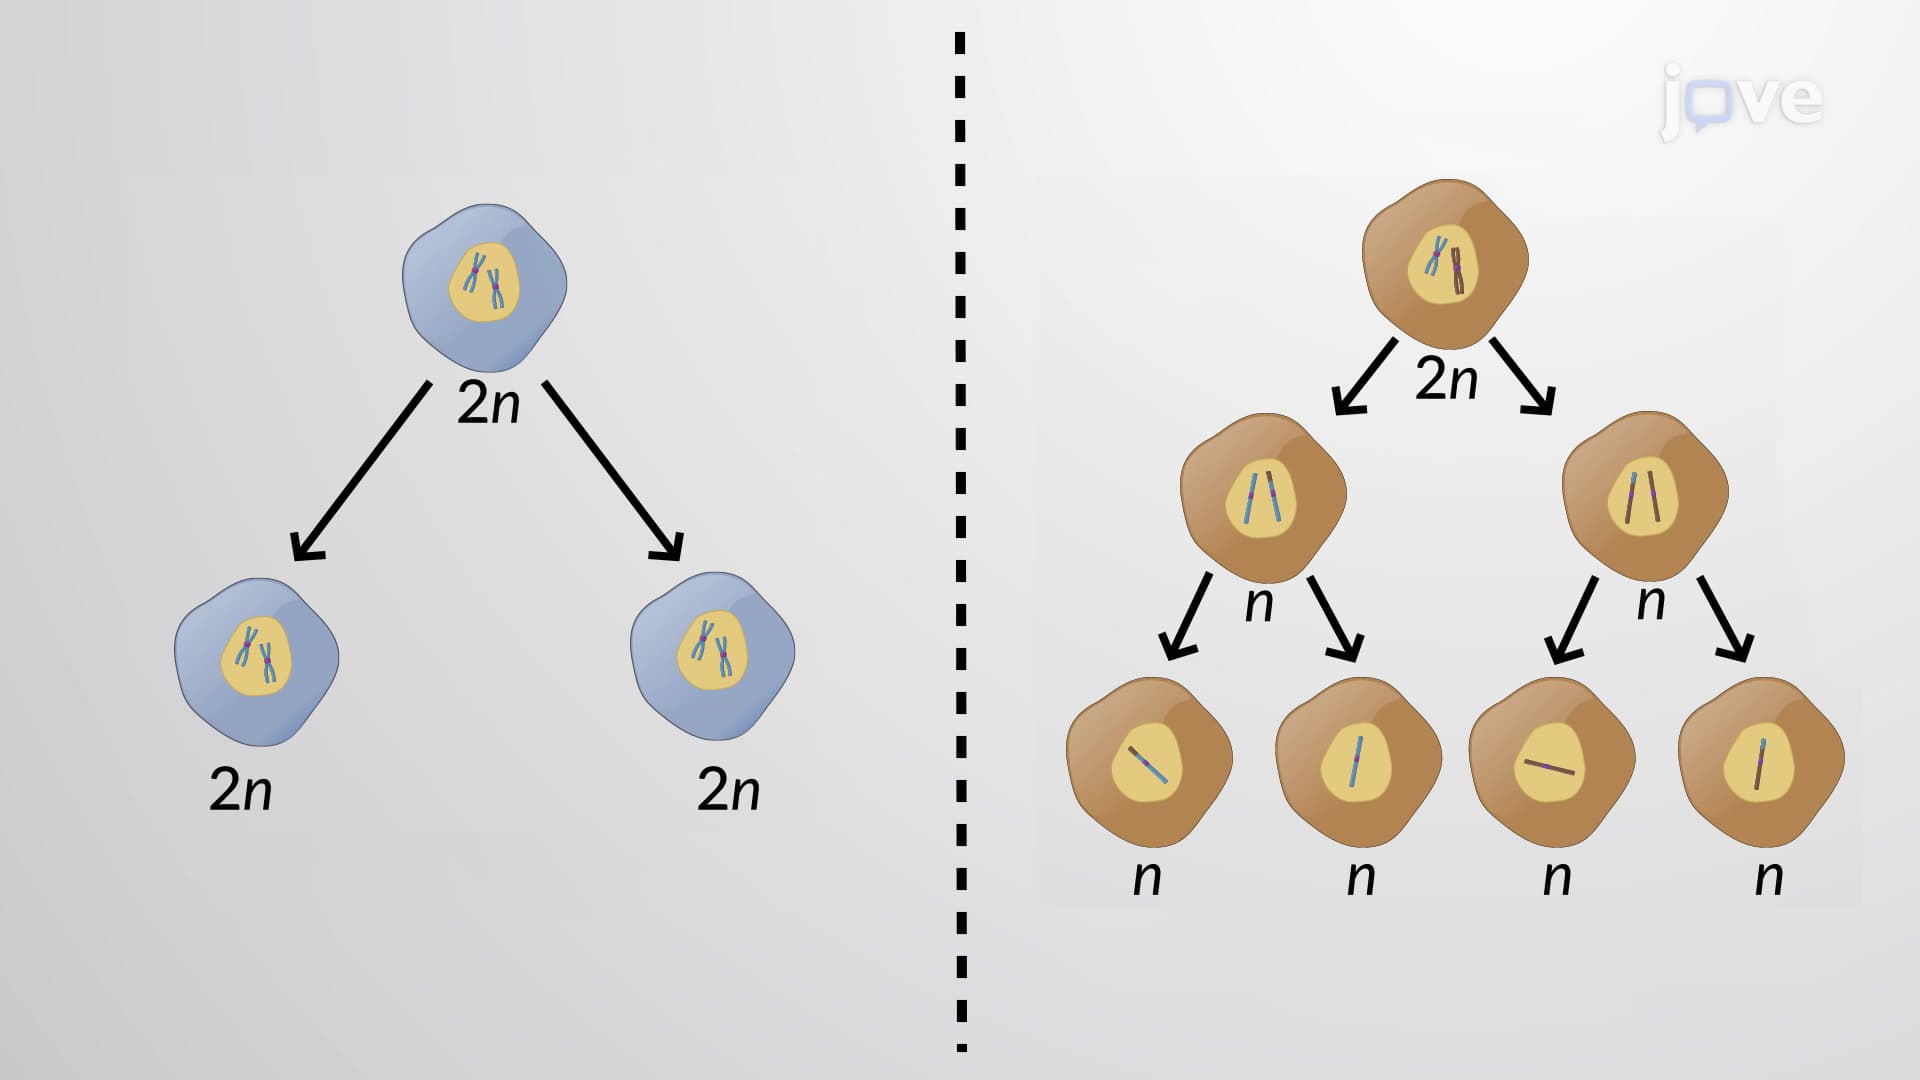
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 02:07
Oogenesis
 01:20
Actuarial Approach
Consider the example of a high-risk surgical procedure with significant early-stage mortality. A two-year clinical study is conducted,...
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...