Related Experiment Video
Updated: Dec 10, 2025
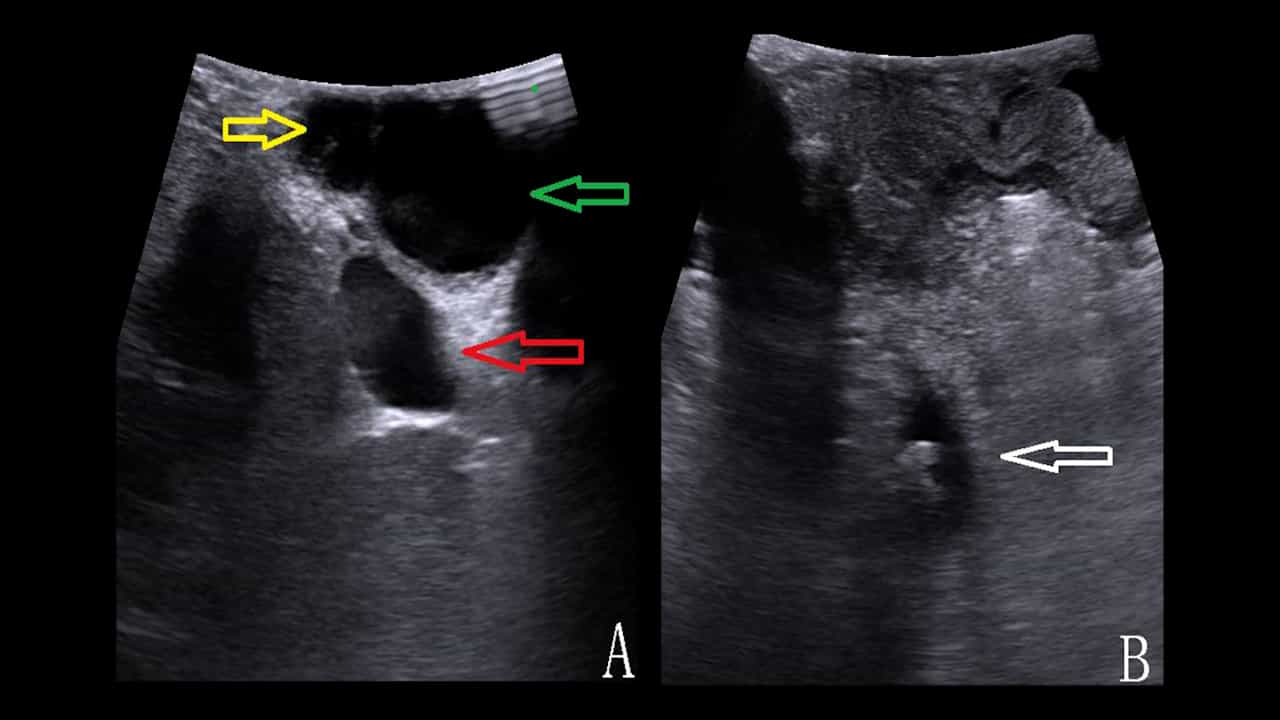

Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
Considering delay of cholecystectomy in the third trimester of pregnancy
Julie Hong1, Jie Yang2, Xiaoyue Zhang2
1Division of Bariatric, Foregut, and Advanced Gastrointestinal Surgery, Department of Surgery, Stony Brook University Medical Center, Stony Brook, NY, USA. juliehongeras@gmail.com.

Introduction:
Current guidelines support laparoscopic cholecystectomy as the treatment of choice for pregnant women with symptomatic gallbladder disease, regardless of the trimester. Early intervention has remained the standard of care, but recent evidence has challenged this practice in pregnant women. We sought to compare surgical and maternal-fetal outcomes of antepartum versus postpartum cholecystectomy in New York State.
Methods:
Between 2005 and 2014, the New York Statewide Planning and Research Cooperative System (SPARCS) database was queried for patients who underwent cholecystectomy within 3 months before (antepartum cholecystectomy, APCCY: n = 82) and after (postpartum cholecystectomy, PPCCY: n = 5040) childbirth to approximate third-trimester operations. All patients who underwent cholecystectomy during pregnancy (n = 971) were extracted to evaluate inter-trimester differences. Subgroup analysis compared APCCY patients who were not hospitalized within 1 year before APCCY (n = 80) and PPCCY patients who were hospitalized within 1 year before childbirth (n = 29) for symptomatic biliary disease. Multivariable generalized linear regression models were used to characterize the association between timing of cholecystectomy and several primary outcomes: length of stay (LOS), 30-day non-pregnancy, non-delivery readmission (NPND), bile duct injury (BDI), composite maternal outcome (antepartum hemorrhage, preterm delivery, cesarean section), any complications, and fetal demise.
Results:
Third-trimester APCCY women had longer LOS (Ratio: 1.44, 95% CI [1.26-1.66], p < 0.0001) and greater incidence of preterm delivery (OR 2.54, 95% CI [1.37-4.43], p = 0.0019). Cholecystectomy timing was not independently associated with differences in composite maternal outcome (p = 0.1480), BDI (p = 0.2578), 30-day NPND readmission (p = 0.7579), any complications (p = 0.2506), and fetal demise (2.44% versus 0.44%, p = 0.0545). Subgroup analysis revealed no differences in any of the seven outcomes.
Conclusions:
New York Statewide data suggest that although laparoscopic cholecystectomy is safe in pregnancy, delay of cholecystectomy should be discussed in the third trimester due to an increased risk for preterm delivery.
Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...