Related Experiment Video
Updated: Dec 9, 2025
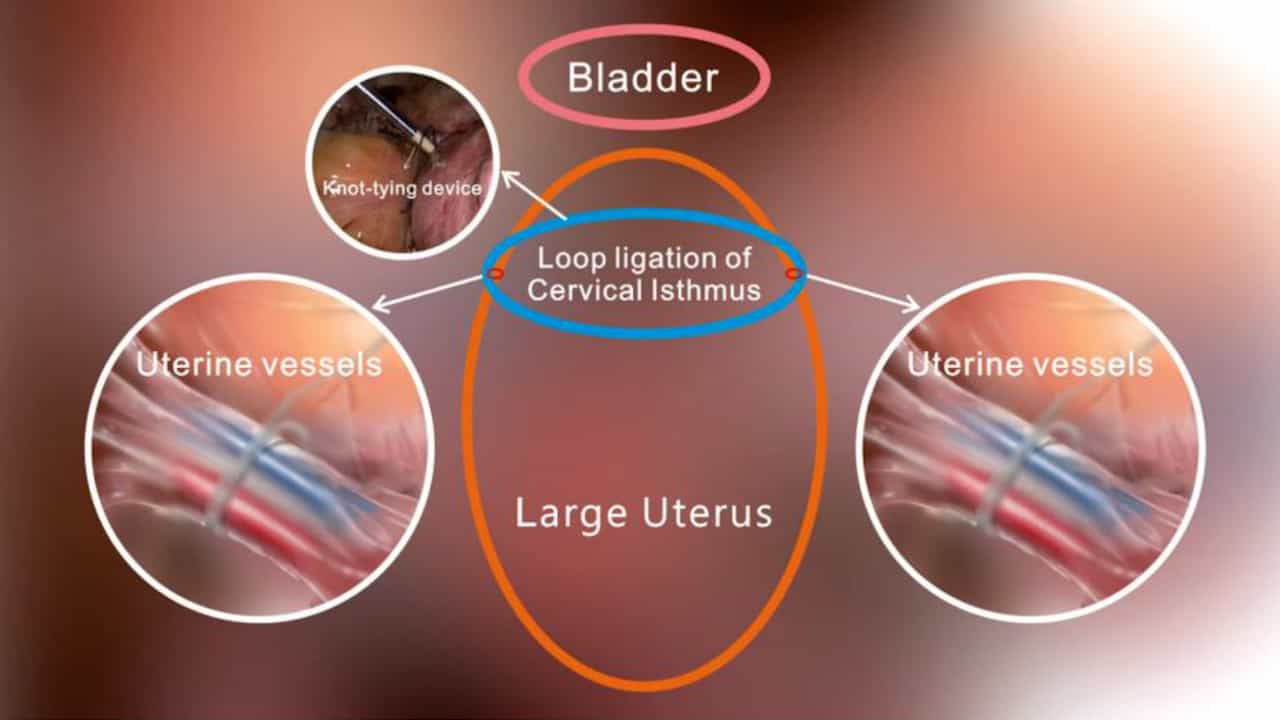
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Impact of Surgical Wait Time to Hysterectomy for Benign Gynecologic Disease
Jessica Traylor1, Nathanael Koelper2, Sun Woo Kim2
1Department of Obstetrics and Gynecology, Hospital of the University of Pennsylvania, Philadelphia, Pennsylvania (all authors)..

Insights
Longer surgical wait times for hysterectomy increase healthcare use and readmission risk. Optimizing care coordination is crucial for patients with benign gynecologic conditions.
Area of Science:
- Gynecology
- Surgical Outcomes
- Healthcare Management
Background:
- Surgical wait times can impact patient outcomes and healthcare resource utilization.
- Hysterectomy for benign gynecologic conditions is a common procedure with varying wait times.
- Understanding the relationship between wait times and outcomes is essential for quality improvement.
Purpose of the Study:
- To evaluate the effect of surgical wait time on healthcare utilization and surgical outcomes.
- To identify associations between wait times exceeding 30 days and patient outcomes after hysterectomy for benign conditions.
Main Methods:
- Retrospective cohort study of 277 patients undergoing hysterectomy for benign disease (2012-2018).
- Patients categorized into groups with wait times >30 days or ≤30 days.
- Healthcare use measured by patient interactions; outcomes assessed via logistic regression.
Main Results:
- Patients with wait times >30 days showed significantly increased healthcare use (OR 5.55).
- No significant difference in intraoperative or postoperative complications between groups.
- Longer wait times (>30 days) were associated with a 3.22-fold increased risk of readmission.
Conclusions:
- Surgical wait times exceeding 30 days for hysterectomy are linked to greater interim healthcare use.
- While immediate surgical outcomes are similar, longer waits increase readmission risk.
- Interventions are needed to optimize care coordination, reduce healthcare use, and minimize delays for these patients.
Study Objective:
To determine the impact of surgical wait time on healthcare use and surgical outcomes for patients undergoing hysterectomy for benign gynecologic indications.
Design:
Retrospective cohort study.
Setting:
Urban, academic tertiary care center.
Patients:
Patients who underwent hysterectomy for benign disease between 2012 and 2018.
Interventions:
None.
Measurements And Main Results:
Patients were categorized into 2 groups, dichotomized by surgical wait times >30 days or ≤30 days. Healthcare use was measured by the number of discrete patient interactions with the healthcare system through phone calls, secure electronic messaging, and office and emergency room visits. Univariate and multivariable logistic regression models were performed to assess the association between surgical wait time and healthcare use and perioperative outcomes while controlling for confounders. A total of 277 patients were included in our analysis: 106 (38.3%) had surgical wait times >30 days (median 47 days, range 24-68 days), and 171 (67.1%) had surgical wait times ≤30 days (median 19 days; range 12-26 days). The groups did not differ by age, insurance status, substance use, or comorbid conditions. Patients in the group with surgical wait times >30 days were more likely to have increased healthcare use (69 of 106, 65% vs 43 of 171, 25%; odds ratio 5.55; 95% confidence interval, 3.27-9.41). There were no differences in intraoperative complications (9 of 106, 8% vs 19 of 171, 11%; p = .482) or postoperative complications (28 of 106, 26% vs 32 of 171, 19%; p = .13) between the groups; however, after controlling for potential confounders, patients with surgical wait times >30 days were 3.22 times more likely to be readmitted than patients with surgical wait times ≤30 days (95% confidence interval, 1.27-8.19).
Conclusion:
A surgical wait time >30 days in patients undergoing a hysterectomy for benign disease is associated with increased healthcare use in the interim. Although patients who experience longer surgical wait times do not experience worse surgical outcomes, they may be at higher risk for readmission after surgery. Targeted interventions to optimize perioperative coordination of care for patients undergoing a hysterectomy for benign disease, especially those within vulnerable populations, are needed to improve quality of care, decrease any redundant or inefficient healthcare use, and reduce any unnecessary delays.
More Related Videos
 05:46
Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
 03:01
Author Spotlight: A Reproductive Hysteroscopy Approach for Complete Endometrial Polyp Removal and Enhanced Endometrial Receptivity
Published on: August 2, 2024
Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:25
Urinary Tract Calculi VI: Surgical Management