Related Experiment Video
Updated: Dec 9, 2025
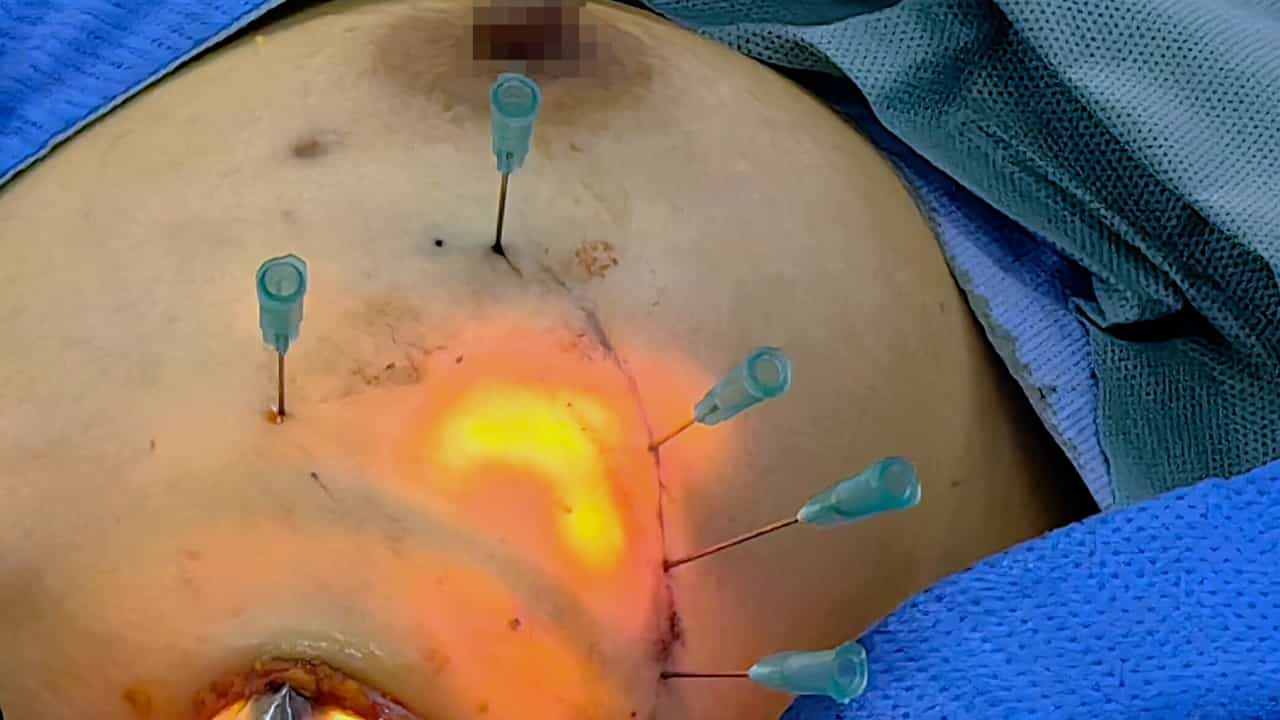

Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
Feasibility of Axillary Lymph Node Localization and Excision Using Radar Reflector Localization
James Sun1, Danielle A Henry2, Michael J Carr3
1Department of Breast Oncology, Moffitt Cancer Center, Tampa, FL; Present affiliation: Department of Surgery, University Hospitals, Cleveland Medical Center, Cleveland, OH.

Introduction:
Neoadjuvant chemotherapy (NAC) is commonly used for patients with clinically detected nodal metastases. Sentinel lymph node biopsy (SLNB) after NAC is feasible. Excision of biopsy-proven positive lymph nodes in addition to SLNB, termed targeted axillary dissection (TAD), decreases the false-negative rate of SLNB alone. Positive nodes can be marked with radar reflector-localization (RRL) clips. We report our institutional experience with RRL-guided TAD and demonstrate its safety and feasibility.
Patients And Methods:
We performed an institutional review board-approved retrospective review of consecutive clinically node-positive female patients with breast cancer treated with NAC and RRL-guided TAD between January 2017 and September 2019. Clinicopathologic and treatment data were collected; descriptive statistics are reported.
Results:
Forty-five patients were analyzed; the median age was 55 years (range, 20-72 years), and the median body mass index was 27.2 kg/m2 (range, 16.5-40.4 kg/m2). All patients received NAC, primary breast surgery, and TAD. All clinically detected nodal metastases were confirmed with percutaneous biopsy and marked with a biopsy clip. RRL clips were implanted a median of 8 days (range, 1-167 days) prior to surgery; all were retrieved without complications. The RRL node was identified as the sentinel lymph node in 36 (80%) patients. Twenty-five patients had positive nodes, of which 24 were identified by RRL node excision, and 1 (4%) patient had a positive node identified by SLNB but not RRL. Over a median follow-up time of 29.6 months, 5 patients recurred (1 local, 4 distant).
Conclusions:
RRL-guided TAD after NAC is safe and feasible. This technique allows for adequate assessment of the nodal basin and helps confirm excision of the previously biopsied positive axillary node.
More Related Videos
 07:30
Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
 13:35
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024