Related Experiment Video
Updated: Dec 5, 2025

Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Pitfalls in Expiratory Flow Limitation Assessment at Peak Exercise in Children: Role of Thoracic Gas Compression
Danielle Strozza1, Daniel P Wilhite2, Tony G Babb2
1School of Medicine, University of Nevada Las Vegas, Las Vegas, NV.

Purpose:
Thoracic gas compression and exercise-induced bronchodilation can influence the assessment of expiratory flow limitation (EFL) during cardiopulmonary exercise tests. The purpose of this study was to examine the effect of thoracic gas compression and exercise-induced bronchodilation on the assessment of EFL in children with and without obesity.
Methods:
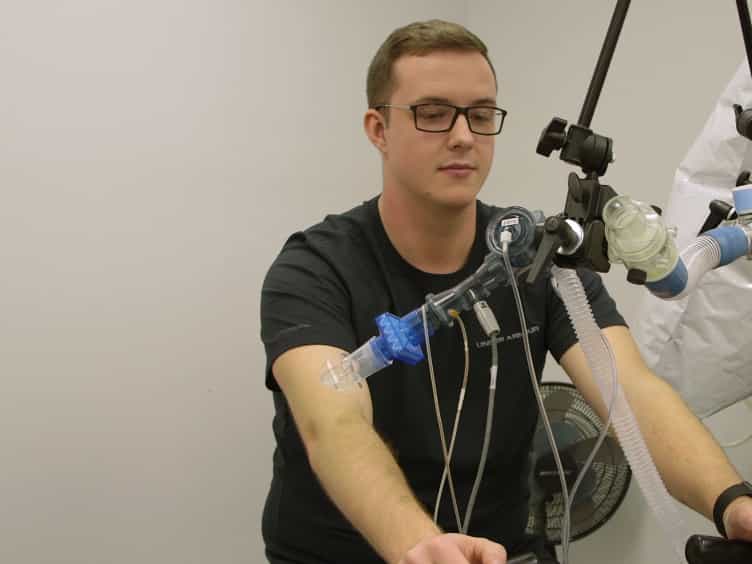
Forty children (10.7 ± 1.0 yr; 27 obese; 15 with EFL) completed pulmonary function tests and incremental exercise tests. Inspiratory capacity maneuvers were performed during the incremental exercise test for the placement of tidal flow volume loops within the maximal expiratory flow volume (MEFV) loops, and EFL was calculated as the overlap between the tidal and the MEFV loops. MEFV loops were plotted with volume measured at the lung using plethysmography (MEFVp), with volume measured at the mouth using spirometry concurrent with measurements in the plethysmograph (MEFVm), and from spirometry before (MEFVpre) and after (MEFVpost) the incremental exercise test. Only the MEFVp loops were corrected for thoracic gas compression.
Results:
Not correcting for thoracic gas compression resulted in incorrect diagnosis of EFL in 23% of children at peak exercise. EFL was 26% ± 15% VT higher for MEFVm compared with MEFVp (P < 0.001), with no differences between children with and without obesity (P = 0.833). The difference in EFL estimation using MEFVpre (37% ± 30% VT) and MEFVpost (31% ± 26% VT) did not reach statistical significance (P = 0.346).
Conclusions:
Not correcting the MEFV loops for thoracic gas compression leads to the overdiagnosis and overestimation of EFL. Because most commercially available metabolic measurement systems do not correct for thoracic gas compression during spirometry, there may be a significant overdiagnosis of EFL in cardiopulmonary exercise testing. Therefore, clinicians must exercise caution while interpreting EFL when the MEFV loop is derived through spirometry.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...