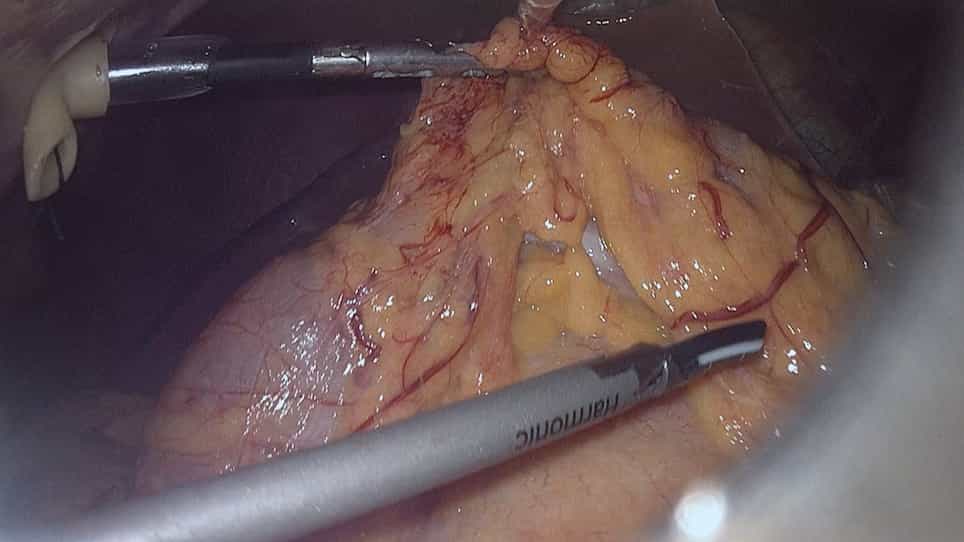
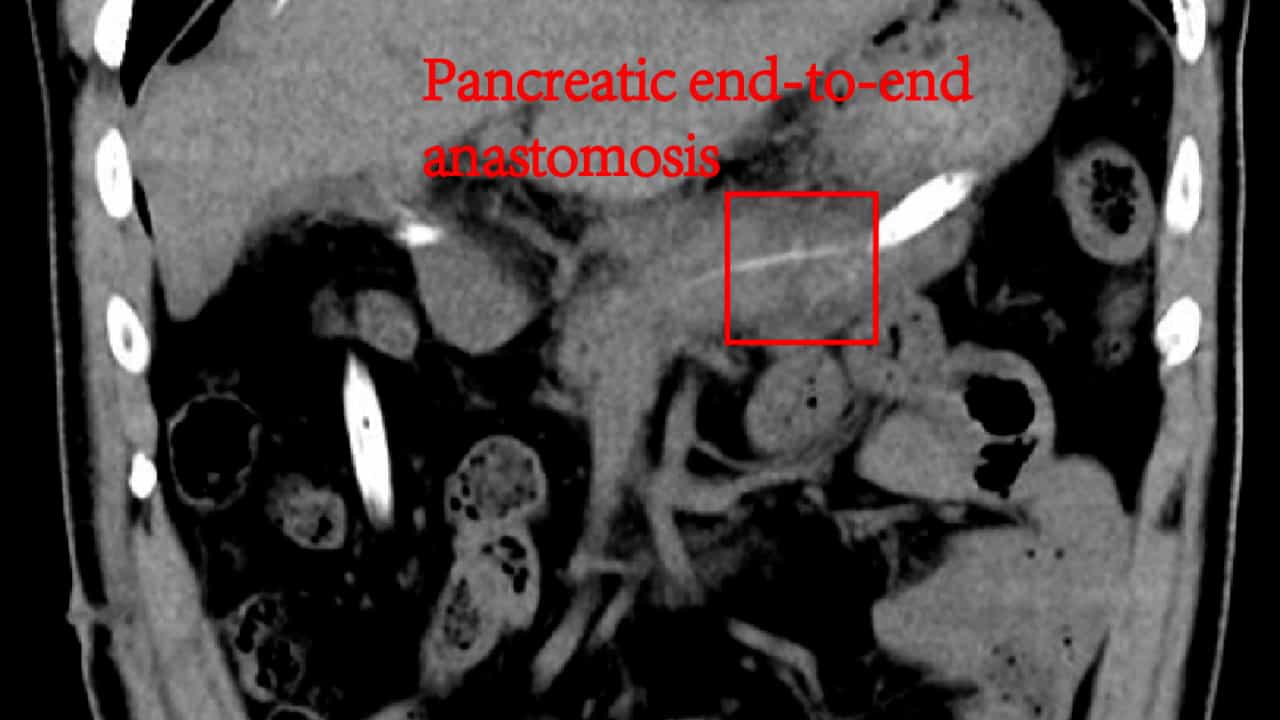
Related Experiment Video
Updated: Dec 5, 2025

Robotic Central Pancreatectomy with Roux-en-Y Pancreaticojejunostomy
Published on: November 20, 2021
Distal pancreatectomy after pancreatic injury, in two pediatric patients
Theodoros Hadjizacharias1, Ioannis Kaliviotis2, George Kottakis2
12nd Department of Surgery, Aretaieion University Hospital, Medical School, National and Kapodistrian University of Athens, Greece.

Insights
Pediatric blunt abdominal trauma can cause severe pancreatic injuries. Surgical management, including distal pancreatectomy and splenectomy, offers excellent outcomes for Grade IV pancreatic injuries in children.
Area of Science:
- Pediatric Surgery
- Trauma Management
- Gastrointestinal Surgery
Background:
- Blunt abdominal trauma in children presents management challenges.
- Pancreatic injuries, particularly with main pancreatic duct rupture, are complex.
- Grade IV pancreatic injury requires specialized surgical consideration.
Introduction:
Although serious trauma is rare in pediatric patients, the management of blunt force trauma to the abdomen remains a challenge for Child Surgery Departments. Pancreatic injury comprises the fourth most common injury among the solid organs and cases accompanied by rupture of the main pancreatic duct (MPD) present a further challenge for physicians (Fayza Haider et al.; Wood et al., 2010; Jobst et al., 1999; Grosfeld et al., 2006).
Case Presentation:
Two adolescents, both 13 years old, where referred to our Pediatric Hospital, due to blunt force abdominal trauma. During admission, both patients were hemodynamically stable, in good general condition but suffering from abdominal pain and vomiting. After a full diagnostic check-up, grade IV pancreatic injury was diagnosed in both patients and they were taken to the operation room 3 and 6 days post-injury. Intra-operatively a distal pancreatectomy along with splenectomy was performed in both cases, with catheterization and ligation of the main pancreatic duct. Both patients were admitted to the pediatric ICU for 2 and 4 days. Both made an uneventful recovery and remain well 6 months postoperatively.
Conclusion:
While hemodynamically stable, patients with Grade IV pancreatic injury, benefit from sub-acute management, allowing for planning of the surgical intervention. Distal pancreatectomy with splenectomy, along with catheterization and ligation of the main pancreatic duct, has excellent post-operative results. The chief of the Pediatric Hospital, said that in 35 years at pediatric surgery, is the first time with the need of operative management, in pancreatic injury. The hepatobiliary surgical expert in adults, who was consulted in both cases, said that without the surgeries, both children were going to die.