Related Experiment Video
Updated: Dec 5, 2025


Description of a Swine Infant Model of Volume-Controlled Hemorrhagic Shock
Published on: November 3, 2023
Hemodynamic Response to Fluid Boluses for Hypotension in Children in a Cardiac ICU
Ben Gelbart1, Anatole Harrois2,3, Lauren Gardiner4
1Paediatric Intensive Care Unit, Royal Children's Hospital, University of Melbourne, Department of Paediatrics, Murdoch Children's Research Institute, Parkville, VIC, Australia.

Insights
Fluid boluses in pediatric cardiac ICU patients with hypotension showed a 66% response rate. The mean arterial pressure increase was temporary, often returning to baseline shortly after administration.
Area of Science:
- Pediatric Cardiology
- Critical Care Medicine
- Hemodynamics
Background:
- Hypotension is a critical concern in pediatric cardiac intensive care units (CICU).
- Fluid boluses are a common intervention, but their hemodynamic effects in this population require detailed description.
Purpose of the Study:
- To characterize the hemodynamic response to fluid boluses in children experiencing hypotension within a cardiac ICU setting.
- To identify factors influencing the response to fluid administration.
Main Methods:
- Prospective, observational study conducted in a single-centered cardiac ICU.
- Monitored hemodynamic parameters in children receiving clinician-prescribed fluid boluses for hypotension.
- Analyzed fluid composition, volume, duration, and associated clinical factors.
Main Results:
- 66% of fluid boluses resulted in a mean arterial pressure (MAP) response (≥10% increase).
- The peak MAP increase in responders was 15 mm Hg, occurring at a median of 17 minutes.
- MAP response often dissipated, with 67% returning to baseline within study parameters.
- Cardiopulmonary bypass pump blood was associated with a greater peak MAP change.
Conclusions:
- Fluid boluses in pediatric CICU patients with hypotension yield a moderate response rate.
- The hemodynamic improvement from fluid boluses is typically transient, with responses often returning to baseline.
- Further research may explore optimal fluid strategies and adjunct therapies in this vulnerable population.
Objectives:
To describe the hemodynamic response to fluid boluses for hypotension in children in a cardiac ICU.
Design:
A prospective, observational study.
Setting:
Single-centered cardiac ICU.
Patients:
Children in a cardiac ICU with hypotension.
Interventions:
Clinician prescribed fluid bolus.
Measurements And Main Results:
Sixty-four fluid boluses were administered to 52 children. Fluid composition was 4% albumin in 36/64 (56%), 0.9% saline in 18/64 (28%), and cardiopulmonary bypass pump blood in 10/64 (16%). The median volume and duration were 5.0 mL/kg (interquartile range, 4.8-5.4) and 8 minutes (interquartile range, 4-19), respectively. Hypovolemia/low filling pressures was the most common additional indication (25/102 [25%]). Mean arterial pressure response, defined as a 10% increase from baseline, occurred in 42/64 (66%) of all fluid boluses at a median time of 6 minutes (interquartile range, 4-11). Mean arterial pressure responders had a median peak increase in the mean arterial pressure of 15 mm Hg (43 mm Hg [interquartile range, 29-50 mm Hg] to 58 mm Hg [interquartile range, 49-65 mm Hg]) at 17 minutes (interquartile range, 14-24 min) compared with 4 mm Hg (48 mm Hg [interquartile range, 40-51 mm Hg] to 52 mm Hg [interquartile range, 45-56 mm Hg]) at 10 minutes (interquartile range, 3-18 min) in nonresponders. Dissipation of mean arterial pressure response, when defined as a subsequent decrement in mean arterial pressure below 10%, 5%, and 2% increases from baseline, occurred in 28/42 (67%), 18/42 (43%), and 13/42 (31%) of mean arterial pressure responders, respectively. Cardiopulmonary bypass pump blood was strongly associated with peak change in mean arterial pressure from baseline (coefficient 11.0 [95% CI, 4.3-17.7]; p = 0.02). Fifty out of 64 (78%) were receiving a vasoactive agent. However, change in vasoactive inotrope score was not associated with change in mean arterial pressure (coefficient 2.3 [95% CI, -2.5 to -7.2]; p = 0.35). Timing from admission, nor fluid bolus duration, influenced mean arterial pressure response.
Conclusions:
In children with hypotension in a cardiac ICU, the median dose and duration of fluid boluses were 5 mL/kg and 8 minutes. Peak response occurred shortly following administration and commonly returned to baseline.

Related Concept Videos
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:29
Drug Dosing: Infants and Children
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:29
Heart Failure II: Pathophysiology
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
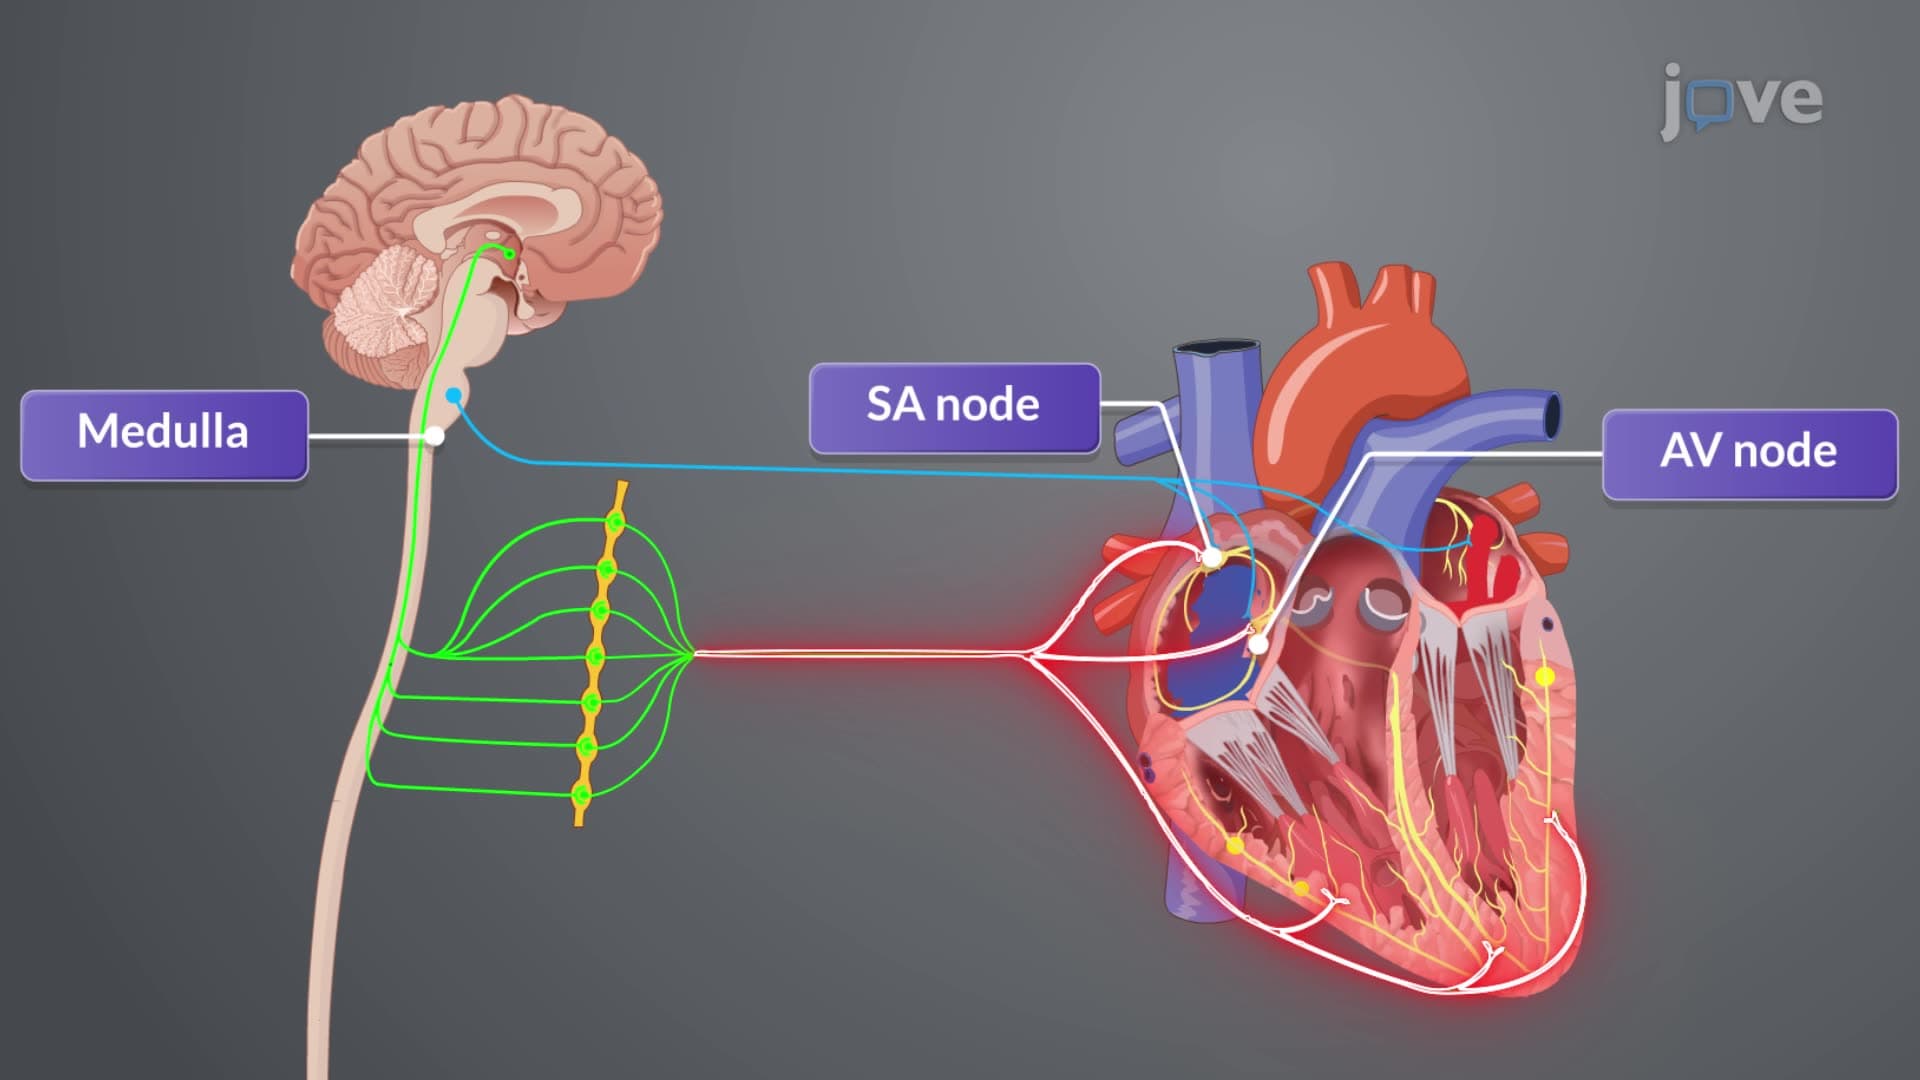
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...