Related Experiment Video
Updated: Dec 3, 2025
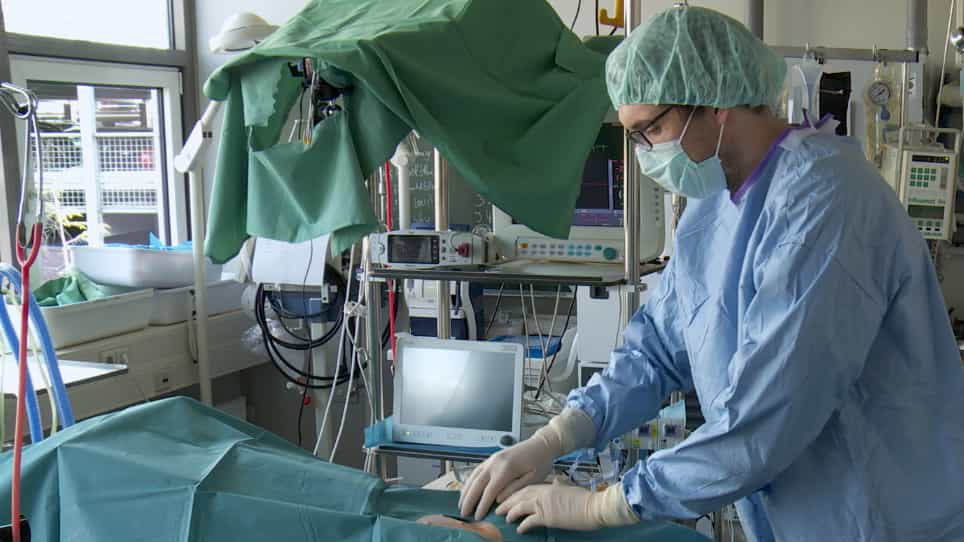
Standardized Hemorrhagic Shock Induction Guided by Cerebral Oximetry and Extended Hemodynamic Monitoring in Pigs
Published on: May 21, 2019
Regional venous-arterial CO2 to arterial-venous O2 content difference ratio in experimental circulatory shock and
Thiago Domingos Corrêa1,2, Adriano José Pereira3,4,5, Jukka Takala6
1Department of Intensive Care Medicine, Inselspital, Bern University Hospital, University of Bern, Bern, Switzerland. thiago.correa@einstein.br.

Background:
Venous-arterial carbon dioxide (CO2) to arterial-venous oxygen (O2) content difference ratio (Cv-aCO2/Ca-vO2) > 1 is supposed to be both sensitive and specific for anaerobic metabolism. What regional hemodynamic and metabolic parameters determine the ratio has not been clarified.
Objectives:
To address determinants of systemic and renal, spleen, gut and liver Cv-aCO2/Ca-vO2.
Methods:
Post hoc analysis of original data from published experimental studies aimed to address effects of different fluid resuscitation strategies on oxygen transport, lactate metabolism and organ dysfunction in fecal peritonitis and endotoxin infusion, and from animals in cardiac tamponade or hypoxic hypoxia. Systemic and regional hemodynamics, blood flow, lactate uptake, carbon dioxide and oxygen-derived variables were determined. Generalized estimating equations (GEE) were fit to assess contributors to systemic and regional Cv-aCO2/Ca-vO2.
Results:
Median (range) of pooled systemic Cv-aCO2/Ca-vO2 in 64 pigs was 1.02 (0.02 to 3.84). While parameters reflecting regional lactate exchange were variably associated with the respective regional Cv-aCO2/Ca-vO2 ratios, only regional ratios were independently correlated with systemic ratio: renal Cv-aCO2 /Ca-vO2 (β = 0.148, 95% CI 0.062 to 0.234; p = 0.001), spleen Cv-aCO2/Ca-vO2 (β = 0.065, 95% CI 0.002 to 0.127; p = 0.042), gut Cv-aCO2/Ca-vO2 (β = 0.117, 95% CI 0.025 to 0.209; p = 0.013), liver Cv-aCO2/Ca-vO2 (β = - 0.159, 95% CI - 0.297 to - 0.022; p = 0.023), hepatosplanchnic Cv-aCO2/Ca-vO2 (β = 0.495, 95% CI 0.205 to 0.786; p = 0.001).
Conclusion:
In a mixed set of animals in different shock forms or during hypoxic injury, hepatosplanchnic Cv-aCO2/Ca-vO2 ratio had the strongest independent association with systemic Cv-aCO2/Ca-vO2, while no independent association was demonstrated for lactate or hemodynamic variables.

Related Concept Videos
 01:04
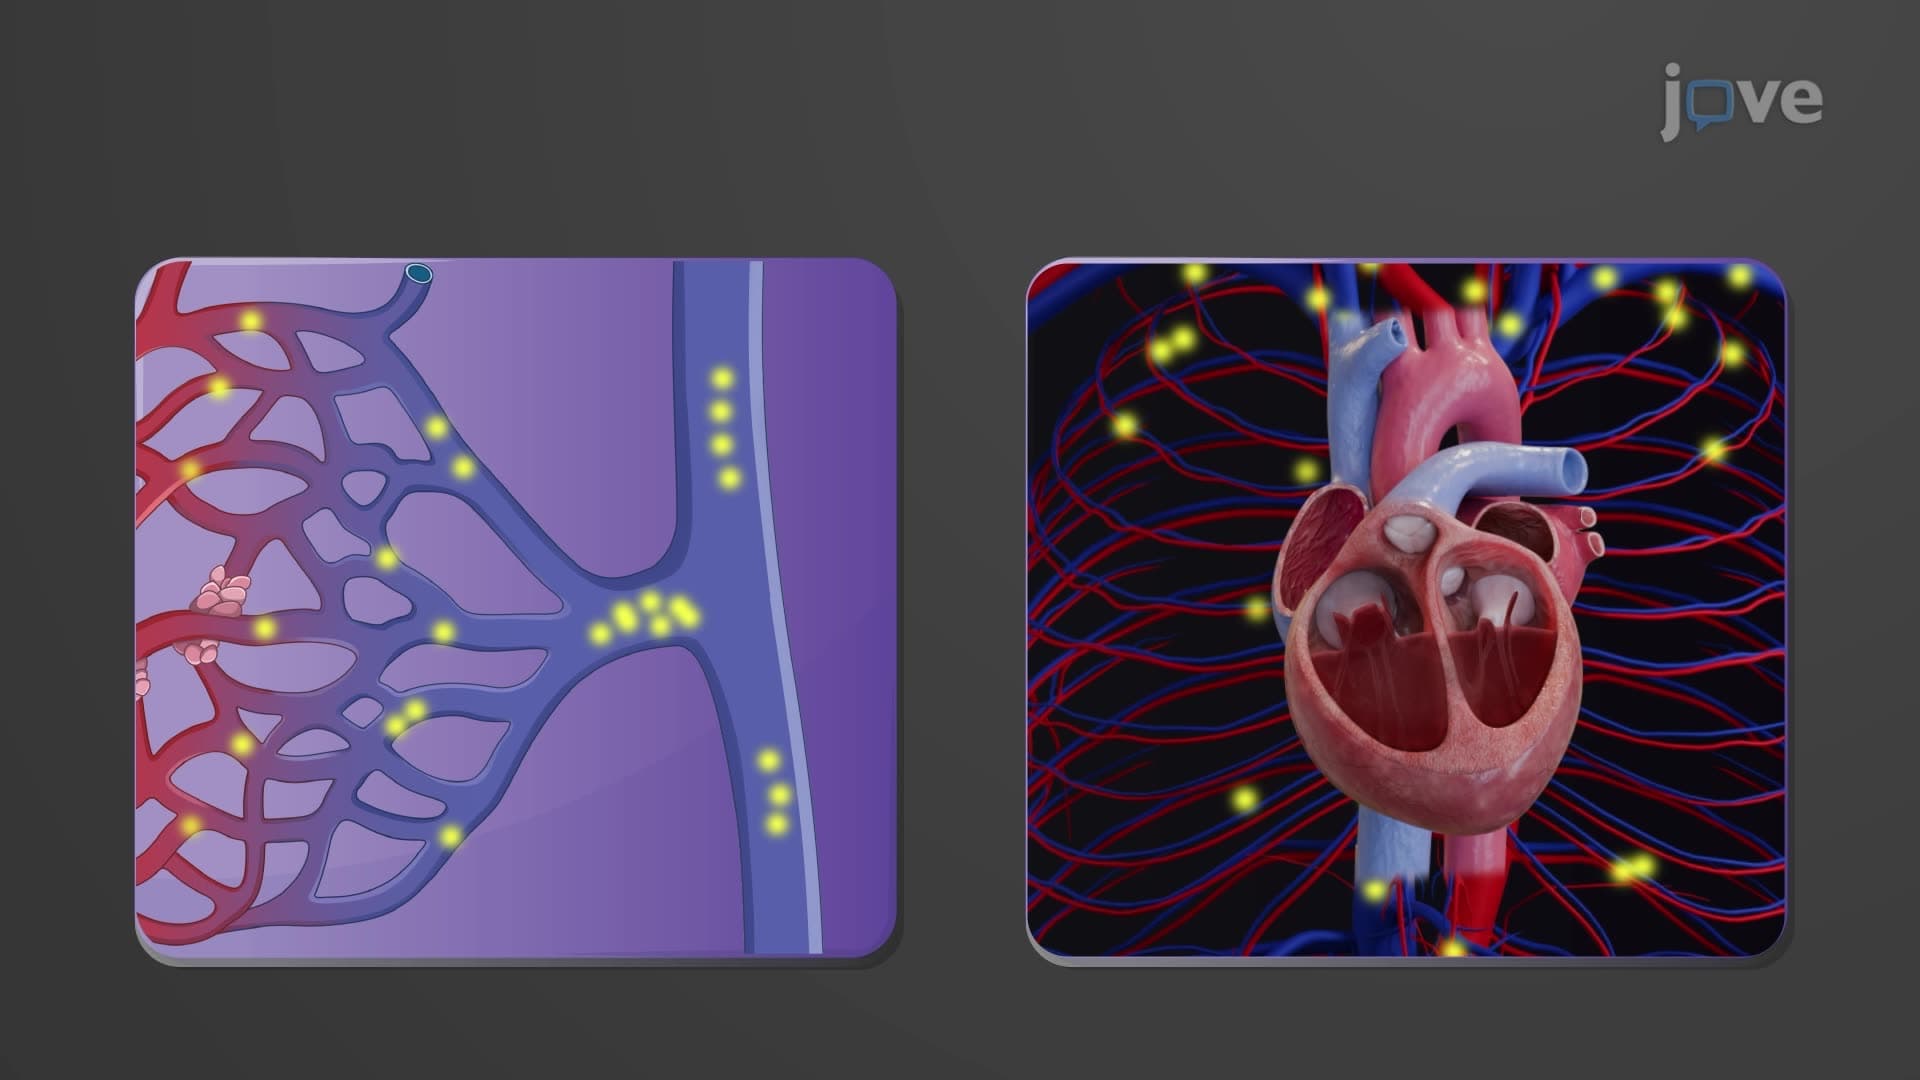
Venous Return
What is Venous Return?
Venous return refers to the rate at which blood flows back to the heart from the body's peripheral veins. It's an integral part of the circulatory system...
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this...
 01:27
Oxygen Transport in the Blood
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:26
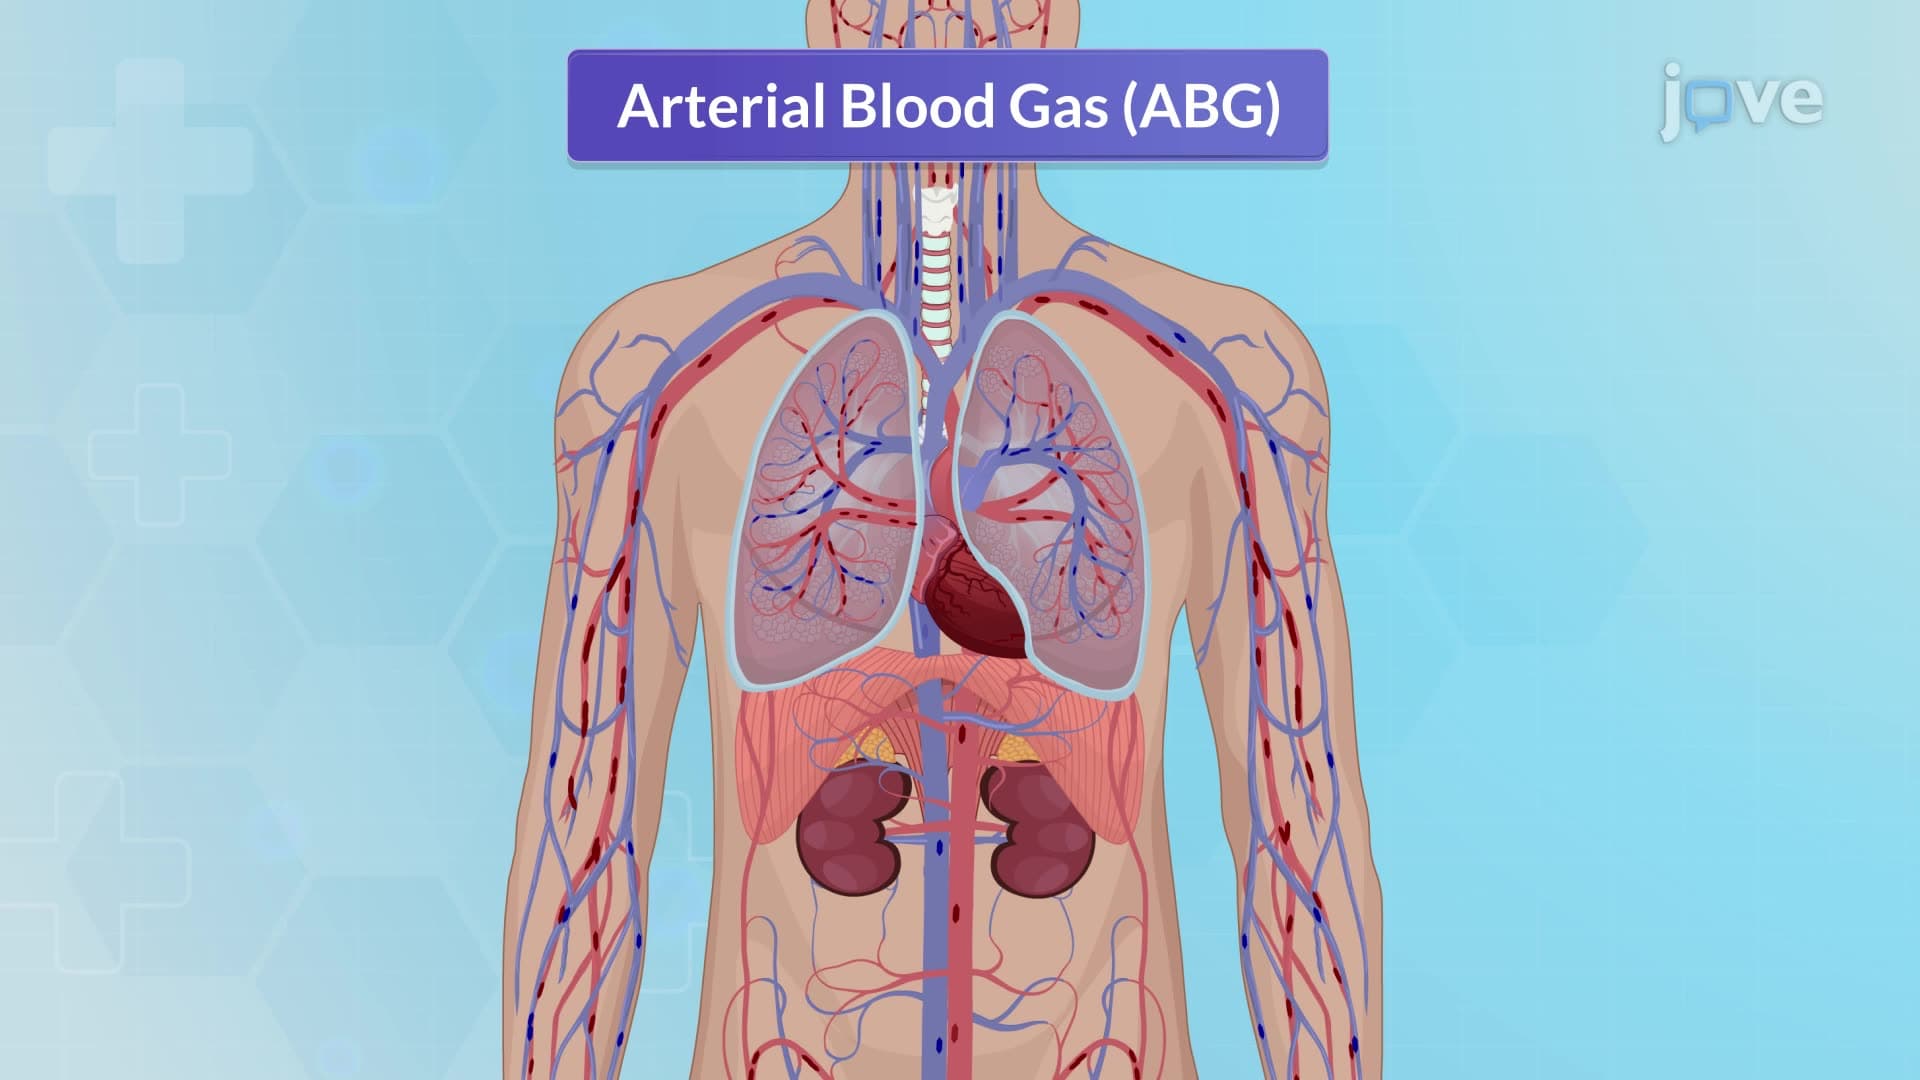
Blood Studies I: ABG and VBG
Arterial Blood Gas (ABG)
Arterial Blood Gas (ABG) studies are crucial for assessing the lungs' ability to supply oxygen and remove carbon dioxide, reflecting the patient's ventilation status. They also help understand the kidneys' capacity to...