Related Experiment Video
Updated: Dec 2, 2025


Quantitative Analysis and Characterization of Atherosclerotic Lesions in the Murine Aortic Sinus
Published on: December 7, 2013
The pathology of Kawasaki disease aortitis: a study of 37 cases
Wakana Sato1, Yuki Yokouchi1, Toshiaki Oharaseki1
1Department of Surgical Pathology (Ohashi), Toho University Graduate School of Medicine, Tokyo, Japan.

Insights
Kawasaki disease (KD) causes aortic inflammation, primarily involving macrophages and progressing through different layers. While aortic inflammation occurs, it does not lead to aneurysms or architectural destruction in KD patients.
Area of Science:
- Cardiovascular Pathology
- Pediatric Rheumatology
- Immunology
Background:
- Kawasaki disease (KD) is a pediatric systemic vasculitis primarily affecting coronary arteries.
- Aortic involvement in KD remains understudied, lacking detailed temporal and site-specific analyses.
- This study investigates aortic pathology in KD autopsy cases.
Purpose of the Study:
- To elucidate the time-course of aortic lesions in Kawasaki disease.
- To compare inflammatory cell types and infiltration degrees across different aortic sites.
- To examine the progression of inflammation within the aortic wall.
Main Methods:
- Histological analysis of aortic specimens from 37 KD autopsy cases (19 acute, 18 remote phase).
- Evaluation of three aortic sites: thoracic aorta, aortic root, and aortic bifurcation.
- Assessment of inflammatory cell infiltration, vasa vasorum involvement, and progression patterns.
Main Results:
- Inflammatory cell infiltration, mainly CD163-positive macrophages, was present in 90% of acute-phase cases, peaking around day 18.
- Aortic root and bifurcation showed more severe inflammation than the thoracic aorta.
- Inflammation progressed from adventitia to media via vasa vasorum and direct intimal spread, without vascular destruction or aneurysm formation.
Conclusions:
- Kawasaki disease induces aortic inflammation with a temporal profile and cellular infiltrate similar to coronary arteries.
- Inflammation severity varies across aortic sites, with greater impact on the aortic root and bifurcation.
- Unlike coronary arteries, KD-associated aortic inflammation in this study did not result in aneurysms or architectural damage.
Background:
Kawasaki disease (KD) is a systemic vasculitis syndrome that occurs most frequently in children. Most clinical and pathological studies have focused on its coronary artery lesions. To date, no detailed studies of the aorta have been conducted. We studied KD autopsy cases with the aims of clarifying the time-course of changes in aortic lesions, the differences in the inflammatory cells and degree of inflammation at various aortic sites, and the progression of the inflammation.
Materials And Methods:
The study materials were aortic specimens taken from 37 KD autopsy cases (acute phase: 19; remote phase: 18). Twenty-seven of the cases also had coronary aneurysms. We chose 3 aortic sites, i.e., the thoracic aorta, aortic root and aortic bifurcation, and we histologically observed and compared those sites in regard to the changes with time, the kinds of infiltrating cells and the number of inflammatory cells. We also observed the relationship between the vasa vasorum and inflammatory cell localization in the tunica media, and examined the progression of inflammation in the tunica media.
Results:
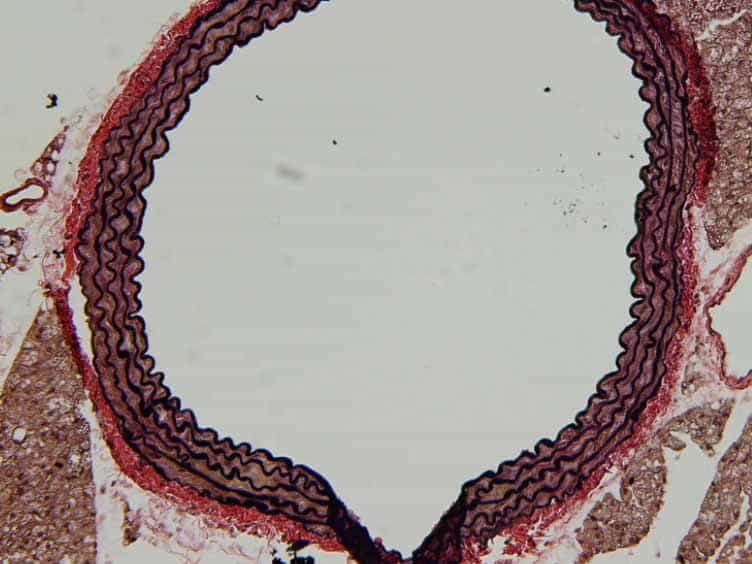
Destruction of the vascular architecture was not seen in any of the 37 cases, but inflammatory cell infiltration was observed in 90% of the acute-phase cases. The inflammatory cell infiltration involved the tunica intima and tunica adventitia of the aorta on the 6th disease-day, and all layers of the aorta on the 13th disease-day; the infiltration peaked on the 18th disease-day. The infiltration gradually disappeared thereafter, and no significant infiltration was seen in the remote phase. The infiltrating inflammatory cells consisted mainly of CD163-positive macrophages. Comparison of the 3 sites of the aorta showed that the inflammatory cell infiltration was more severe in the aortic root and aortic bifurcation than in the thoracic aorta. The progression of inflammation to the aortic tunica media from the adventitia showed 2 patterns: 1 in which macrophages were aggregated around the vasa vasorum; and a second in which there was no such aggregation around the vasa vasorum, but there was diffuse inflammatory cell infiltration of the tunica media. In addition to this, there were findings of direct infiltration of cells from the tunica intima into the tunica media.
Conclusion:
Inflammation in KD occurs in the aorta. The changes with time and the kinds of infiltrating cells were the same as reported to date for coronary arteries in KD. There were differences in the degree of inflammation among the 3 aortic sites. It can be thought that the inflammation from the adventitia to the media progresses via the vas vasorum, and also, there is a possibility of spreading directly. From the intima to the media, inflammation spreads directly. However, formation of aneurysms and destruction of the vascular architecture of the aorta were absent in this study, unlike in coronary arteries.
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:23
Rheumatic Heart Disease I: Introduction
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:15
Aortic Regurgitation I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests