Related Experiment Video
Updated: Dec 1, 2025


Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Syndrome of the trephined: A rare challenge in head & neck reconstruction
Erica Christenson1, Sean Figy2, Urvashi Upadhyay3
1University of Massachusetts Medical School, Worcester, MA, USA.

Background:
Syndrome of the trephined (ST) refers to the rare, reversible event of neurological deterioration following craniectomy. ST is also known as "sinking skin flap syndrome" and typically occurs in the weeks to months following operation. The mechanism underlying syndromic onset is poorly understood. Changes to cerebrospinal fluid flow, alteration of temperature-related perfusion, and scarring at the intracranial surgical site have all been proposed. Patients present with a variety of symptoms related to paradoxical increased intracranial pressure. Sometimes falsely attributed as a consequence of the initial cranial insult, ST is more specifically a symptomatic process resulting as direct consequence of the craniectomy procedure. With timely identification and subsequent cranioplasty, the associated neurological dysfunction can be corrected - this rectification being the primary confirmatory feature of the syndrome.
Case:
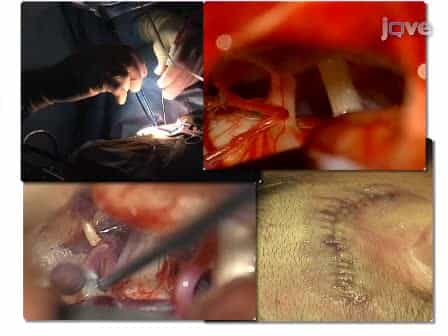
A 59-year-old female was seen with regards to a wound of the temporoparietal scalp, with exposed cranial implant. She had suffered a traumatic brain injury and underwent craniectomy after a motor vehicle accident 10 years prior. Her injury was complicated by necrosis of her cranial bone flap after reimplantation and at least 10 subsequent attempts to reconstruct her wound. When delayed cranial reconstruction was attempted on two separate occasions, the patient suffered severe syndrome of the trephined and required hospitalization for symptoms of impending herniation. Ultimately, she required revision and replacement of titanium mesh and latissimus dorsi free flap for soft tissue coverage of the titanium mesh.
Conclusion:
This case presents a unique surgical challenge in that chronic infection was perpetuated by the replacement of implant material in the wound. Soft tissue reconstruction alone was not possible given the patient's severe ST. Free tissue transfer was required in order to bring vascularized myofascial tissue to prevent recolonization of the newly implanted mesh and allow the cranial wound to heal.
Related Concept Videos
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...