Related Experiment Video
Updated: Nov 28, 2025
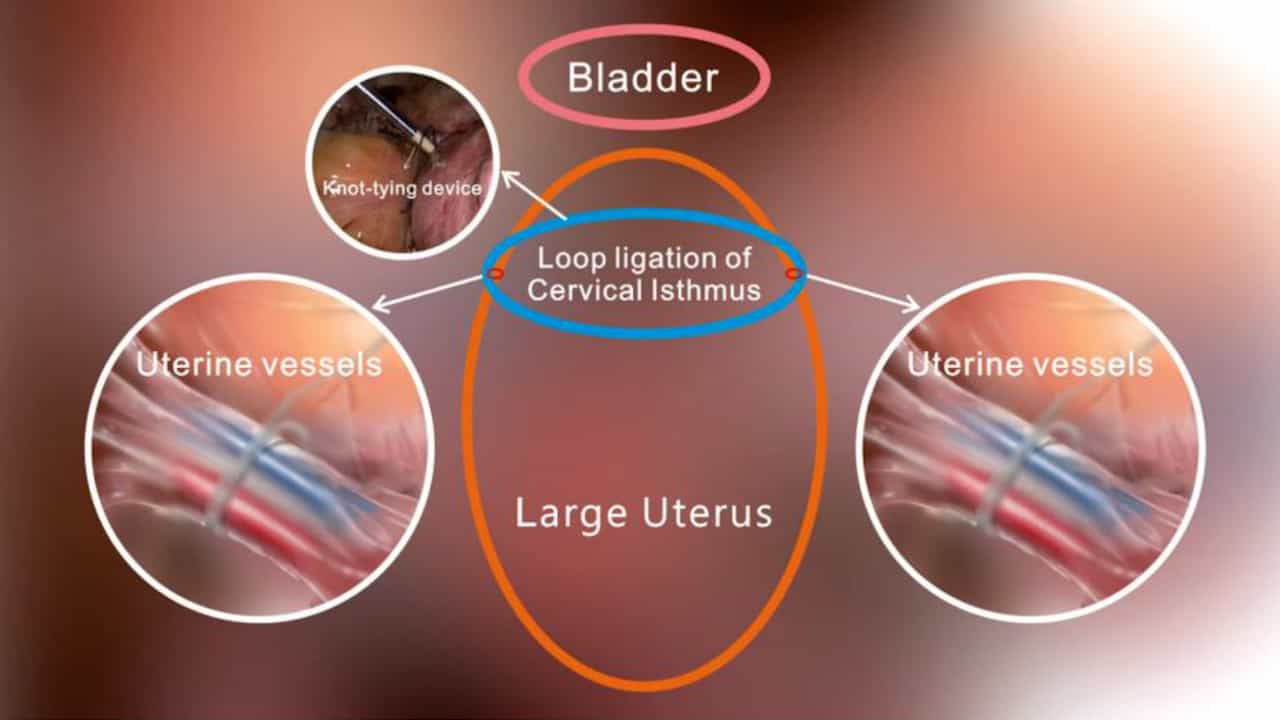

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Laparoscopic emergency cervicoisthmic cerclage in second trimester of pregnancy: A case series report
Andreas Kavallaris1, Antonios Gkoutzioulis1, Dimitrios Zygouris1
1Department of Minimally Invasive Gynecology, St Luke's Hospital, Thessaloniki, Greece.

Purpose:
The aim of this study was to evaluate the feasibility and safety of Laparoscopic emergency cervicoisthmic cerclage in second trimester of pregnancy.
Methods:
Between November 2015 and March 2019 5 patients underwent Laparoscopic emergency cervicoisthmic cerclage. All women had showed cervical insufficiency with dilation in the second trimester due to extensive conisation (3 patients) or re-conisation (2 patients) and failed transvaginal cerclage (5 patients) due to a short vaginal cervix. Patients' characteristics were obtained from hospital's medical record and we evaluated surgical data, intra, postoperative complications, and perinatal outcome. All operations were performed by the same surgeon.
Results:
The average operation time was 88 min (ranging from 80 to 95 minutes), the average estimated blood loss during the procedure was less than 100 mL and there were no perioperative or postoperative complications. The mean gestational age at surgery was 14.4 (ranging from 14.2 to 16) weeks. All women underwent an elective CS after 38 weeks of gestation. The overall pregnancy survival rate was 100 %, the mean gestational age at delivery was 38.1 weeks (ranging from 38.0 to 38.5 weeks) and the mean birth weight was 3190 g (g) (ranging from 2980 g to 3350 g).
Conclusion:
Laparoscopic cervicoisthmic cerclage might be an alternative approach even in the early second trimester of pregnancy. Our study's success rates compare favourably to the laparotomy approach and the laparoscopic cervicoisthmic cerclage showed a relatively high success rate in women who are at risk of poor obstetric outcomes. Of course, the surgeon's experience and competence plays a key role and this approach should only be attempted in well-organized units.