Related Experiment Video
Updated: Nov 27, 2025


Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
Constrictive bronchiolitis in diffuse idiopathic pulmonary neuroendocrine cell hyperplasia
Bilal F Samhouri1, Natalya Azadeh2, Thorvardur R Halfdanarson3
1Dept of Pulmonary and Critical Care Medicine, Mayo Clinic, Rochester, MN, USA.

Background:
Diffuse idiopathic pulmonary neuroendocrine cell hyperplasia (DIPNECH) is characterised by multifocal proliferation of neuroendocrine cells and belongs in the spectrum of pulmonary neuroendocrine tumours. Some patients with DIPNECH develop airflow obstruction but the relationship between the two entities remains unclear.
Methods:
We performed a computer-assisted search of the Mayo Clinic's electronic medical records for biopsy-proven cases of DIPNECH. We extracted clinical, pulmonary function, imaging and histopathological data along with treatments and outcomes.
Results:
Among 44 patients with DIPNECH 91% were female and the median age was 65 years (interquartile range 56-69 years); 73% were never-smokers. Overall, 38 patients (86%) had respiratory symptoms including cough (68%) and dyspnoea (30%); 45% were previously diagnosed to have asthma or COPD. Pulmonary function testing showed an obstructive pattern in 52%, restrictive pattern in 11%, mixed pattern in 9%, nonspecific pattern in 23%, and was normal in 5%. On chest computed tomography scan, 95% manifested diffuse nodules and 77% manifested mosaic attenuation. For management, 25% of patients were observed without pharmacological therapy, 55% received an inhaled bronchodilator, 41% received an inhaled corticosteroid, 32% received octreotide; systemic steroids, azithromycin, or combination chemotherapy was employed in four patients (9%). Of 24 patients with available follow-up pulmonary function tests, 50% remained stable, 33% worsened and 17% improved over a median interval of 21.3 months (interquartile range 9.7-46.9 months).
Conclusion:
DIPNECH occurs mostly in women and manifests diffuse pulmonary nodules and mosaic attenuation on imaging. It is commonly associated with airflow obstruction due to constrictive bronchiolitis, which manifests limited response to current pharmacological therapy.


Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:17
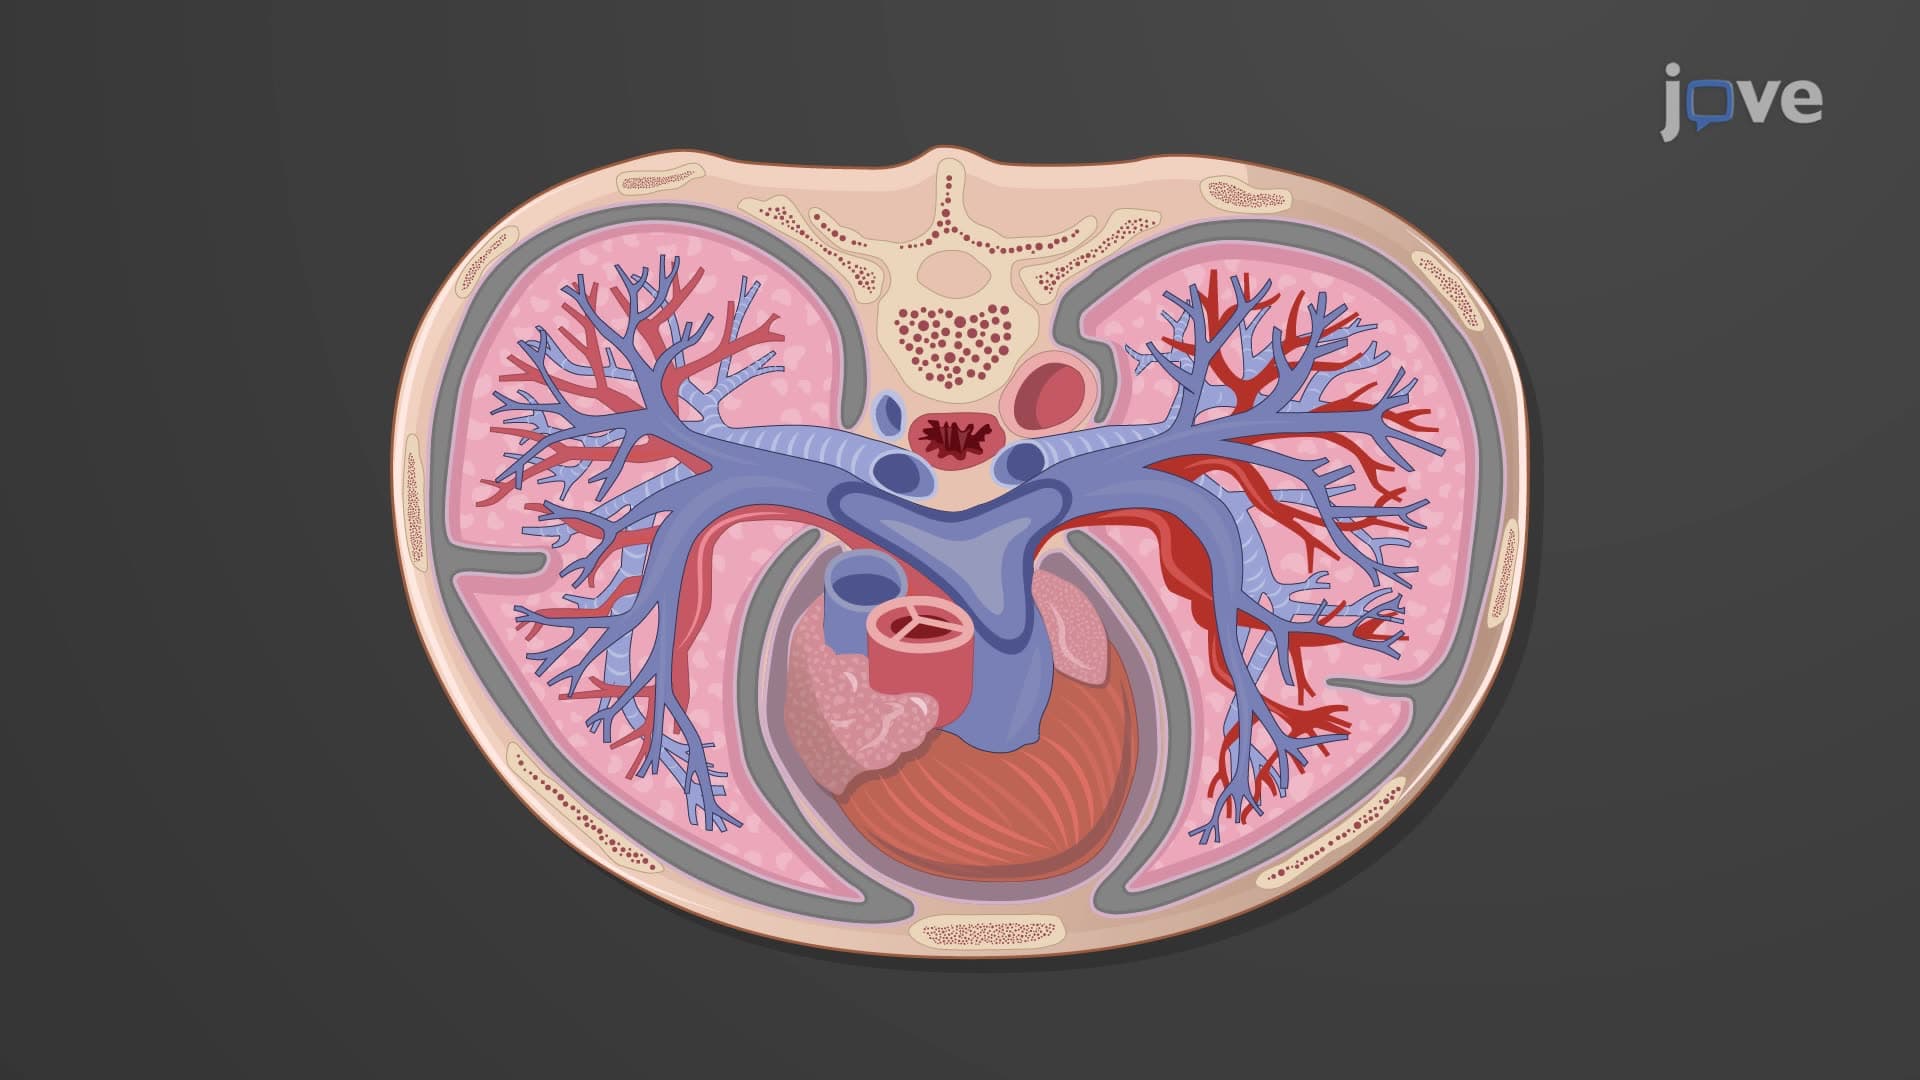
Gross Anatomy of the Lungs
 01:23
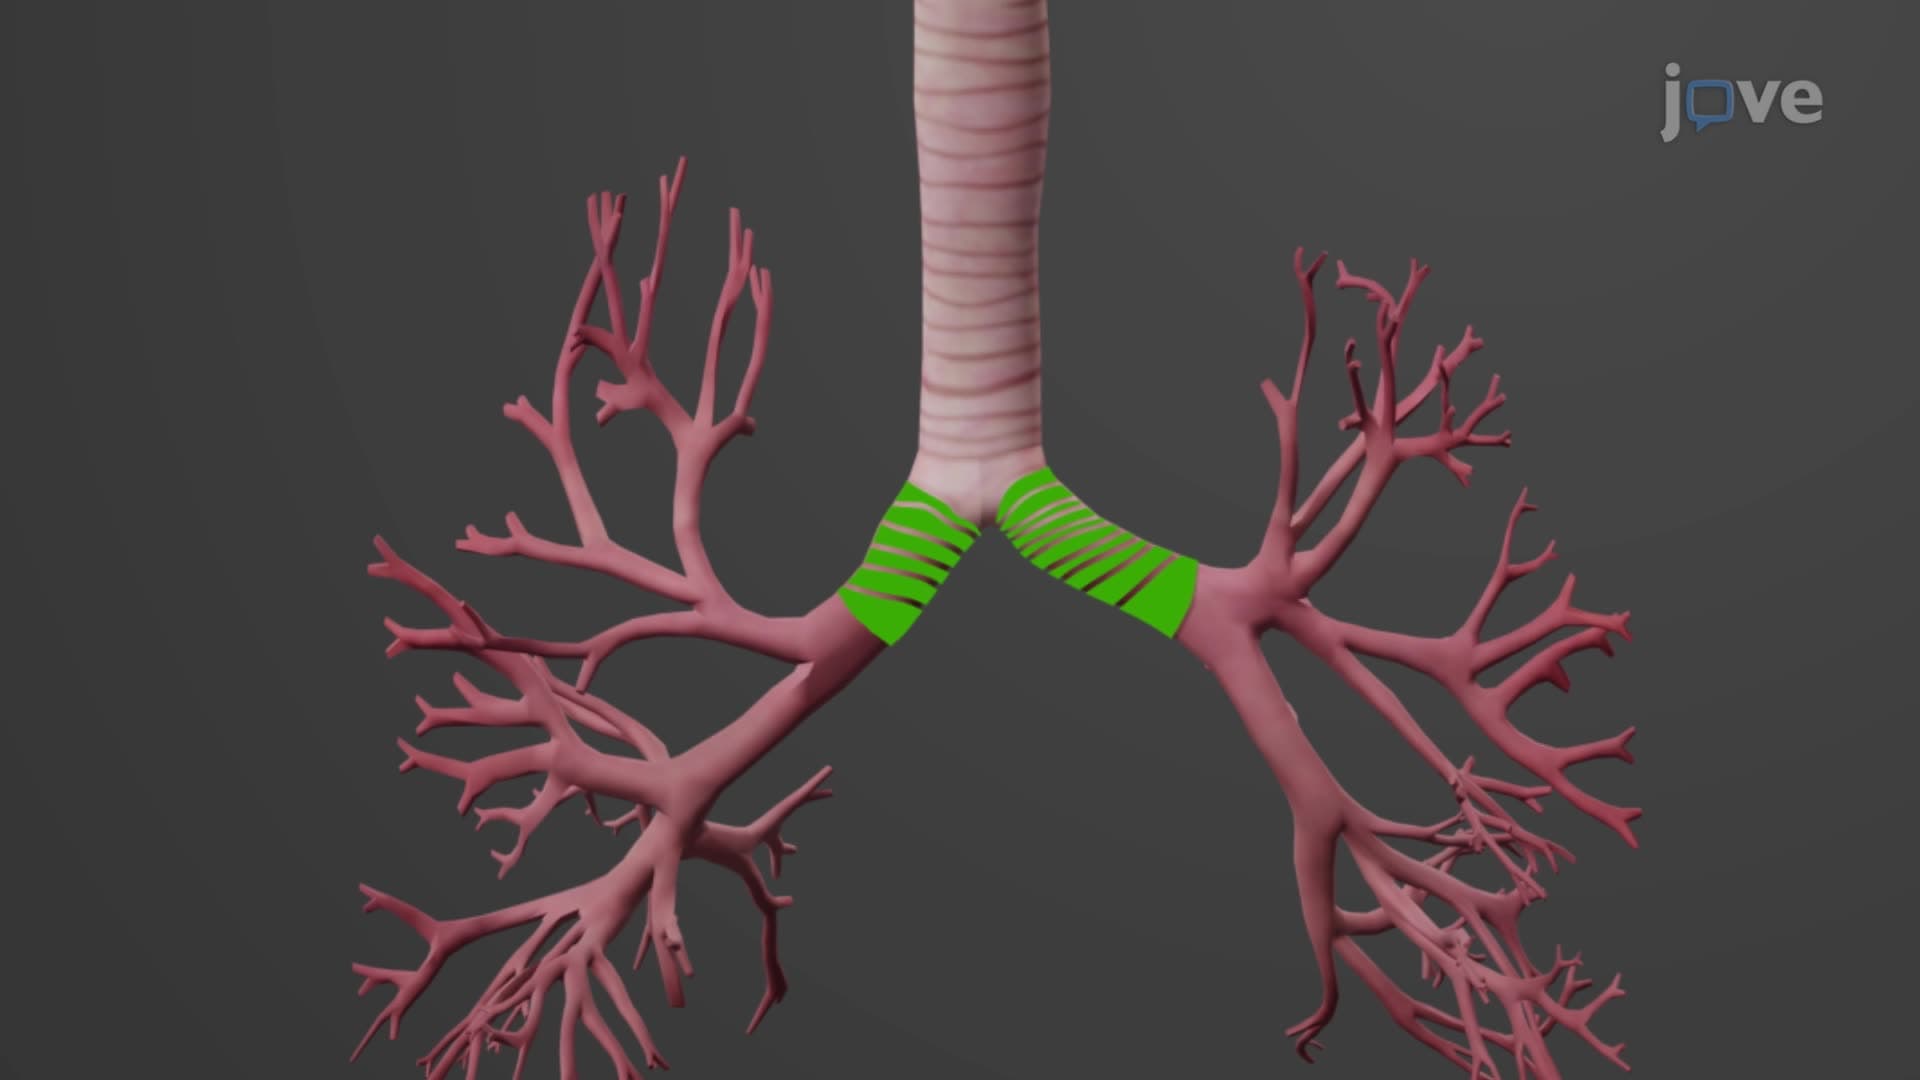
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...