Related Experiment Video
Updated: Nov 27, 2025
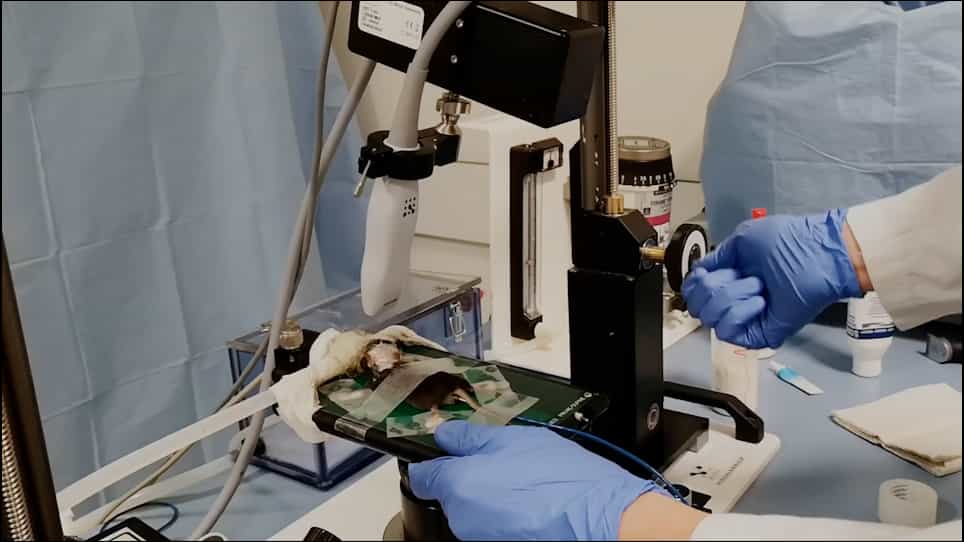

Analysis of Cerebral Vasospasm in a Murine Model of Subarachnoid Hemorrhage with High Frequency Transcranial Duplex Ultrasound
Published on: June 3, 2021
Neurovascular disease, diagnosis, and therapy: Subarachnoid hemorrhage and cerebral vasospasm
Nima Etminan1, R Loch Macdonald2
1Department of Neurosurgery, University Hospital Mannheim, University of Heidelberg, Mannheim, Germany.

The worldwide incidence of spontaneous subarachnoid hemorrhage is about 6.1 per 100,000 cases per year (Etminan et al., 2019). Eighty-five percent of cases are due to intracranial aneurysms. The mean age of those affected is 55 years, and two-thirds of the patients are female. The prognosis is related mainly to the neurologic condition after the subarachnoid hemorrhage and the age of the patient. Overall, 15% of patients die before reaching the hospital, another 20% die within 30 days, and overall 75% are dead or remain disabled. Case fatality has declined by 17% over the last 3 decades. Despite the improvement in outcome probably due to improved diagnosis, early aneurysm repair, administration of nimodipine, and advanced intensive care support, the outcome is not very good. Even among survivors, 75% have permanent cognitive deficits, mood disorders, fatigue, inability to return to work, and executive dysfunction and are often unable to return to their premorbid level of functioning. The key diagnostic test is computed tomography, and the treatments that are most strongly supported by scientific evidence are to undertake aneurysm repair in a timely fashion by endovascular coiling rather than neurosurgical clipping when feasible and to administer enteral nimodipine. The most common complications are aneurysm rebleeding, hydrocephalus, delayed cerebral ischemia, and medical complications (fever, anemia, and hyperglycemia). Management also probably is optimized by neurologic intensive care units and multidisciplinary teams.
The worldwide incidence of spontaneous subarachnoid hemorrhage is about 6.1 per 100,000 cases per year (Etminan et al., 2019). Eighty-five percent of cases are due to intracranial aneurysms. The mean age of those affected is 55 years, and two-thirds of the patients are female. The prognosis is related mainly to the neurologic condition after the subarachnoid hemorrhage and the age of the patient. Overall, 15% of patients die before reaching the hospital, another 20% die within 30 days, and overall 75% are dead or remain disabled. Case fatality has declined by 17% over the last 3 decades. Despite the improvement in outcome probably due to improved diagnosis, early aneurysm repair, administration of nimodipine, and advanced intensive care support, the outcome is not very good. Even among survivors, 75% have permanent cognitive deficits, mood disorders, fatigue, inability to return to work, and executive dysfunction and are often unable to return to their premorbid level of functioning. The key diagnostic test is computed tomography, and the treatments that are most strongly supported by scientific evidence are to undertake aneurysm repair in a timely fashion by endovascular coiling rather than neurosurgical clipping when feasible and to administer enteral nimodipine. The most common complications are aneurysm rebleeding, hydrocephalus, delayed cerebral ischemia, and medical complications (fever, anemia, and hyperglycemia). Management also probably is optimized by neurologic intensive care units and multidisciplinary teams.


Related Concept Videos
 01:16
Vascular Spasm
 01:22
Aneurysm IV: Nursing Management
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Aneurysm III: Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management