Related Experiment Video
Updated: Jul 25, 2026
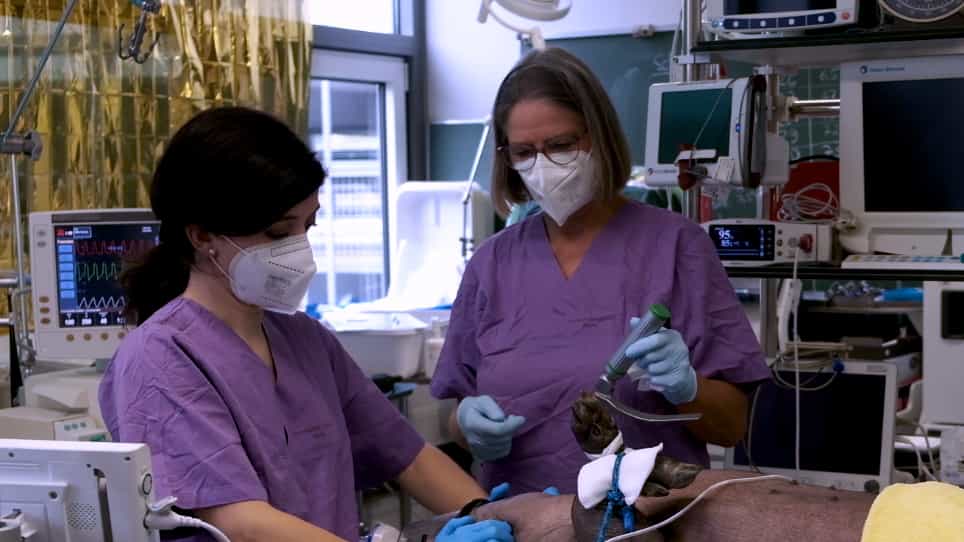
Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Evaluation of transmitted glow point at a priori chosen depth (1 cm below vocal cords) for lightwand intubation: a
Eunyoung Cho1, Hyun-Chang Kim2,3, Jung-Man Lee4
1Department of Anesthesiology and Pain Medicine, Keimyung University Dongsan Hospital, Keimyung University School of Medicine, Daegu, Korea.

Objective:
When performing lightwand intubation, an improper transmitted glow position before tube advancement can cause intubation failure or laryngeal injury. This study was performed to explore the transmitted glow point corresponding to a priori chosen depth for lightwand intubation.
Methods:
Before lightwand intubation, we marked the transmitted glow point from a bronchoscope on the neck when it reached 1 cm below the vocal cords. Lightwand intubation was then performed using this marking point. The distances from the mark to the upper border of the thyroid cartilage, upper border of the cricoid cartilage, and suprasternal notch were measured.
Results:
In total, 107 patients were enrolled. The success rate of lightwand intubation using the mark was 93.5% (95% confidence interval, 88.7%-99.2%) at the first attempt. The marking point was placed 12.0 mm (95% confidence interval, 10.6-13.4 mm) below the upper border of the cricoid cartilage.
Conclusion:
Anaesthesiologists should be aware of the appropriate point of the transmitted glow on the patient's neck when performing lightwand intubation. We suggest that this point is approximately 1 cm below the upper border of the cricoid cartilage.Trial registration: ClinicalTrials.gov NCT03480035.

Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Endoscopic Studies I: Bronchoscopy and Thoracoscopy
Bronchoscopy
Description
Bronchoscopy is a procedure that involves direct visualization of the larynx, trachea, and bronchi for diagnostic and therapeutic purposes. A flexible fiber optic or rigid bronchoscope is used to carry out the procedure. The fiber-optic bronchoscope is more frequently used due to...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:23
Tracheostomy Suctioning II: Procedure