Related Experiment Video
Updated: Nov 26, 2025


Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
Effect of Beta 3 Adrenoreceptor Modulation on Patency of the Ductus Arteriosus
Alessandro Pini1, Camilla Fazi2, Patrizia Nardini1
1Department of Experimental and Clinical Medicine, University of Florence, 50139 Florence, Italy.

Abstract:
β3-adrenoreceptor (β3-AR), a G-protein coupled receptor, has peculiar regulatory properties in response to oxygen and widespread localization. β3-AR is expressed in the most frequent neoplasms, also occurring in pregnant women, and its blockade reduces tumor growth, indicating β3-AR-blockers as a promising alternative to antineoplastic drugs during pregnancy. However, β3-AR involvement in prenatal morphogenesis and the consequences of its blockade for the fetus remain unknown. In this study, after the demonstrated expression of β3-AR in endothelial and smooth muscle cells of ductus arteriosus (DA), C57BL/6 pregnant mice were acutely treated at 18.5 of gestational day (GD) with indomethacin or with the selective β3-AR antagonist SR59230A, or chronically exposed to SR59230A from 15.5 to 18.5 GD. Six hours after the last treatment, fetuses were collected. Furthermore, newborn mice were treated straight after birth with BRL37344, a β3-AR agonist, and sacrificed after 7 h. SR59230A, at the doses demonstrated effective in reducing cancer progression (10 and 20 mg/kg) in acute and chronic mode, did not induce fetal DA constriction and did not impair the DA ability to close after birth, whereas at the highest dose (40 mg/kg), it was shown to cause DA constriction and preterm-delivery. BRL37344 administered immediately after birth did not alter the physiological DA closure.
Insights
Beta3-adrenoreceptor (β3-AR) blockade showed no adverse effects on fetal ductus arteriosus (DA) closure at therapeutic doses. However, high doses of the β3-AR antagonist SR59230A caused DA constriction and preterm birth in mice.
Area of Science:
- Pharmacology
- Developmental Biology
- Obstetrics
Background:
- The beta3-adrenoreceptor (β3-AR) is a G-protein coupled receptor with unique regulatory properties and widespread expression.
- β3-AR is found in common neoplasms and its blockade inhibits tumor growth, suggesting potential as an anti-neoplastic drug during pregnancy.
- The role of β3-AR in prenatal development and the fetal effects of its blockade are currently unknown.
Purpose of the Study:
- To investigate the effects of β3-adrenoreceptor blockade on fetal ductus arteriosus (DA) development and function.
- To assess the safety of β3-AR antagonists for fetal use during pregnancy.
- To determine the impact of β3-AR modulation on prenatal morphogenesis and postnatal DA closure.
Main Methods:
- Expression of β3-AR was confirmed in endothelial and smooth muscle cells of the fetal ductus arteriosus (DA).
- Pregnant mice were treated acutely or chronically with the selective β3-AR antagonist SR59230A or with indomethacin.
- Newborn mice were treated with the β3-AR agonist BRL37344 to assess its effect on DA closure.
Main Results:
- SR59230A, at doses effective for cancer treatment (10 and 20 mg/kg), did not cause fetal DA constriction or impair postnatal closure.
- A higher dose of SR59230A (40 mg/kg) induced DA constriction and preterm delivery in mice.
- Postnatal administration of the β3-AR agonist BRL37344 did not affect physiological DA closure.
Conclusions:
- Selective β3-AR blockade at therapeutically relevant doses is safe for fetal ductus arteriosus development and function.
- High doses of β3-AR antagonists may pose risks, including DA constriction and preterm birth.
- β3-AR modulation does not appear to interfere with normal physiological ductus arteriosus closure after birth.
More Related Videos
Related Concept Videos
 01:26
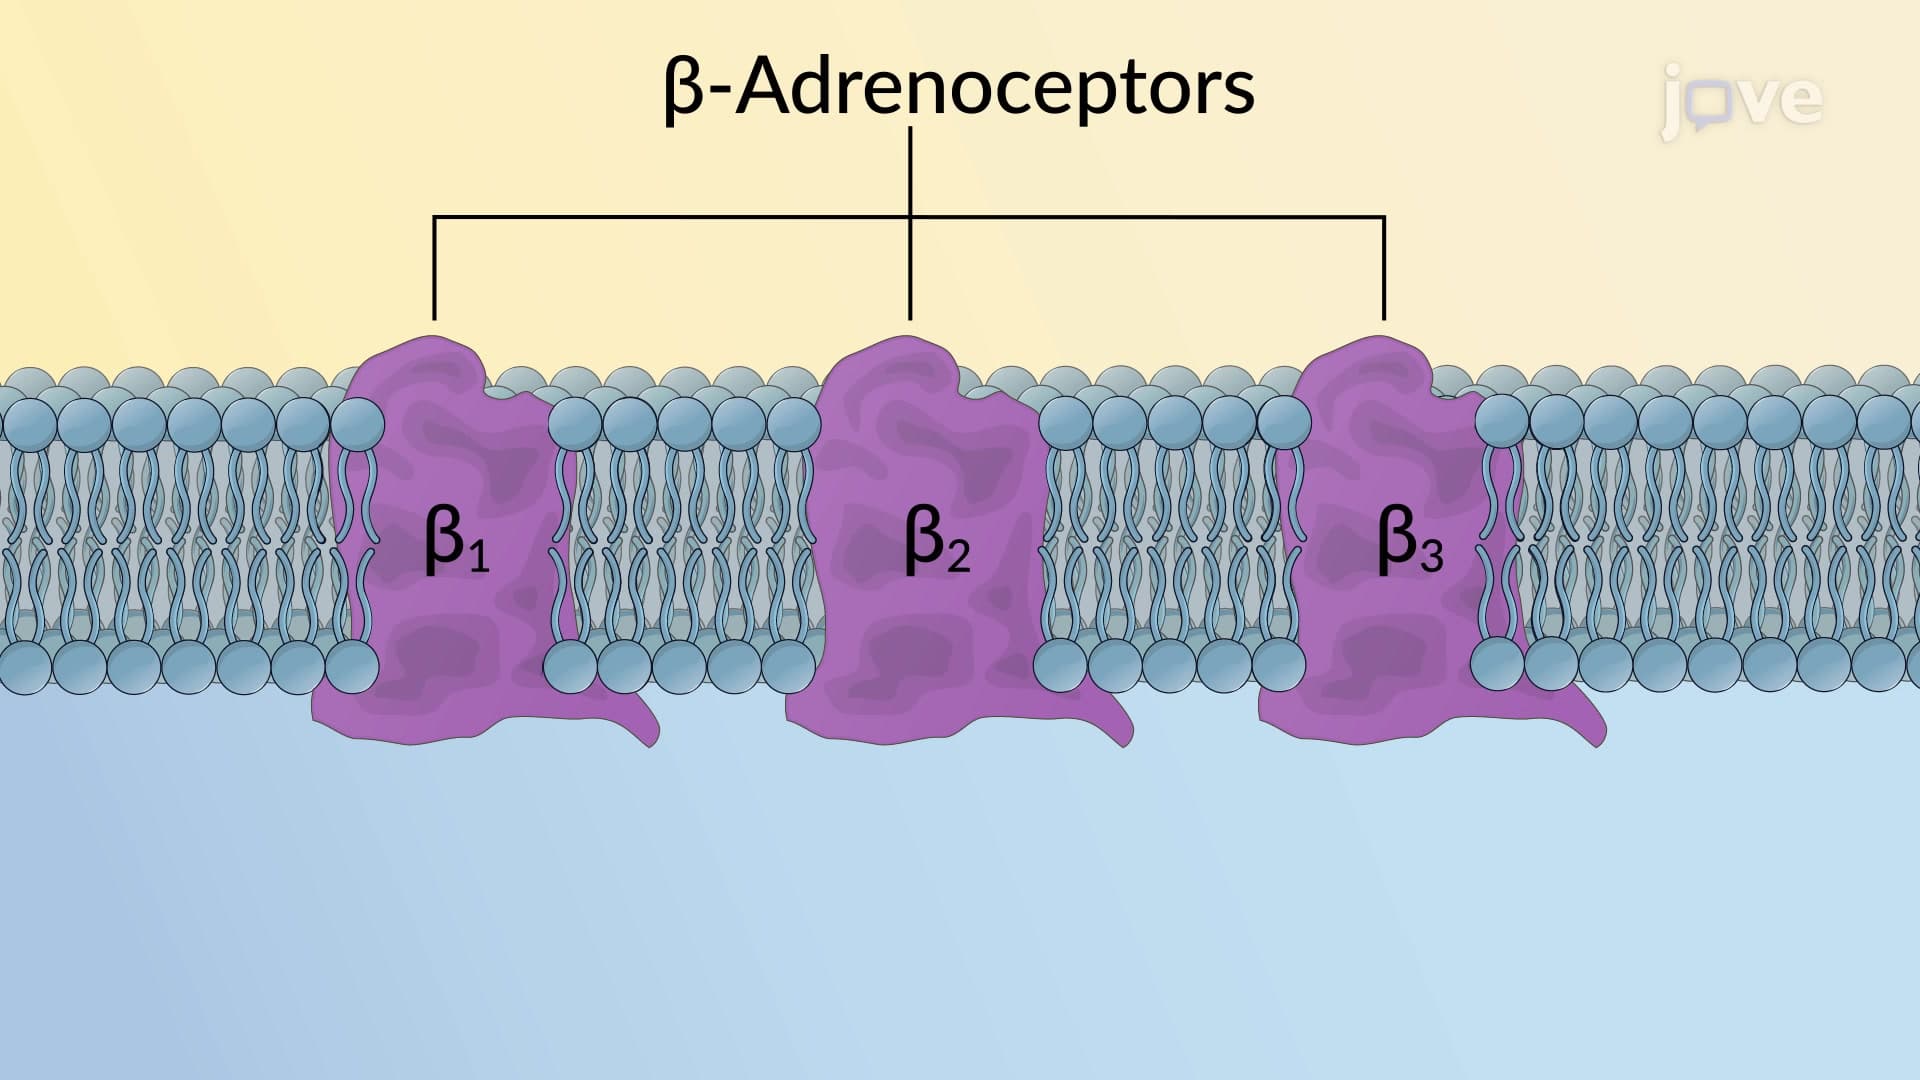
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
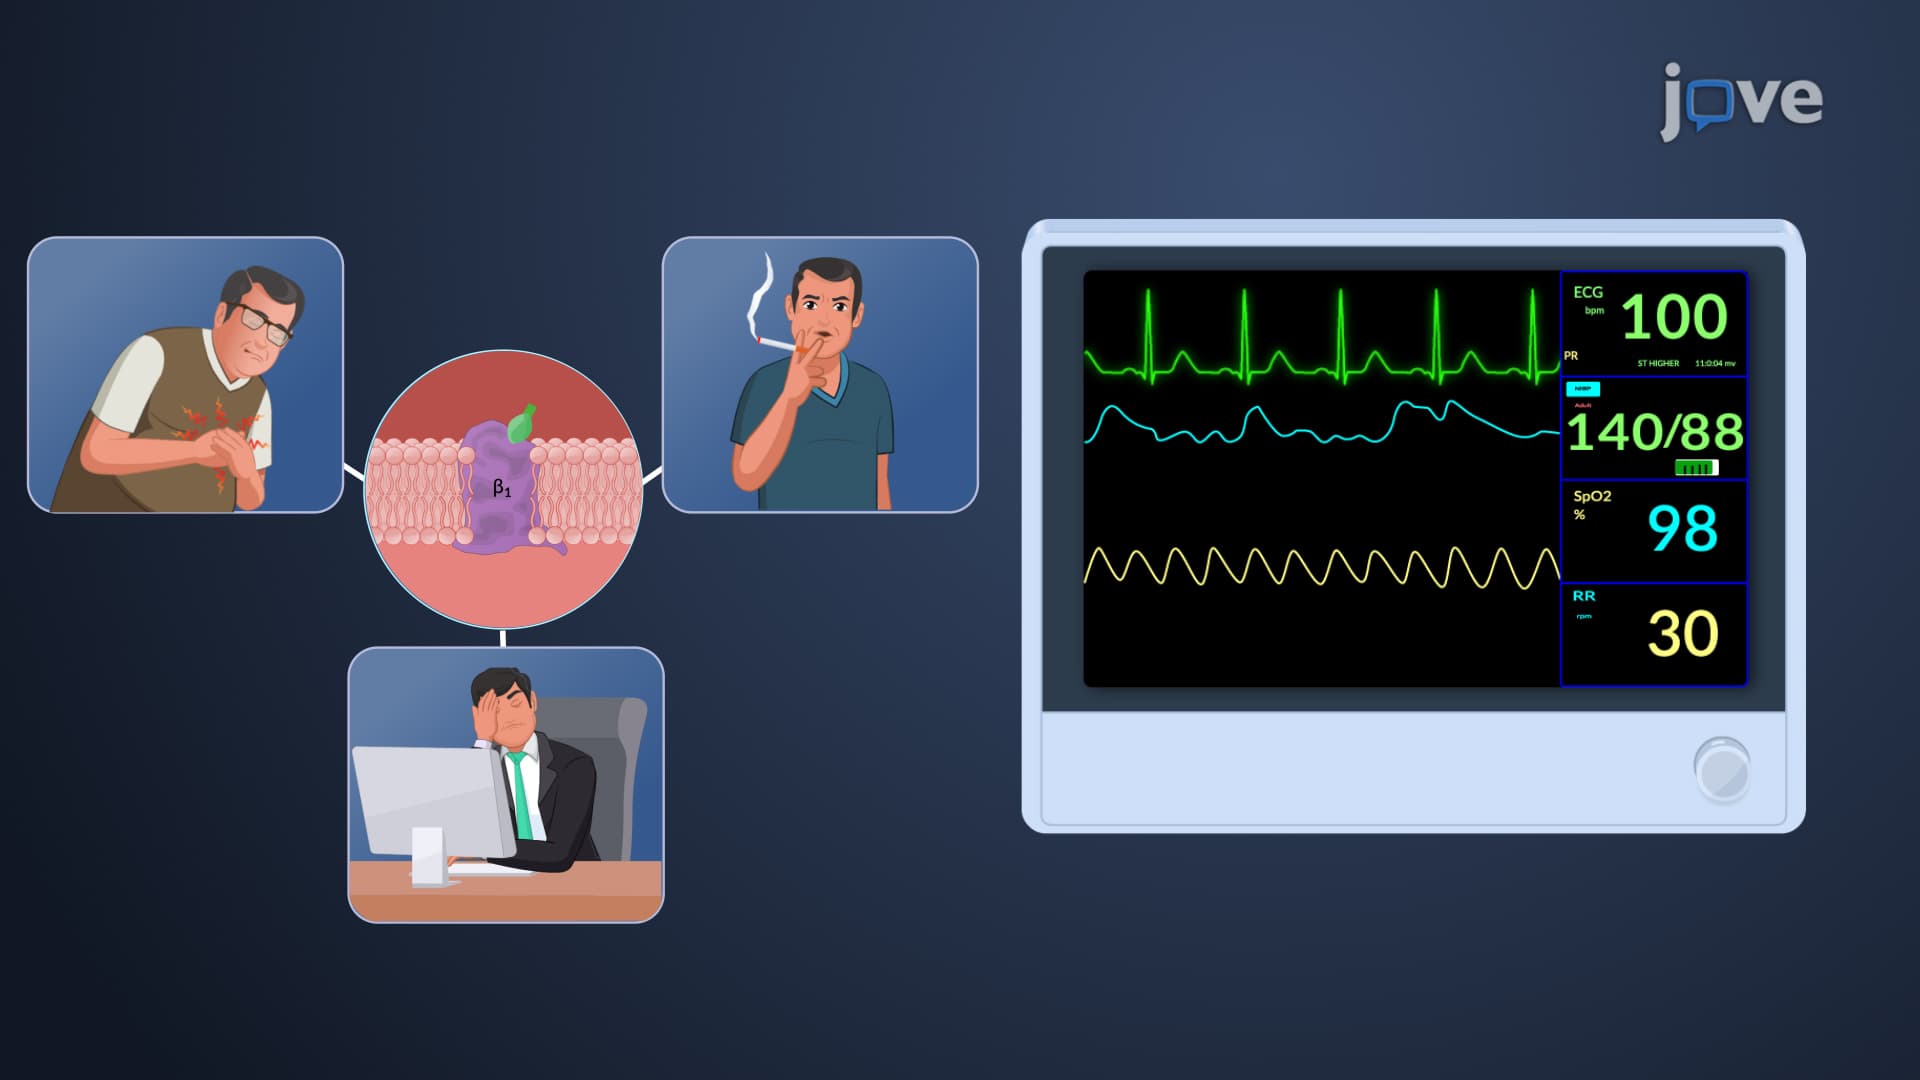
Antihypertensive Drugs: Action of β1 Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
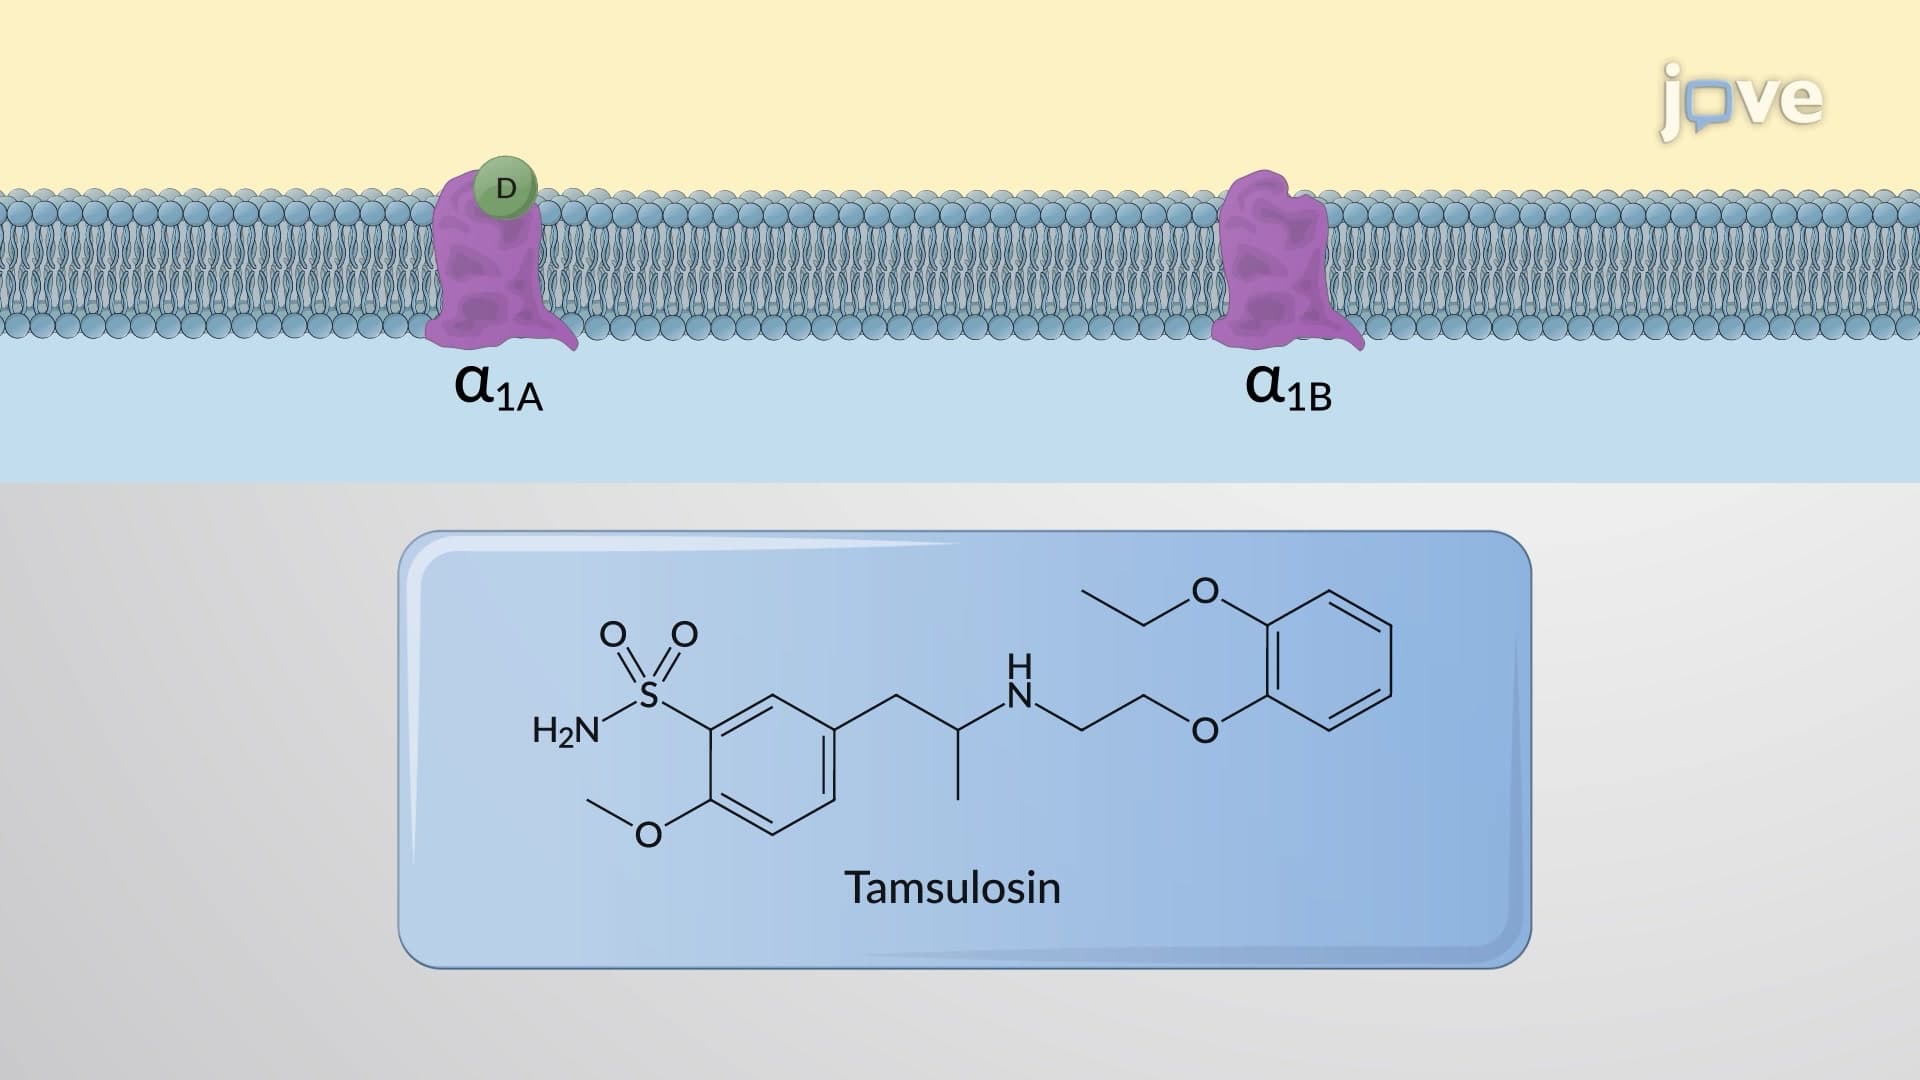 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers