Related Experiment Video
Updated: Aug 13, 2026


Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
Ectopic automatic atrial tachycardia in children: clinical characteristics, management and follow-up
A V Mehta1, G R Sanchez, E J Sacks
1Pediatric Heart Institute, St. Christopher's Hospital for Children, Philadelphia, Pennsylvania.

Insights
Ectopic automatic atrial tachycardia in children is often resistant to standard treatments. Intravenous propranolol and amiodarone effectively suppressed tachycardia in infants and children, predicting long-term oral therapy success.
Area of Science:
- Pediatric Cardiology
- Electrophysiology
- Arrhythmology
Background:
- Ectopic automatic atrial tachycardia (EAAT) is an uncommon supraventricular tachycardia.
- EAAT in pediatric patients often proves resistant to medical management.
- Surgical or cryoablation is frequently recommended for refractory cases.
Purpose of the Study:
- To describe the management and outcomes of 10 infants and children diagnosed with EAAT.
- To evaluate the efficacy of various antiarrhythmic agents in pediatric EAAT.
- To identify acute treatment strategies that predict long-term therapeutic response.
Main Methods:
- Retrospective analysis of 10 pediatric patients (median age 6 months) with EAAT.
- Assessment of treatment responses to digoxin, propranolol, Class I antiarrhythmics (quinidine, procainamide, phenytoin), and amiodarone.
- Evaluation of acute suppression and long-term control of tachycardia.
Main Results:
- Digoxin showed limited efficacy, decreasing heart rate by 5-20% in 8 patients.
- Propranolol (IV and oral) suppressed or controlled tachycardia in 5 out of 10 patients.
- Class I agents were ineffective and worsened tachycardia in 3 patients.
- Amiodarone (IV and oral) suppressed tachycardia in 4 out of 5 patients.
- Surgical and catheter ablation procedures had mixed success.
Conclusions:
- Intravenous propranolol and amiodarone demonstrated acute efficacy in suppressing pediatric EAAT.
- These acute responses predicted successful long-term oral therapy.
- EAAT resolved or was well-controlled in 8 out of 10 patients during follow-up.
Abstract:
Ectopic automatic atrial tachycardia, an uncommon type of supraventricular tachycardia in children and adults, has been reported to be resistant to medical therapy, and surgical or cryoblation has been recommended. This report describes 10 infants and children (median age 6 months; range birth to 7.5 years) with automatic atrial tachycardia and their management and follow-up. Digoxin alone was unsuccessful in controlling tachycardia in all 10 patients but decreased the tachycardia rate by 5 to 20% in 8. Intravenous (0.1 mg/kg body weight per dose) and oral propranolol successfully suppressed tachycardia in three of five patients and oral propranolol successfully controlled tachycardia in two of five other patients. Class I antiarrhythmic agents--quinidine (three patients), procainamide (four patients) and phenytoin (three patients)--did not control tachycardia in any patients but made the tachycardia rate worse in three patients. Intravenous (5 mg/kg per dose) and oral amiodarone suppressed tachycardia in three of four patients and oral amiodarone suppressed it in another patient. Thus, intravenous propranolol and amiodarone were effective in acutely suppressing automatic ectopic atrial tachycardia and predicted the response to long-term oral therapy. One patient had persistent tachycardia after surgical ablation of the high right atrial ectopic focus, and another patient had unsuccessful catheter ablation of the high right atrial ectopic focus (25 J). During follow-up (10 to 28 months), ectopic atrial tachycardia resolved completely in four patients and was well controlled in four patients.


Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:29
Disturbances in Heart Rhythm
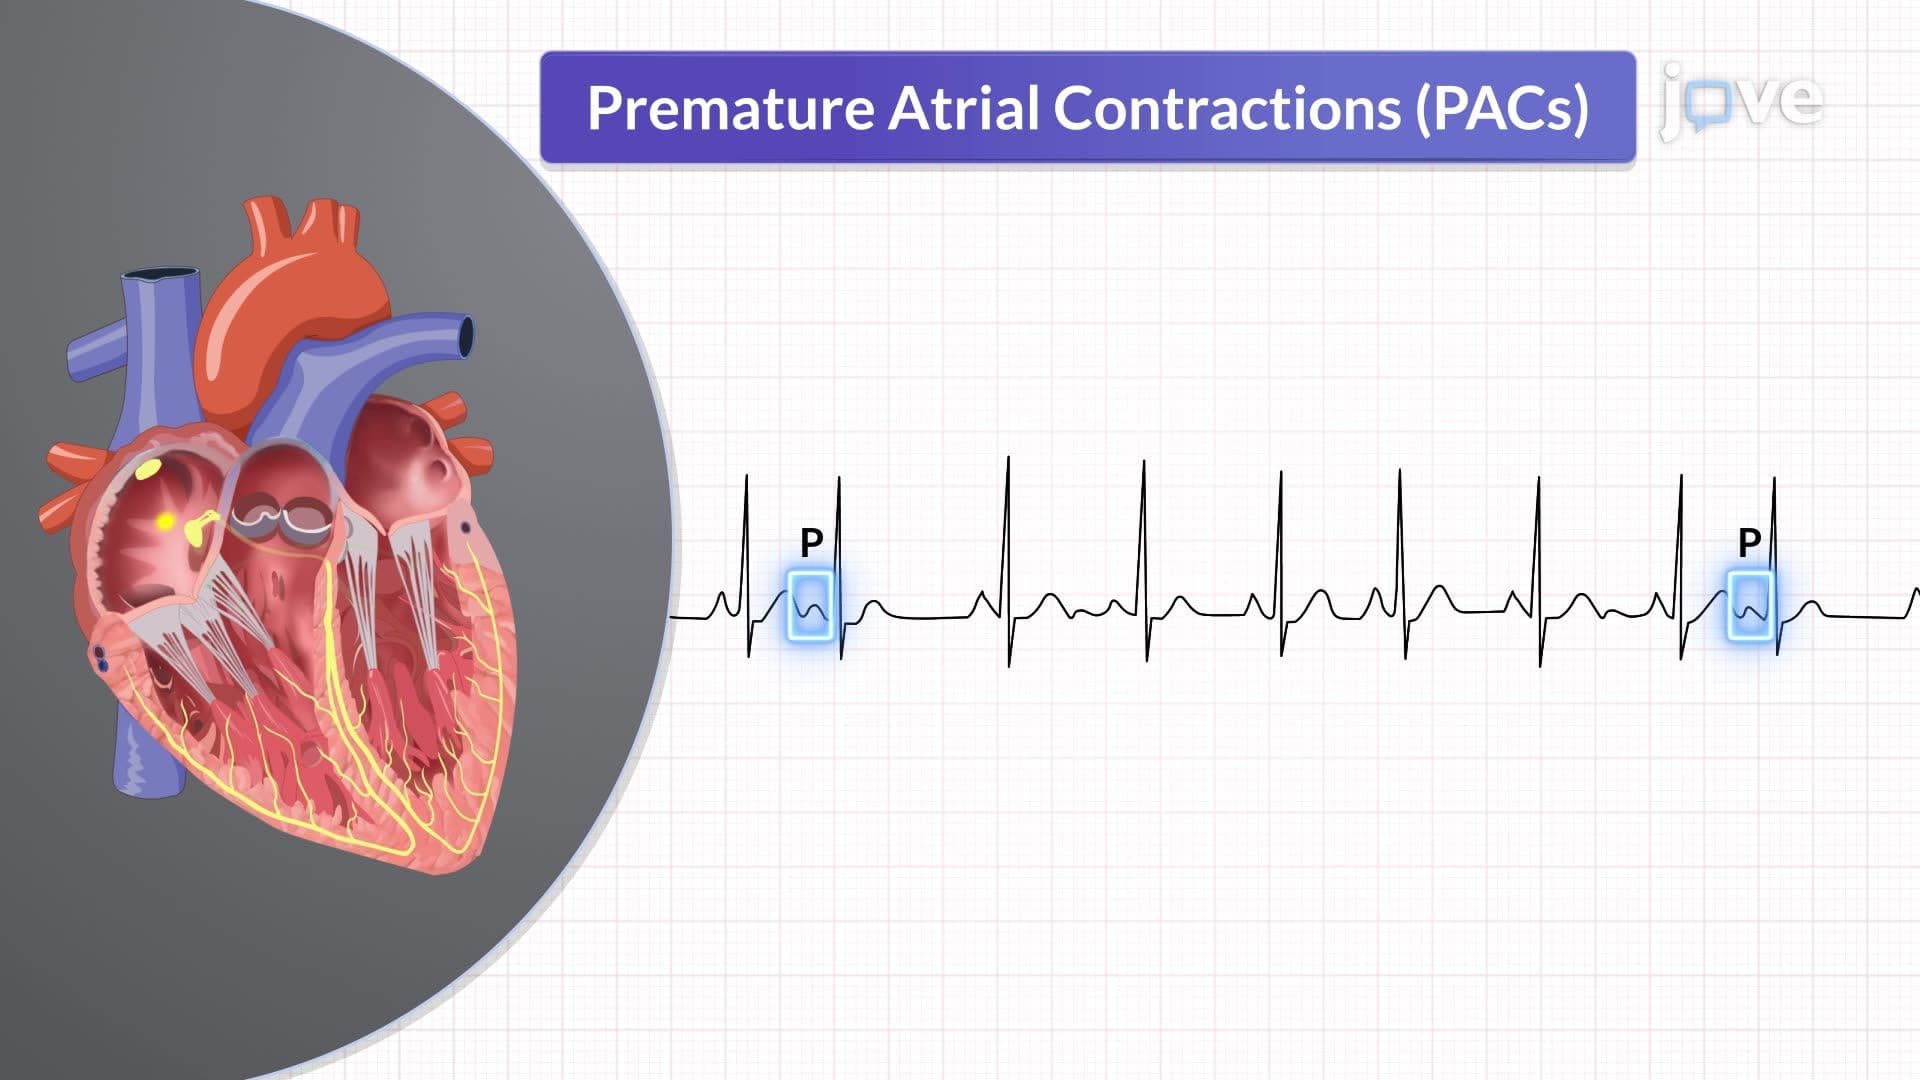
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:29
Dysrhythmias III: Characteristics of Dysrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias