Related Experiment Video
Updated: Nov 23, 2025
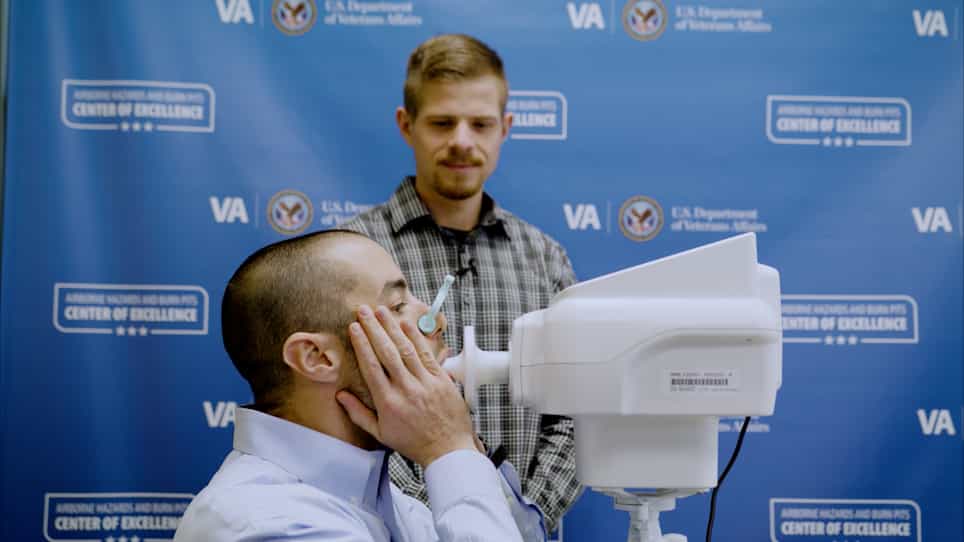

Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Prevalence of long-term mechanical insufflation-exsufflation in children with neurological conditions: a
Brit Hov1,2, Tiina Andersen3,4, Michel Toussaint5
1Division of Paediatric and Adolescent Medicine, Oslo University Hospital, Oslo, Norway.

Insights
Mechanical insufflation-exsufflation (MI-E) is used by 6 in 1000 children with neurological conditions, primarily for airway clearance. Use and timing vary by diagnosis, often alongside ventilatory support, especially in spinal muscular atrophy.
Area of Science:
- Pediatric Pulmonology
- Neurology
- Respiratory Care
Background:
- Neurological conditions in children can impair airway clearance and respiratory function.
- Mechanical insufflation-exsufflation (MI-E) is a non-invasive technique to assist ventilation and secretion clearance.
- Understanding the use and rationale for long-term MI-E in pediatric populations is crucial for clinical practice.
Purpose of the Study:
- To determine the prevalence of long-term mechanical insufflation-exsufflation (MI-E) in children with neurological conditions.
- To identify the reasons for initiating MI-E treatment in this population.
- To examine the use of concomitant mechanical ventilation alongside MI-E.
Main Methods:
- Population-based, cross-sectional study utilizing Norwegian national registries.
- Data collection through a questionnaire administered to eligible children using MI-E devices.
- Analysis of prevalence, age at initiation, reasons for use, and co-occurring ventilatory support.
Main Results:
- The prevalence of MI-E in children with neurological conditions was 6 per 1000.
- Airway clearance was the primary reason (76%) for initiating long-term MI-E.
- MI-E use and initiation age varied by diagnosis; 56% of MI-E users also received ventilatory support.
Conclusions:
- MI-E is utilized in a significant minority of children with neurological conditions, with airway clearance being the main driver.
- Prevalence and patterns of MI-E use, including co-administration with ventilation, differ across specific neurological diagnoses.
- Clinical judgment guides the initiation of MI-E in pediatric patients with neurological disorders.
Aim:
To determine the prevalence of long-term mechanical insufflation-exsufflation (MI-E) and concomitant mechanical ventilation in children with neurological conditions, with reported reasons behind the initiation of treatment.
Method:
This was a population-based, cross-sectional study using Norwegian national registries and a questionnaire.
Results:
In total, 114 of 19 264 children with a neurological condition had an MI-E device. Seventy-three of 103 eligible children (31 females, 42 males), median (min-max) age of 10 years 1 month (1y 5mo-17y 10mo), reported their MI-E treatment initiation. Overall, 76% reported airway clearance as the main reason to start long-term MI-E. A prophylactic use was mainly reported by children with neuromuscular disorders (NMDs). Prevalence and age at initiation differed by diagnosis. In spinal muscular atrophy and muscular dystrophies, MI-E use was reported in 34% and 7% of children, of whom 83% and 57% respectively received ventilator support. One-third of the MI-E users were children with central nervous system (CNS) conditions, such as cerebral palsy and degenerative disorders, and ventilator support was provided in 31%. The overall use of concomitant ventilatory support among the long-term MI-E users was 56%.
Interpretation:
The prevalence of MI-E in a neuropaediatric population was 6 per 1000, with two-thirds having NMDs and one-third having conditions of the CNS. The decision to initiate MI-E in children with neurological conditions relies on clinical judgment.
What This Paper Adds:
The prevalence and age at initiation of mechanical insufflation/exsufflation (MI-E) differed between diagnoses. MI-E was most commonly used in spinal muscular atrophy, where it generally coincided with ventilatory support. One-third of MI-E devices were given to children with central nervous system conditions, and one-third also received ventilatory support.
More Related Videos
 14:49
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
 08:30
Intraperitoneal Glucose Tolerance Test, Measurement of Lung Function, and Fixation of the Lung to Study the Impact of Obesity and Impaired Metabolism on Pulmonary Outcomes
Published on: March 15, 2018
Related Concept Videos
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...