Related Experiment Video
Updated: Nov 22, 2025


Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Ileocolic intussusception caused by mass-forming fibro-granulation from healed ulcer masquerading as small bowel
Takeshi Okamoto1, Katsuyuki Fukuda2
1Department of Gastroenterology, St. Luke's International Hospital, 9-1 Akashicho, Chuo-ku, Tokyo, 104-8560, Japan. okamotot@luke.ac.jp.

Abstract:
Small bowel intussusception in adults is rare. Unlike children, adults with intussusception generally have a causative lead point, of which a majority is benign. We report the case of a 55-year-old woman with systemic lupus erythematosus on steroids and nonsteroidal anti-inflammatory drugs who presented with intermittent melena. Contrast computed tomography revealed intussusception of the terminal ileum, with a low density mass which had advanced into the cecum as the lead point. The patient was diagnosed with ileocolic intussusception. The mass was observed in the terminal ileum on colonoscopy, indicating spontaneous reduction. As endoscopic treatment did not appear feasible, laparoscopic small bowel resection was performed with no complications. The resected specimen revealed a pedunculated mass over a healed ulcer. Pathology showed a deep ulcer reaching the subserosa with fibro-granulation, with no evidence of mesenteric vasculitis, thrombus, bacteria, fungi, granulomas, lipoma, or other tumors. The patient was diagnosed with ileocolic intussusception due to a fibro-granulation mass formed on a healed ulcer. Based on the patient's systemic lupus erythematosus being well controlled, the absence of other causative factors, and the discovery of several small bowel erosions on subsequent capsule endoscopy, the ulcer was strongly suspected to be drug induced. Both steroids and nonsteroidal anti-inflammatory drugs were reduced and proton pump inhibitors were discontinued by her rheumatologist after surgery. No recurrence has been observed during 4 months of follow-up.

Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
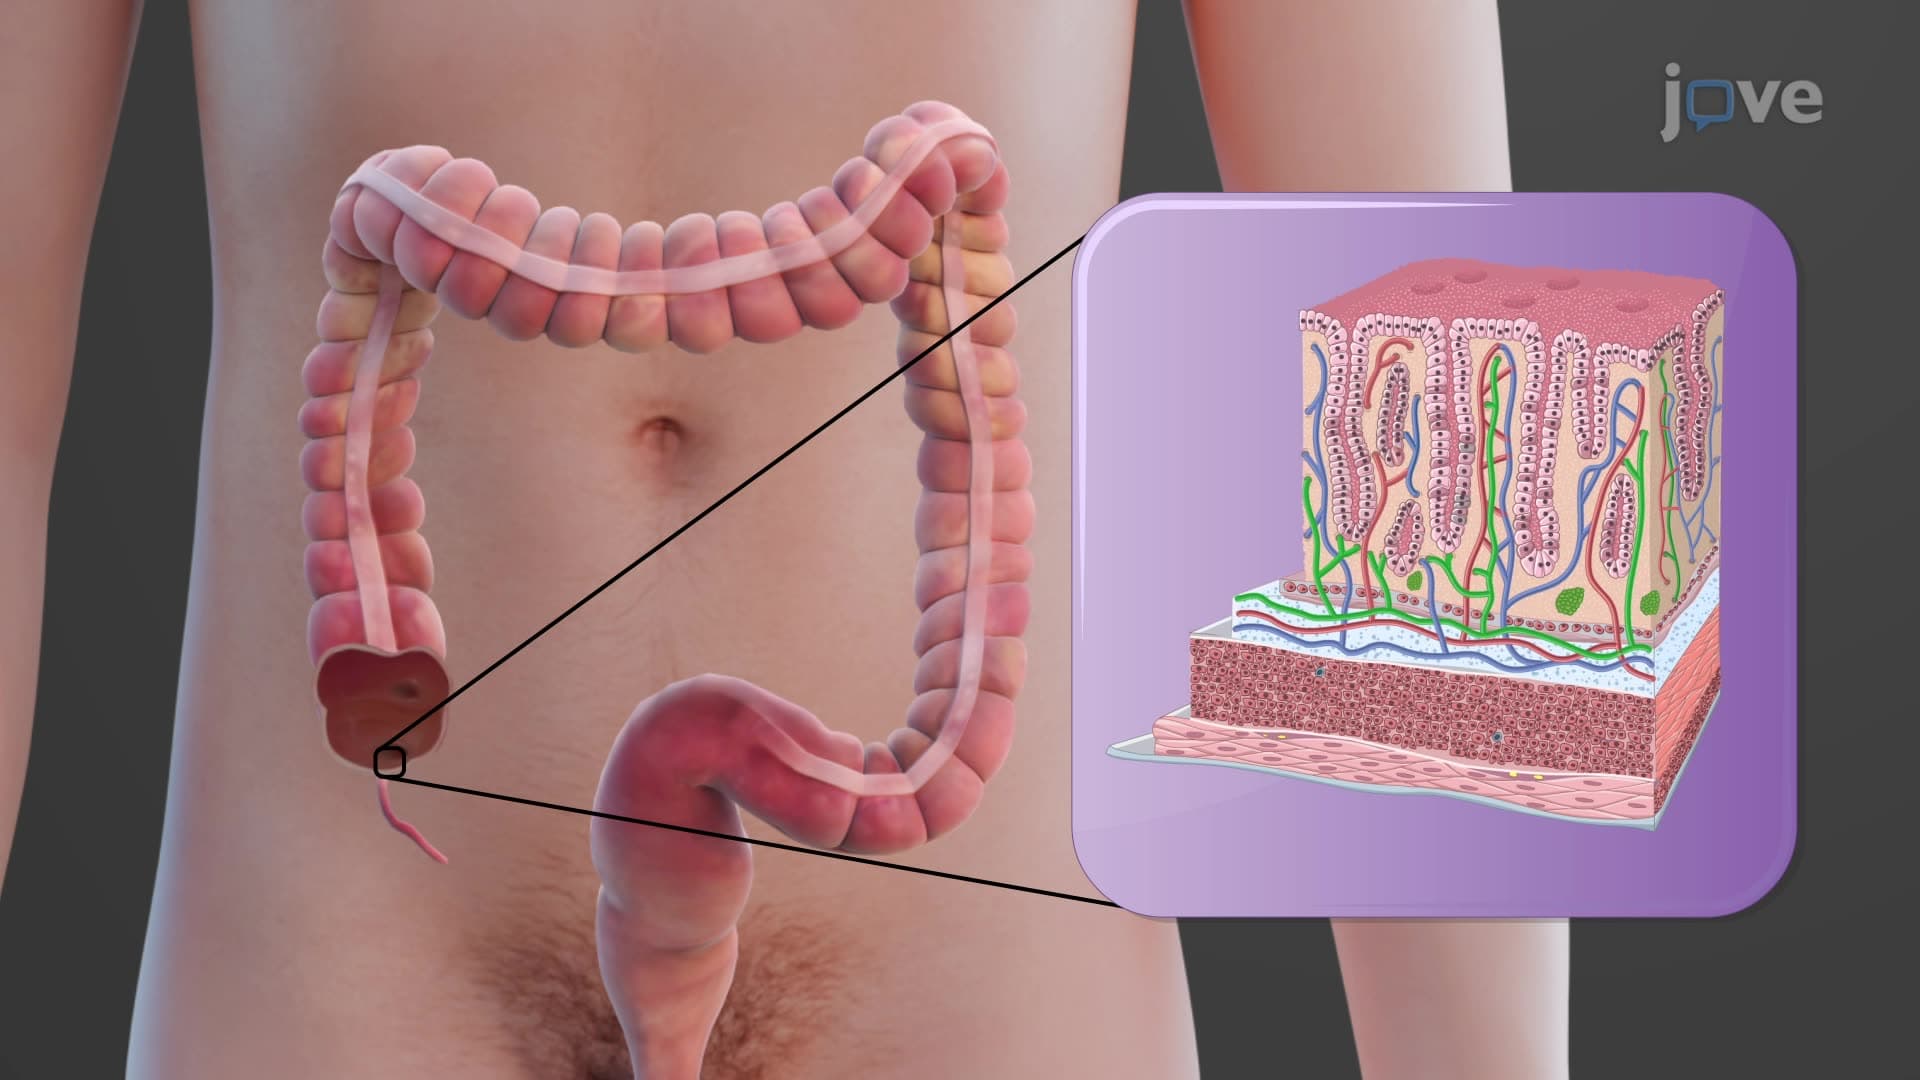
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:27
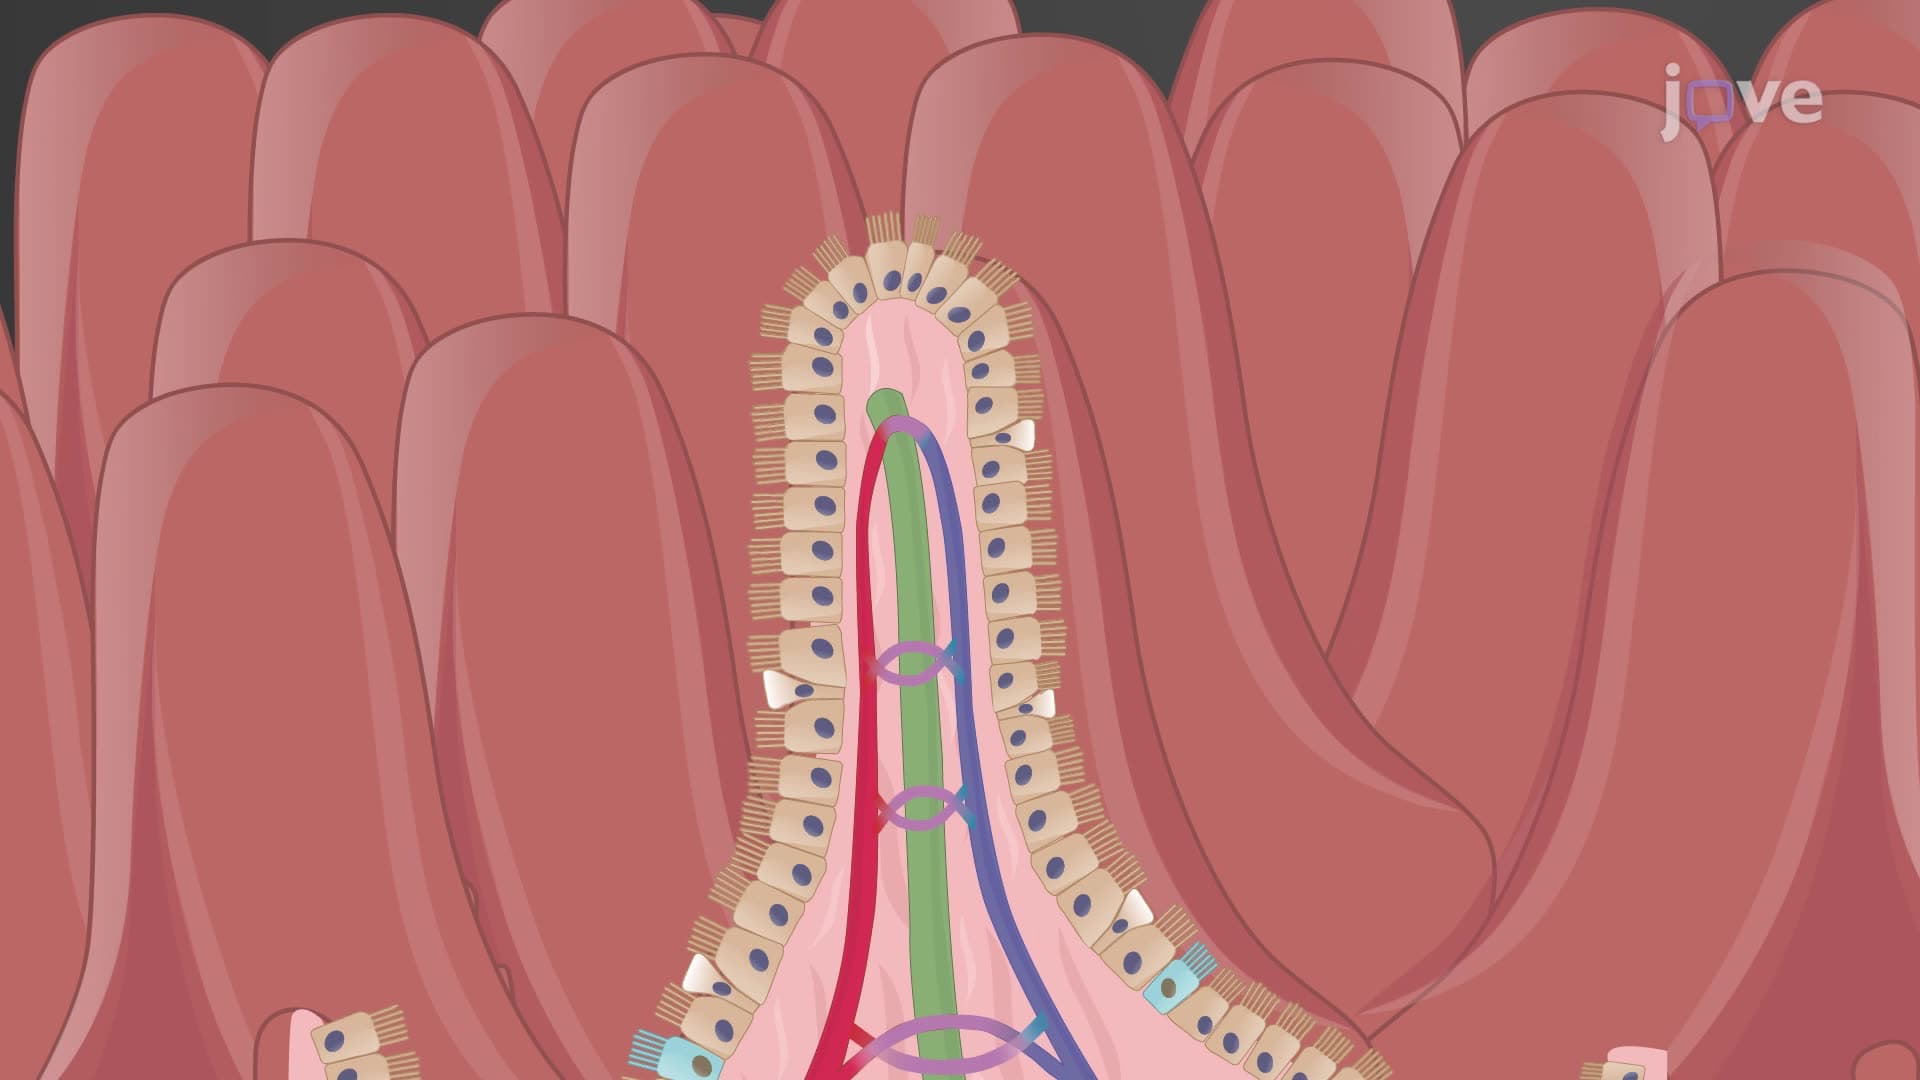
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:09
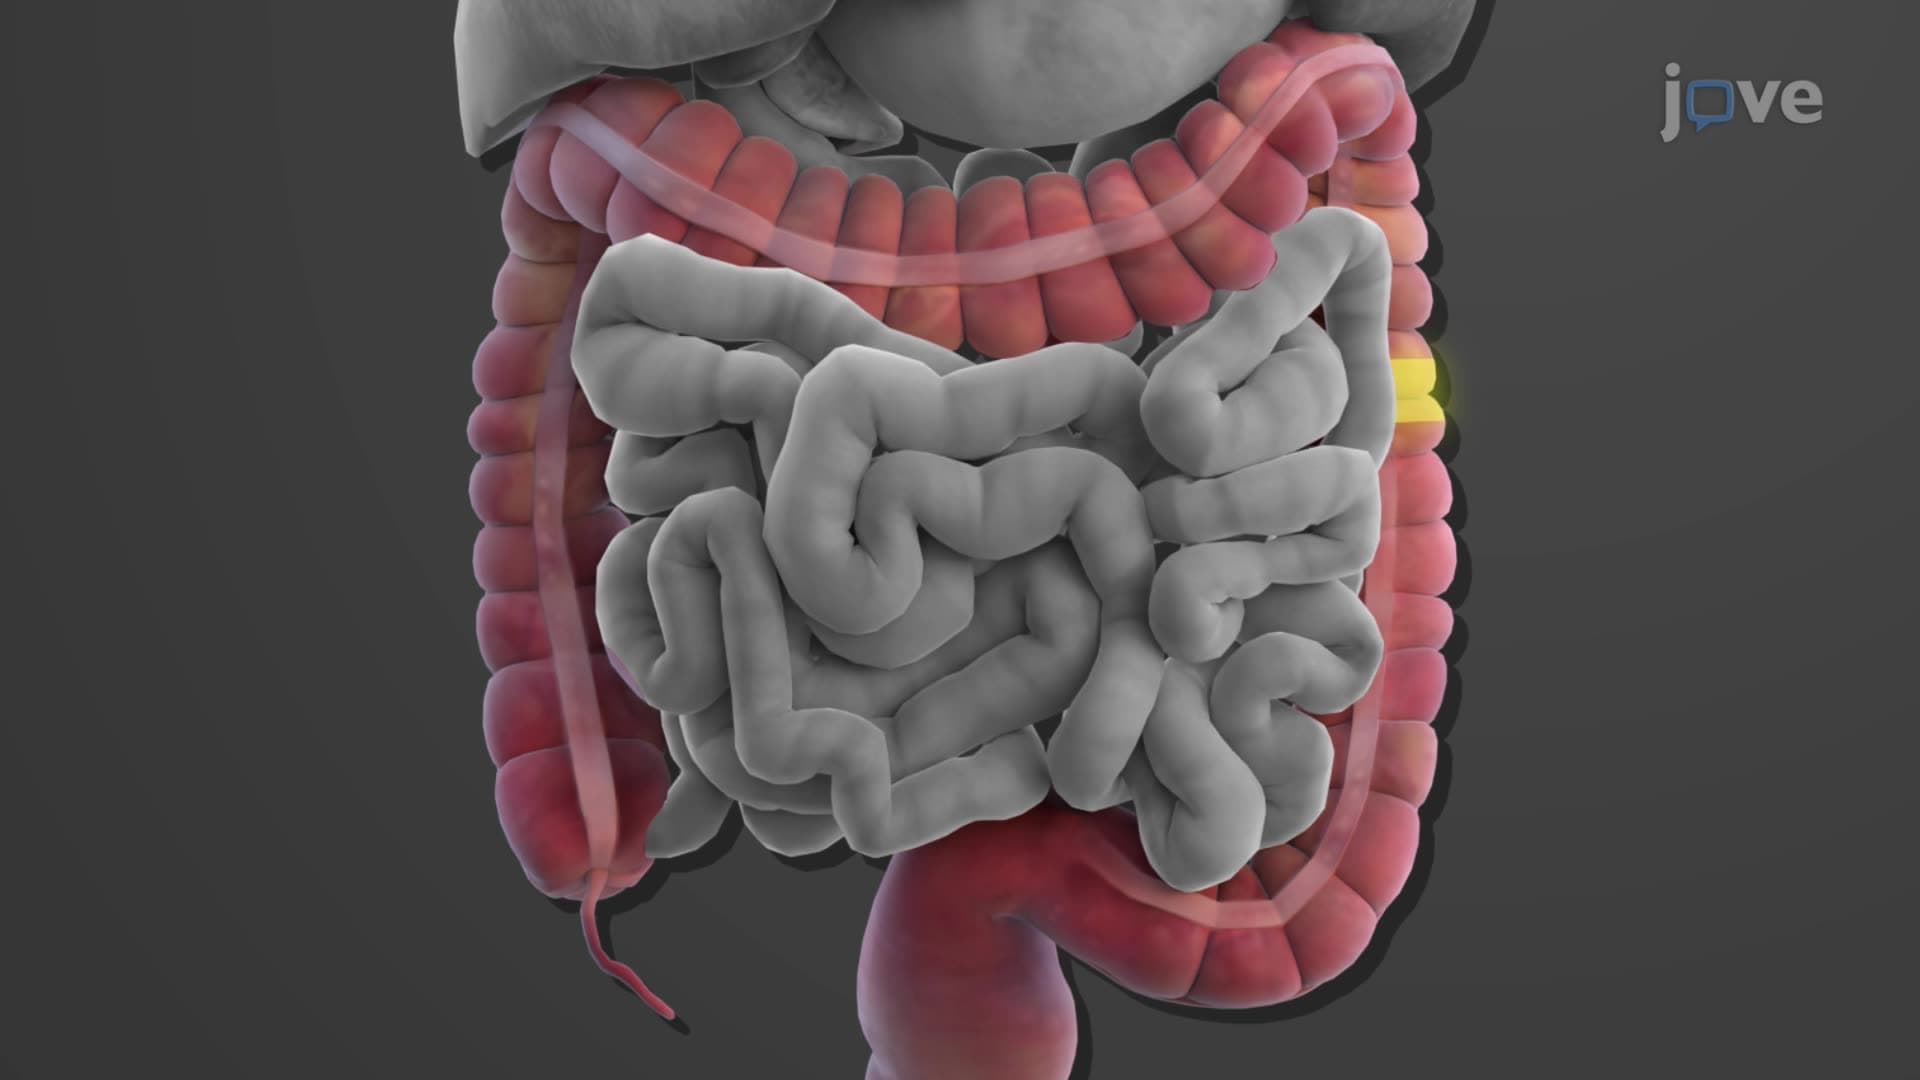
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...