Related Experiment Video
Updated: Nov 21, 2025
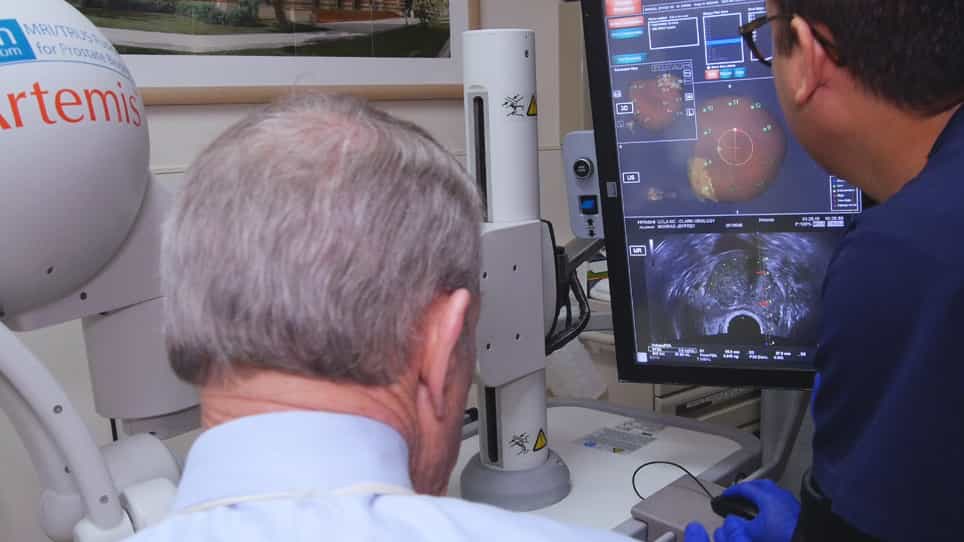

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
High-Risk Lesions Detected by MRI-Guided Core Biopsy: Upgrade Rates at Surgical Excision and Implications for
Aya Y Michaels1,2, Paula S Ginter3, Katerina Dodelzon1
1Department of Radiology, Weill Cornell Medicine, New York, NY 10065.

Abstract:
OBJECTIVE. The purpose of our study was to evaluate the upgrade rates of high-risk lesions (HRLs) diagnosed by MRI-guided core biopsy and to assess which clinical and imaging characteristics are predictive of upgrade to malignancy. MATERIALS AND METHODS. A retrospective review was performed of all women who presented to an academic breast radiology center for MRI-guided biopsy between January 1, 2015, and November 30, 2018. Histopathologic results from each biopsy were extracted. HRLs-that is, atypical ductal hyperplasia (ADH), lobular carcinoma in situ (LCIS), atypical lobular hyperplasia (ALH), radial scar, papilloma, flat epithelial atypia (FEA), benign vascular lesion (BVL), and mucocelelike lesion-were included for analysis. Clinical history, imaging characteristics, surgical outcome, and follow-up data were recorded. Radiologic-pathologic correlation was performed. RESULTS. Of 810 MRI-guided biopsies, 189 cases (23.3%) met the inclusion criteria for HRLs. Of the 189 HRLs, 30 cases were excluded for the following reasons: 15 cases were lost to follow-up, six cases were in patients who received neoadjuvant chemotherapy after biopsy, two lesions that were not excised had less than 2 years of imaging follow-up, and seven lesions had radiologic-pathologic discordance at retrospective review. Of the 159 HRLs in our study cohort, 13 (8.2%) were upgraded to carcinoma. Surgical upgrade rates were high for ADH (22.5%, 9/40) and FEA (33.3%, 1/3); moderate for LCIS (6.3%, 3/48); and low for ALH (0.0%, 0/11), radial scar (0.0%, 0/28), papilloma (0.0%, 0/26), and BVL (0.0%, 0/3). Of the upgraded lesions, 69.2% (9/13) were upgraded to ductal carcinoma in situ (DCIS) or well-differentiated carcinoma. ADH lesions were significantly more likely to be upgraded than non-ADH lesions (p = .005). CONCLUSION. ADH diagnosed by MRI-guided core biopsy warrants surgical excision. The other HRLs, however, may be candidates for imaging follow-up rather than excision, especially after meticulous radiologic-pathologic correlation.
More Related Videos
 06:08
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
 05:49
Use of Magnetic Resonance Imaging and Biopsy Data to Guide Sampling Procedures for Prostate Cancer Biobanking
Published on: October 10, 2019
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Urinary Tract Calculi VI: Surgical Management