Related Experiment Video
Updated: Nov 21, 2025
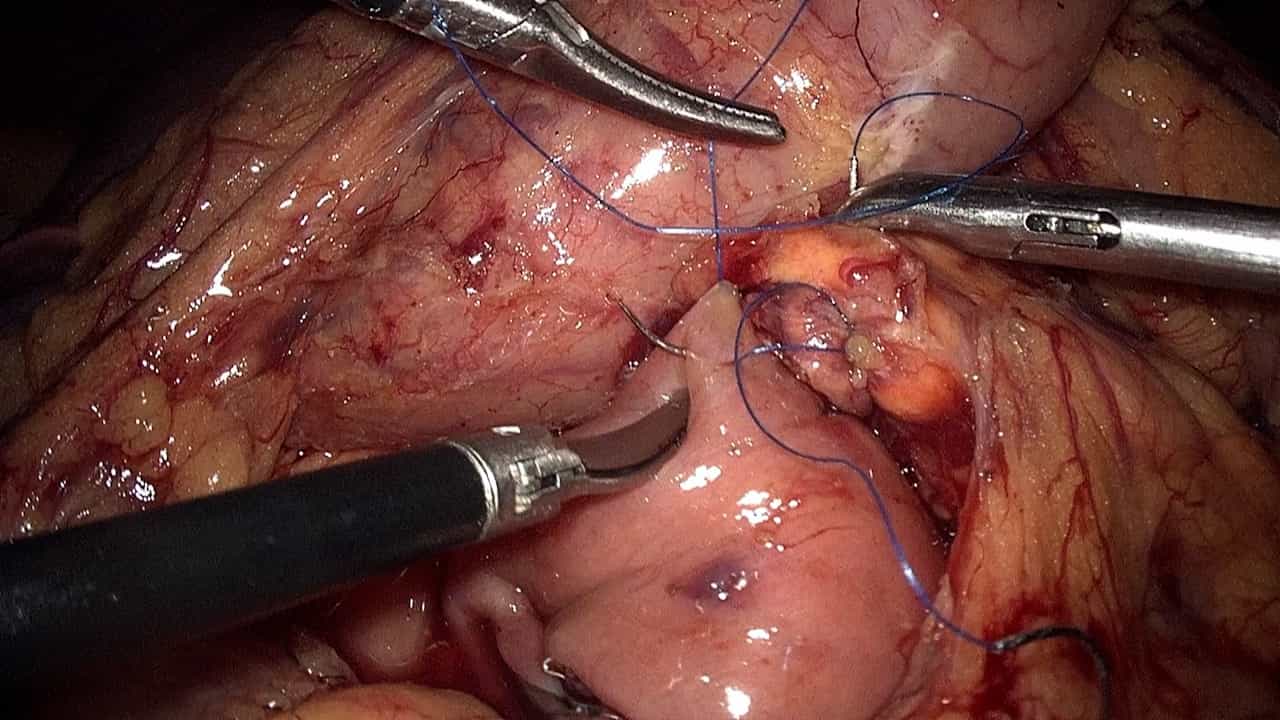

Laparoscopic Duodenum-Preserving Pancreatic Head Resection via Inferior Infracolic Approach: A Surgical Approach for Benign Lesions
Published on: February 9, 2024
Hemosuccus Pancreaticus: A systematic approach
H S Yashavanth1, Nitin Jagtap1, Jagadeesh Rampal Singh2
1Department of Medical Gastroenterology, Asian Institute of Gastroenterology, Hyderabad, India.

Background And Aim:
Hemosuccus pancreaticus is considered as one of the rare cause of upper gastrointestinal bleeding. Intermittent nature of bleeding and lack of standardized approach for diagnosis has resulted in significant delay in definitive management.
Methods:
We retrospectively analyzed prospectively maintained data of patients with suspected hemosuccus pancreaticus between January 2010 and December 2019.
Results:
Out of 114 patients, 87 patients were diagnosed with hemosuccus pancreaticus. Mean age was 35.7 ± 11.7 years with 89.7% men. Median duration of bleeding before diagnosis was 10 days, with 40.2%, 10.3%, and 5.7% patients had symptoms beyond 1, 6, and 12 months, respectively. Visceral artery aneurysm was noted in 62% of cases with splenic artery aneurysm (37.9%) being the common source of bleed. Rarer causes noted were superior mesenteric artery aneurysm, pancreatic adenocarcinoma, gastrointestinal stromal tumor, and post-endoscopic retrograde cholangiopancreatography (2.3% each). Santorinirrhage was seen in 3.4% patients. Endoscopic diagnosis was possible in 64.4% of patients, and angiogram localization of bleeding source was noted in 94.2%. A 56.3% of patients underwent conventional angioembolization with 95.9% success and 28.7% underwent surgery, with overall rebleeding rate of 11.5%.
Conclusions:
Early diagnosis of hemosuccus pancreaticus avoids prolonged suffering, multiple hospital admissions, and multiple blood transfusions. It is not uncommon in the absence of aneurysm. In cases of high suspicion, repeating the endoscopy with proper technique and proper timing increases the yield. Angioembolization remains the most preferred first line therapeutic approach in majority of cases.