Related Experiment Video
Updated: Nov 20, 2025


Chronic Intermittent Ethanol Vapor Exposure Paired with Two-Bottle Choice to Model Alcohol Use Disorder
Published on: June 23, 2023
Distinguishing between toxic alcohol ingestion vs alcoholic ketoacidosis: how can we tell the difference?
Emily T Cohen1, Mark K Su1,2, Rana Biary1
1Division of Medical Toxicology, Ronald O. Perelman Department of Emergency Medicine, NYU Grossman School of Medicine, New York, NY, USA.

Context:
Anion gap metabolic acidosis (AGMA) is common in patients presenting for emergency care. While some disease processes and ingestions are easily excluded, diagnosing toxic alcohol (TA) ingestion can be challenging. This is especially true if drug concentrations are not readily available, which forces clinicians to rely on surrogate markers. Like TA ingestion, alcoholic ketoacidosis (AKA) produces an elevated osmol gap and an AGMA. The aim of this study was to identify risk factors suggestive of AKA when TA ingestion was the primary alternative differential diagnosis. We hypothesized that the odds of an AKA diagnosis would increase as ethanol concentration increased.
Methods:
This was a retrospective analysis of data from 2000 through 2019 from a single US Poison Control Center. Records were reviewed to identify cases coded as "methanol" or "ethylene glycol"; or coded as "alcohol" or "ethanol with acidosis." The case definition for AKA required: (1) documented alcohol use disorder; (2) urine or serum ketones or elevated blood beta-hydroxybutyrate concentration; (3) anion gap ≥ 14 mmol/L. The inclusion criterion for TAs was a detectable methanol or ethylene glycol concentration.
Results:
Of 699 patients screened, 86 were diagnosed with AKA and 36 were diagnosed with TA ingestion. As ethanol concentration increased, the odds of an AKA diagnosis significantly increased (OR = 1.016, 95% CI 1.002-1.031, p = .03).
Conclusions:
In this retrospective analysis, the odds of diagnosing AKA instead of TA ingestion increased as ethanol concentration increased. The limited ability of common clinical factors to differentiate these diagnoses highlights the need to obtain quantitative TA concentrations in real time. Until prospective validation, interpretation of ketone concentrations and toxic alcohol concentrations (when available) will continue to guide decision making.
More Related Videos
 08:37
Assessment of Glutamine as a Fuel Source for Alveolar Macrophages Exposed to Chronic Ethanol Using an Extracellular Flux Bioanalyzer
Published on: November 15, 2024
 10:11
Microdialysis of Ethanol During Operant Ethanol Self-administration and Ethanol Determination by Gas Chromatography
Published on: September 5, 2012
Related Concept Videos
 01:24
Diagnosing Acidosis and Alkalosis
First, the pH level is assessed to determine whether the blood pH is normal (7.35–7.45), low (acidosis), or high (alkalosis).
Next, the PCO2 and...
 01:14
Prevention of Further Absorption of Poison
 01:15
Oxidations of Aldehydes and Ketones to Carboxylic Acids
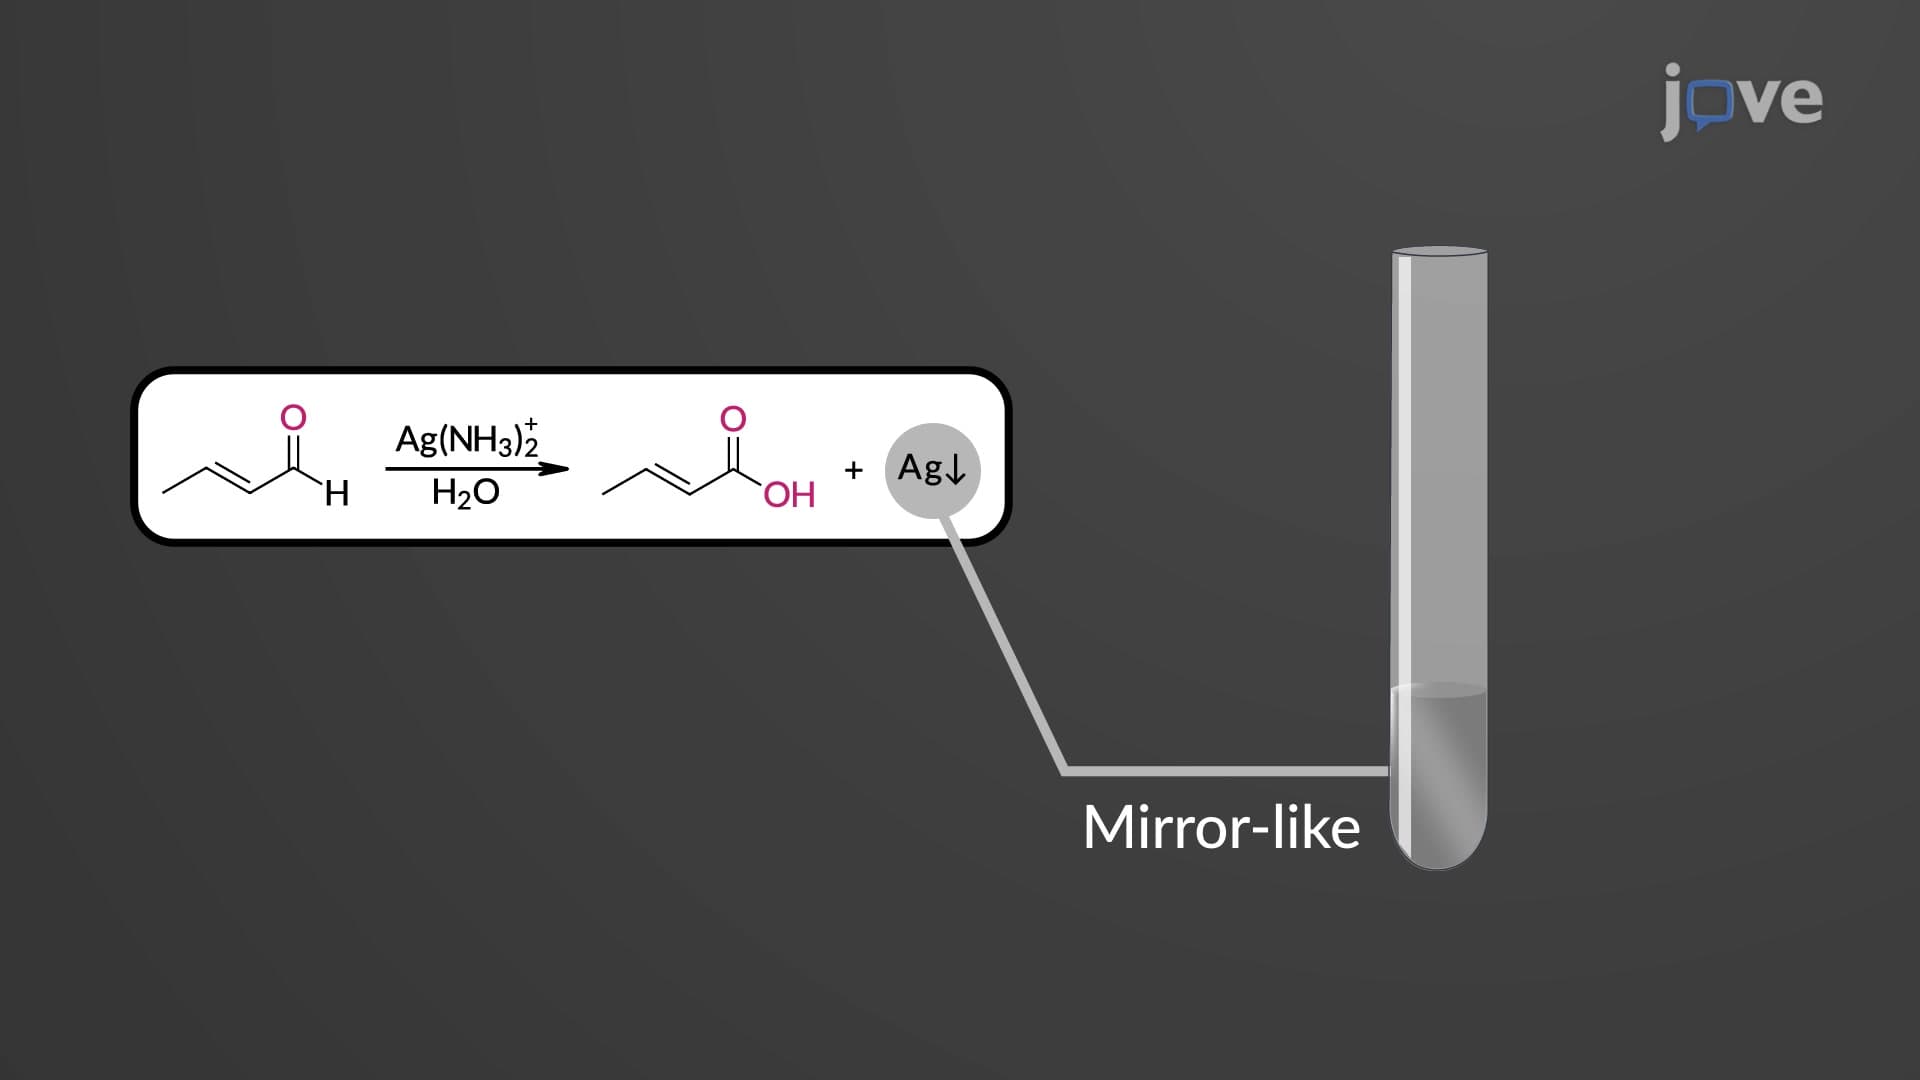
Aldehydes readily undergo oxidation in strong oxidizing agents such as potassium permanganate and chromic acid. The oxidation can also be carried out using mild oxidizing agents such as silver oxide. In fact, aldehydes can be easily oxidized...
 01:26
Enhanced Elimination of Poison
Antidotes serve a crucial role in counteracting the effects of poison by inhibiting enzymes responsible for producing harmful drug metabolites. In some cases, these toxic metabolites can be neutralized by endogenous cosubstrates, which are maintained at specific concentrations to prevent interaction with cellular macromolecules and subsequent cell death.
Renal excretion is the...
 01:27
CNS Depressants: Alcohol and Nicotine
 01:19
Aldehydes and Ketones with Alcohols: Hemiacetal Formation