Related Experiment Video
Updated: Nov 19, 2025
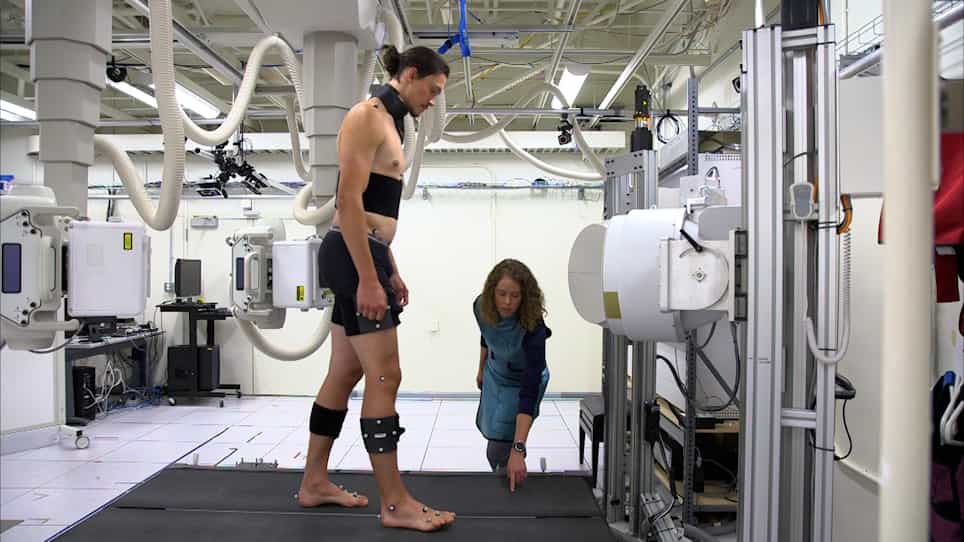
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Supraacetabular osseous corridor: defining dimensions, sex differences, and alternatives
Miqi Wang1, Robert C Jacobs2, Craig S Bartlett3
1Department of Orthopaedics and Rehabilitation, University of Vermont, 4th Floor Safford Hall, 95 Carrigan Dr., Burlington, VT, 05405, USA. mimi.wang@gmail.com.

Introduction:
The supraacetabular (SA) corridor extends from the anterior inferior iliac spine to the posterior ilium and can safely accommodate implants to stabilize pelvic and acetabular fractures. However, quantitative analysis of its dimensions and characteristics have not been thoroughly described. This study seeks to define the dimensions, common constriction points, and any alternative trajectories that would maximize the corridor diameter.
Methods:
Computed tomography of 100 male and 100 female hemipelves without osseous trauma were evaluated. The corridor boundaries were determined through manual best-fit analysis. The largest intercortical cylinder within the pathway was created and measured. Alternative trajectories were tested within the SA boundaries to identify another orientation that maximized the diameter of the intercortical cylinder.
Results:
The traditional SA corridor had a mean diameter of 8.3 mm in men and 6.2 mm in women. This difference in diameter is due to a more S-shaped ilium in women. A larger alternative SA corridor was found that had a less limited path through the ilium and measured 11.3 mm in men and 9.9 mm in women. These dimensions are significantly different compared to those of the traditional SA corridor in both men and women.
Conclusions:
In men, the SA corridor allows for the safe passage of most hardware used in pelvic and acetabular fractures. However, in women, the SA corridor is restricted by a more S-shaped ilium. An alternative trajectory was found that has a significantly larger mean diameter in both sexes. Ultimately, the trajectory of hardware will be dictated by the clinical scenario. When large implants are needed, especially in women, we recommend considering the alternative SA corridor.
More Related Videos
 08:15
Three-Dimensional Preoperative Virtual Planning in Derotational Proximal Femoral Osteotomy
Published on: February 17, 2023
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:25
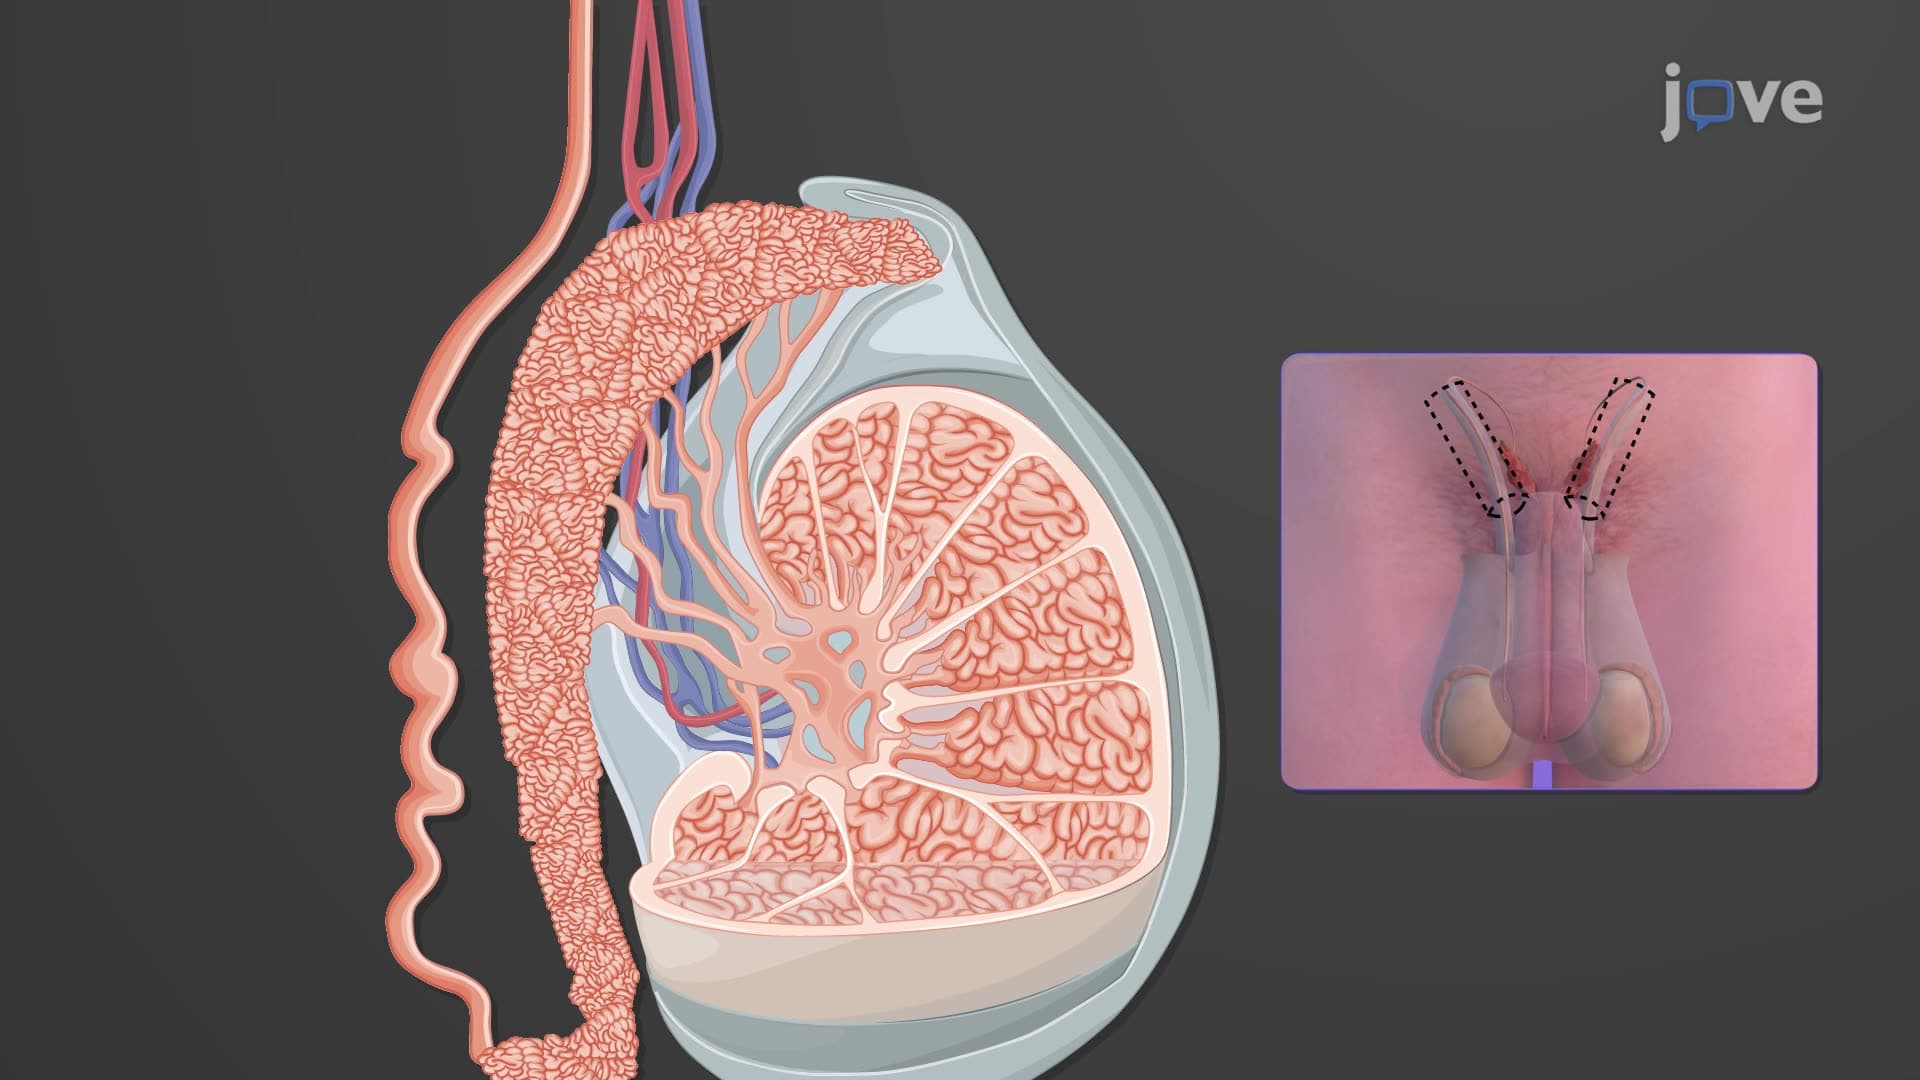
Accessory Ducts of the Male Reproductive System
The epididymis is a small, comma-shaped organ located at the back of each testicle....
 01:09
Overview of the Axial Skeleton
The axial skeleton of the...
 01:09
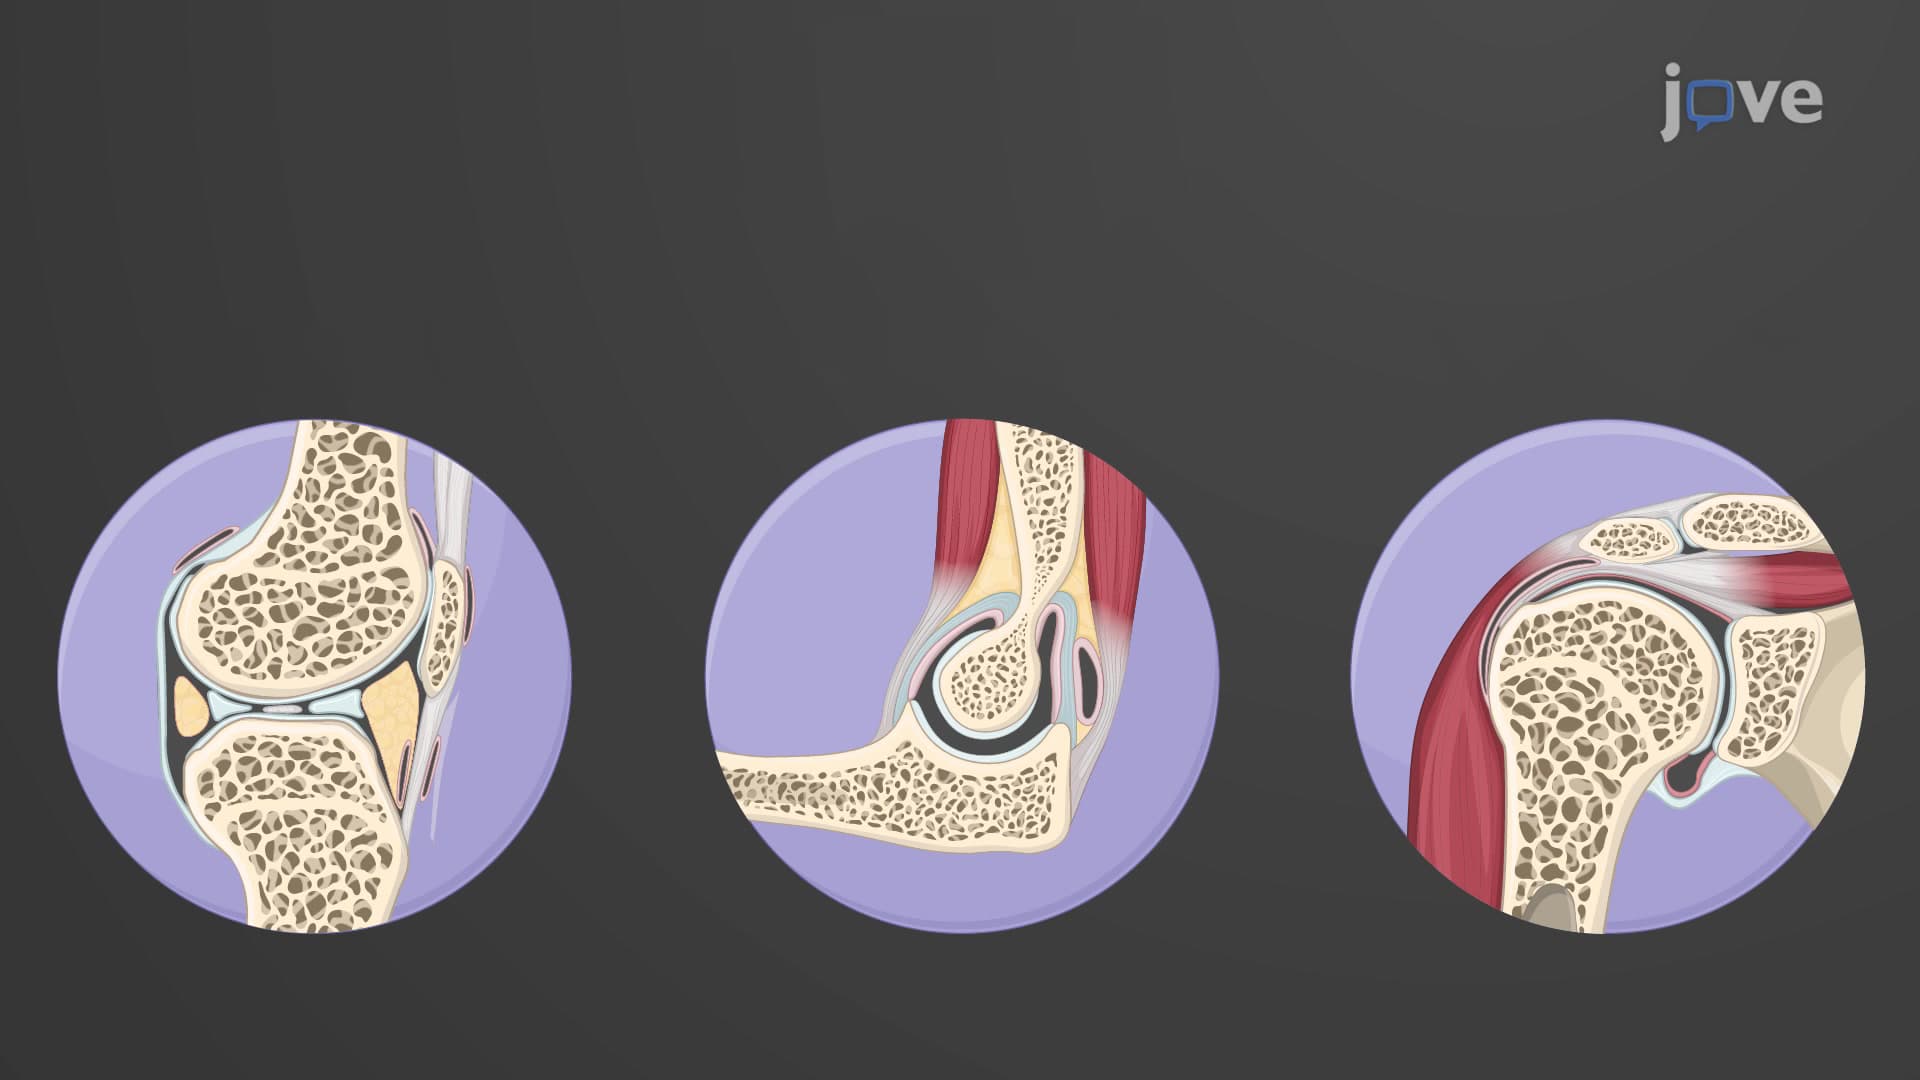
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...
 01:20
Introduction to the Skeletal System
Components of the Skeletal System
Bone, or osseous tissue, is a hard connective tissue that forms an internal support structure for the human body. Bones shield vulnerable organs and soft tissue from external forces. For example, the vertebral bones protect and support the spinal cord.
Cartilage, a semi-rigid connective tissue found in regions such as...