Related Experiment Video
Updated: Nov 18, 2025
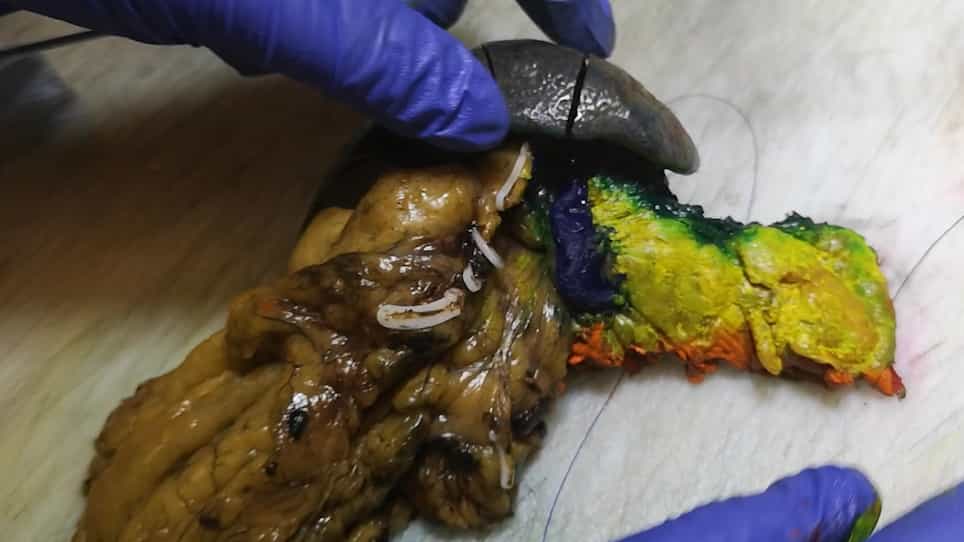

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Axial slicing versus bivalving in the pathological examination of pancreatoduodenectomy specimens (APOLLO): a
Stijn van Roessel1, Eline C Soer2, Susan van Dieren1
1Department of Surgery, Cancer Center Amsterdam, Amsterdam UMC, University of Amsterdam, the Netherlands.

Background:
In pancreatoduodenectomy specimens, dissection method may affect the assessment of primary tumour origin (i.e. pancreatic, distal bile duct or ampullary adenocarcinoma), which is primarily determined macroscopically. This is the first study to prospectively compare the two commonly used techniques, i.e. axial slicing and bivalving.
Methods:
In four centres, a randomized controlled trial was performed in specimens of patients with a suspected (pre)malignant tumour in the pancreatic head. Primary outcome measure was the level of certainty (scale 0-100) regarding tumour origin by four independent gastrointestinal pathologists based on macroscopic assessment. Secondary outcomes were inter-observer agreement and R1 rate.
Results:
In total, 128 pancreatoduodenectomy specimens were randomized. The level of certainty in determining the primary tumour origin did not differ between axial slicing and bivalving (mean score 72 [sd 13] vs. 68 [sd 16], p = 0.21), nor did inter-observer agreement, both being moderate (kappa 0.45 vs. 0.47). In pancreatic cancer specimens, R1 rate (60% vs. 55%, p = 0.71) and the number of harvested lymph nodes (median 16 vs. 17, p = 0.58) were similar.
Conclusion:
This study demonstrated no differences in determining the tumour origin between axial slicing and bivalving. Both techniques performed similarly regarding inter-observer agreement, R1 rate, and lymph node harvest.
Insights
Dissection methods axial slicing and bivalving showed no significant difference in determining pancreatic cancer origin. Both techniques offer similar certainty, inter-observer agreement, and R1 rates in pancreatoduodenectomy specimens.
Area of Science:
- Surgical pathology
- Gastrointestinal oncology
- Surgical technique comparison
Background:
- Macroscopic assessment of pancreatoduodenectomy specimens is crucial for determining primary tumor origin (pancreatic, distal bile duct, or ampullary adenocarcinoma).
- Dissection methods can influence the accuracy of this macroscopic assessment.
- Axial slicing and bivalving are two common techniques for specimen dissection.
Purpose of the Study:
- To prospectively compare the effectiveness of axial slicing versus bivalving dissection techniques in pancreatoduodenectomy specimens.
- To evaluate the impact of each technique on the certainty of determining primary tumor origin.
- To assess secondary outcomes including inter-observer agreement and R1 resection rates.
Main Methods:
- A randomized controlled trial was conducted across four centers involving 128 pancreatoduodenectomy specimens from patients with suspected pancreatic head tumors.
- Four independent gastrointestinal pathologists assessed tumor origin macroscopically using a 0-100 certainty scale.
- Inter-observer agreement and R1 resection rates were secondary outcome measures.
Main Results:
- The level of certainty in determining tumor origin did not significantly differ between axial slicing (mean score 72) and bivalving (mean score 68) (p=0.21).
- Inter-observer agreement was moderate for both techniques (kappa 0.45 vs. 0.47).
- R1 resection rates (60% vs. 55%) and lymph node harvest (median 16 vs. 17) were similar between the groups.
Conclusions:
- Axial slicing and bivalving dissection techniques demonstrate comparable performance in determining the primary tumor origin in pancreatoduodenectomy specimens.
- Both methods yield similar results regarding diagnostic certainty, inter-observer agreement, R1 resection rates, and lymph node yield.
- The choice between axial slicing and bivalving does not appear to impact key pathological assessment outcomes.