Related Experiment Video
Updated: Nov 16, 2025

Author Spotlight: Advancements in Refractive Surgical Correction for Presbyopia and Exploring Postoperative Visual Acuity
Published on: September 20, 2024
Outcomes of modified vertical rectus belly transposition versus augmented superior rectus transposition for chronic
Jing Yao1, Weiyi Xia1, Xiying Wang1
1Department of Ophthalmology and Vision Science, Eye & ENT Hospital, Shanghai Medical School, Fudan University, Shanghai, China; NHC Key Laboratory of Myopia, Fudan University, Shanghai, China; Laboratory of Myopia, Chinese Academy of Medical Sciences, Shanghai, China.

Purpose:
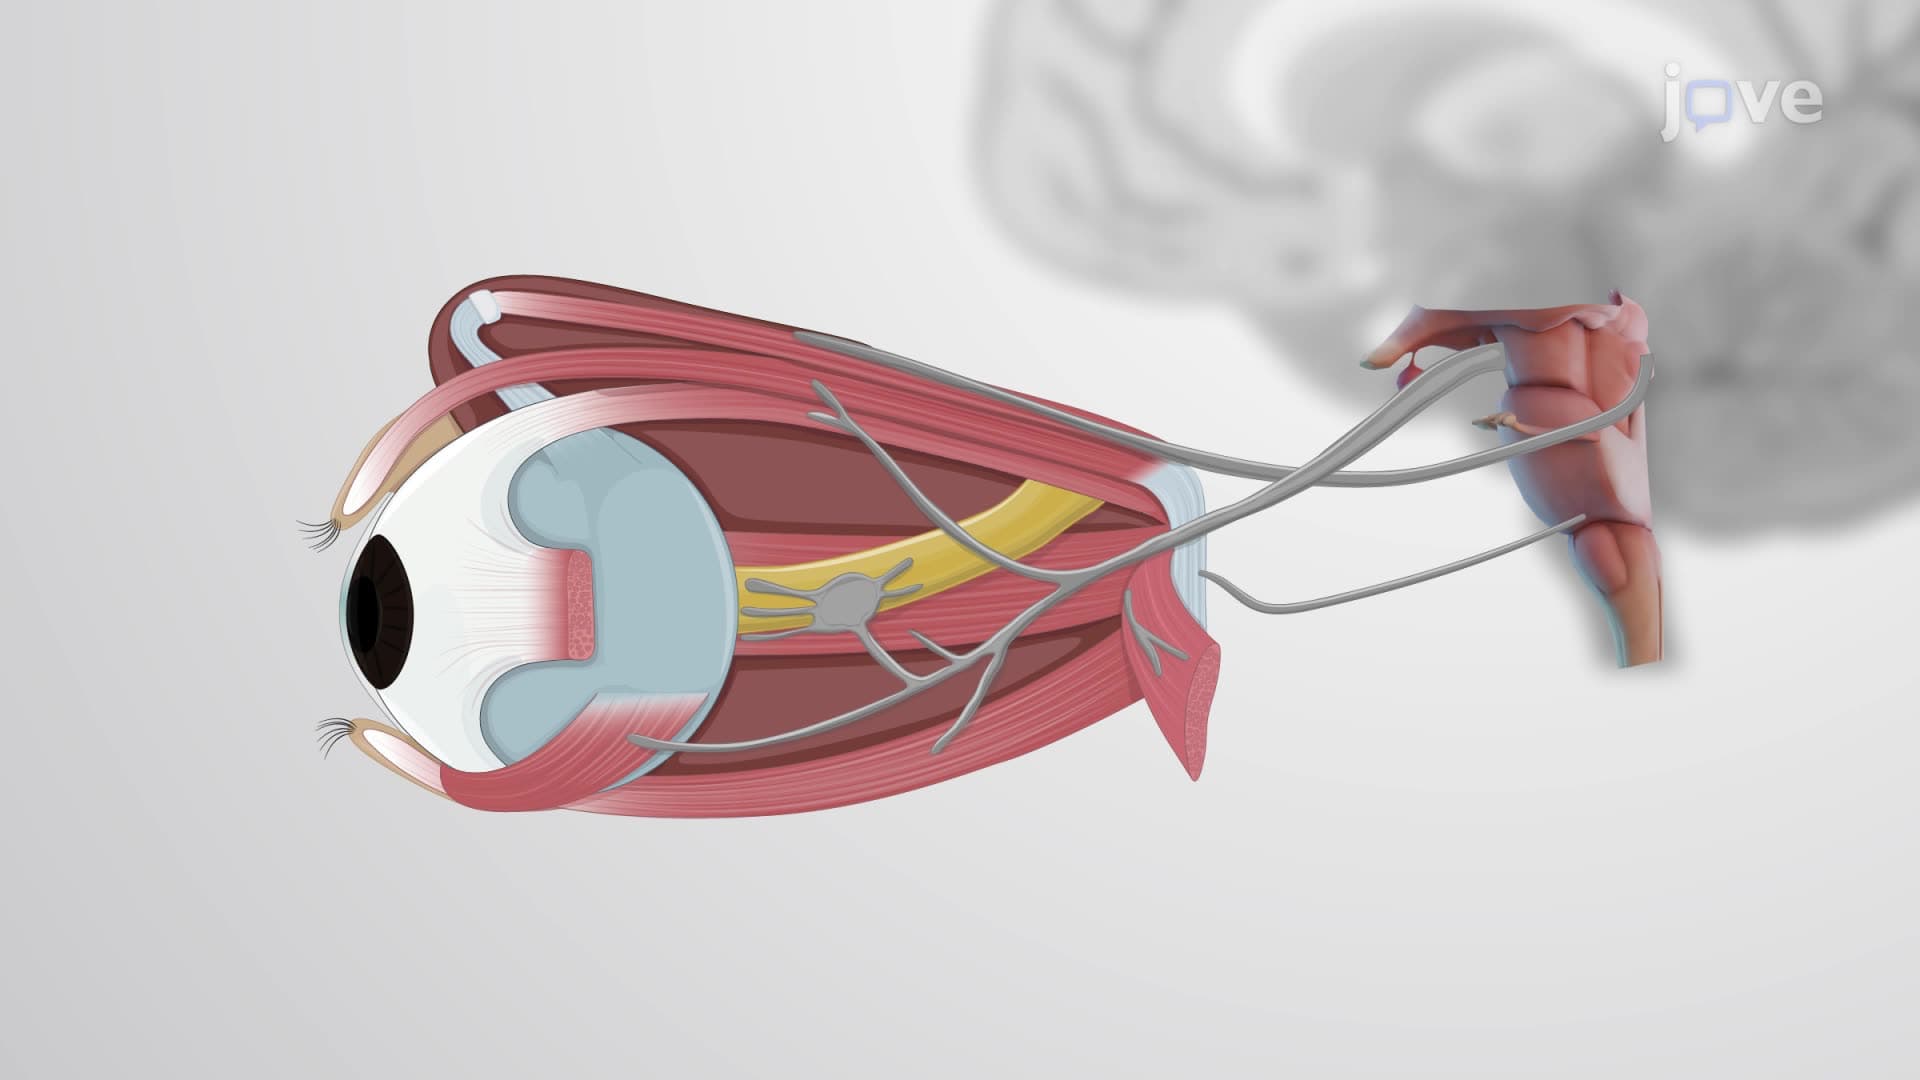
To compare the surgical outcomes of modified vertical rectus belly transposition (mVRBT) and medial rectus recession (MRc) versus augmented superior rectus transposition (aSRT) and MRc in Chinese patients with chronic abducens nerve palsy.
Methods:
The medical records of patients with chronic abducens nerve palsy who underwent mVRBT/MRc or aSRT/MRc were retrospectively reviewed. Pre- and postoperative deviation in primary position, pre- and postoperative abduction limitation, and complications were recorded. Follow-up was at least 6 months.
Results:
A total of 26 patients (mean age, 37.9 ± 19.6 years; 16 males [62%]) were included. Fourteen patients underwent mVRBT/MRc (mVRBT group) and 12 underwent aSRT/MRc (aSRT group). Both groups had similar amounts of recession (t = 0.27; P = 0.79). After surgery, statistically significant changes of abduction limitation and esotropia were observed (both P < 0.05). However, the difference in abduction improvement between groups was not statistically significant (mVRBT vs aSRT, 2.3 ± 0.91 vs 2.3 ± 0.97; t = 0.10, P = 0.92). Of the 19 patients who underwent unilateral surgery, preoperative esotropia was similar in both groups (t = 1.3; P = 0.21), but more esotropia was corrected in the mVRBT group than in the aSRT group (mVRBT vs aSRT, 57.8Δ ± 14.3Δ vs 44.6Δ ± 9.8Δ; t = 2.1; P = 0.047). There was no symptomatic vertical or torsional deviation.
Conclusions:
In our patient cohort, mVRBT/MRc showed a better effect in correcting esotropia and a similar effect in improving abduction limitation compared with aSRT/MRc.