Related Experiment Video
Updated: Nov 14, 2025
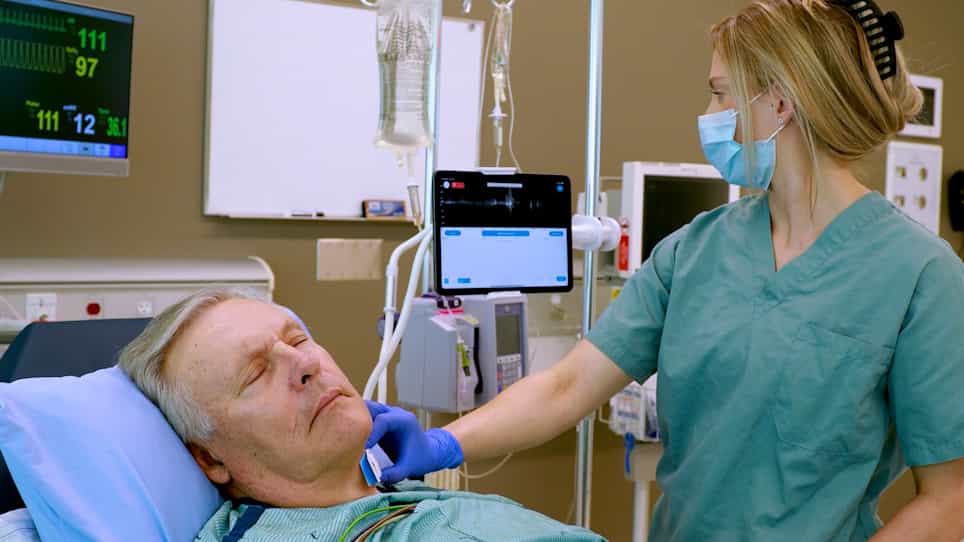

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Hemodynamic Changes via the Lung Recruitment Maneuver Can Predict Fluid Responsiveness in Stroke Volume and Arterial
Aya Kimura1, Koichi Suehiro1, Takashi Juri1
1From the Departments of Anesthesiology.

Background:
We aimed to evaluate the ability of lung recruitment maneuver-induced hemodynamic changes to predict fluid responsiveness in patients undergoing lung-protective ventilation during one-lung ventilation (OLV).
Methods:
Thirty patients undergoing thoracic surgery with OLV (tidal volume: 6 mL/kg of ideal body weight and positive end-expiratory pressure: 5 cm H2O) were enrolled. The study protocol began 30 minutes after starting OLV. Simultaneous recordings were performed for hemodynamic variables of heart rate, mean arterial pressure (MAP), stroke volume (SV), pulse pressure variation (PPV), and stroke volume variation (SVV) were recorded at 4 time points: before recruitment maneuver (continuous airway pressure: 30 cm H2O for 30 seconds), at the end of recruitment maneuver, and before and after volume loading (250 mL over 10 minutes). Patients were recognized as fluid responders if the increase in SV or MAP was >10%. Receiver operating characteristic curves for percent decrease in SV and MAP by recruitment maneuver (ΔSVRM and ΔMAPRM, respectively) were generated to evaluate the ability to discriminate fluid responders from nonresponders. The gray-zone approach was applied for ΔSVRM and ΔMAPRM.
Results:
Of 30 patients, there were 17 SV-responders (57%) and 12 blood pressure (BP)-responders (40%). Area under the curve (AUC) for ΔSVRM to discriminate SV-responders from nonresponders was 0.84 (95% confidence interval [CI], 0.67-0.95; P < .001). The best threshold for ΔSVRM to discriminate the SV-responders was -23.7% (95% CI, -41.2 to -17.8; sensitivity, 76.5% [95% CI, 50.1-93.2]; specificity, 84.6% [95% CI, 54.6-98.1]). For BP-responders, AUC for ΔMAPRM was 0.80 (95% CI, 0.61-0.92, P < .001). The best threshold for ΔMAPRM was -17.3% (95% CI, -23.9 to -5.1; sensitivity, 75.0% [95% CI, 42.8-94.5]; specificity, 77.8% [95% CI, 52.4-93.6]). With the gray-zone approach, the inconclusive range of ΔSVRM for SV-responders was -40.1% to -13.8% including 13 (43%) patients, and that of ΔMAPRM was -23.9% to -5.1%, which included 16 (53%) patients.
Conclusions:
ΔSVRM and ΔMAPRM could predict hemodynamic responses after volume expansion during OLV.
More Related Videos

Related Concept Videos
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:15
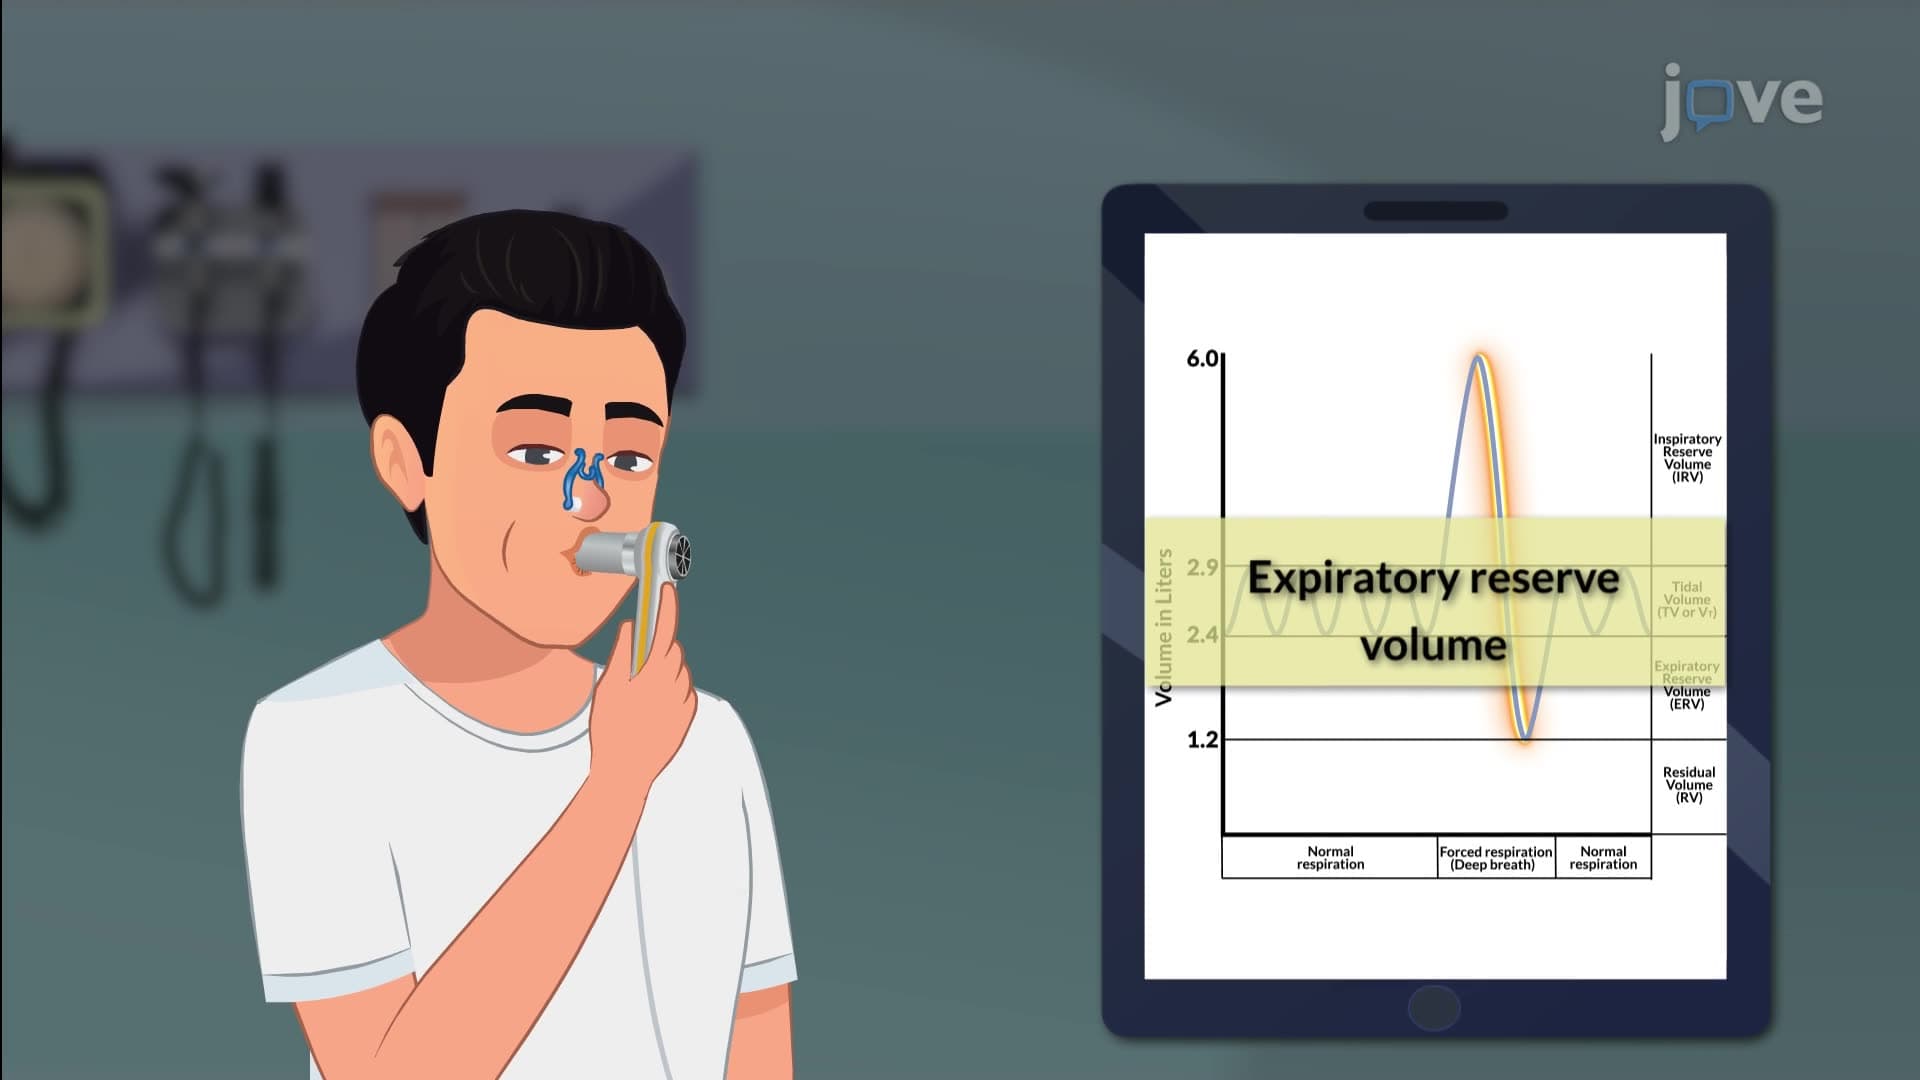
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...