Related Experiment Video
Updated: Nov 12, 2025


Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Association Between Cerebral Desaturation and Postoperative Delirium in Thoracotomy With One-Lung Ventilation: A
Fan Cui1, Wei Zhao2, Dong-Liang Mu1
1From the Department of Anesthesiology and Critical Care, Peking University First Hospital, Beijing, China.

Background:
The association between cerebral desaturation and postoperative delirium in thoracotomy with one-lung ventilation (OLV) has not been specifically studied.
Methods:
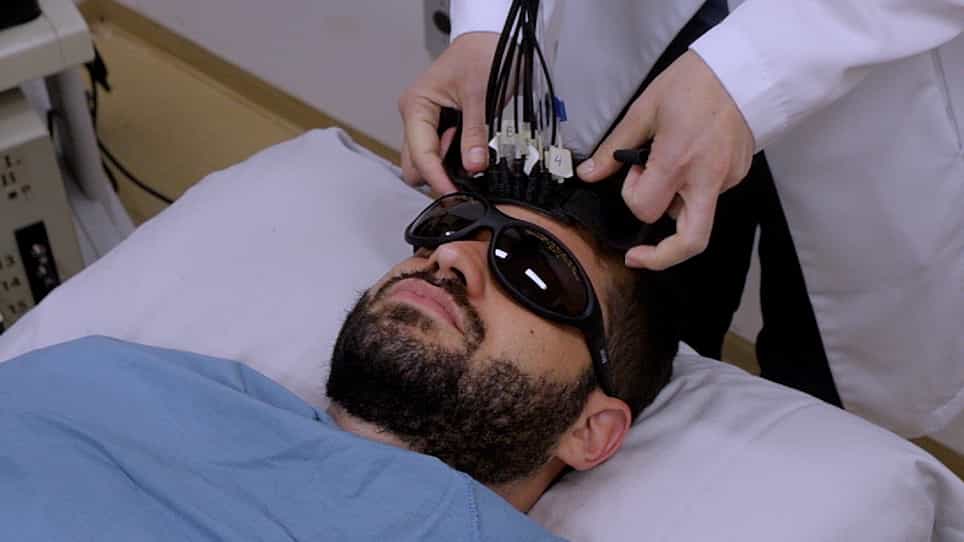
A prospective observational study performed in thoracic surgical patients. Cerebral tissue oxygen saturation (Scto2) was monitored on the left and right foreheads using a near-infrared spectroscopy oximeter. Baseline Scto2 was measured with patients awake and breathing room air. The minimum Scto2 was the lowest measurement at any time during surgery. Cerebral desaturation and hypersaturation were an episode of Scto2 below and above a given threshold for ≥15 seconds during surgery, respectively. The thresholds based on relative changes by referring to the baseline measurement were <80%, <85%, <90%, <95%, and <100% baseline for desaturation and >105%, >110%, >115%, and >120% baseline for hypersaturation. The thresholds based on absolute values were <50%, <55%, <60%, <65%, and <70% for desaturation and >75%, >80%, >85%, and >90% for hypersaturation. The given area under the threshold (AUT)/area above the threshold (AAT) was analyzed. Delirium was assessed until postoperative day 5. The primary analysis was the association between the minimum Scto2 and delirium using multivariable logistic regression controlled for confounders (age, OLV time, use of midazolam, occurrence of hypotension, and severity of pain). The secondary analysis was the association between cerebral desaturation/hypersaturation and delirium, and between the AUT/AAT and delirium using multivariable logistic regression controlled for the same confounders. Multiple testing was corrected using the Holm-Bonferroni method. We additionally monitored somatic tissue oxygen saturation on the forearm and upper thigh.
Results:
Delirium occurred in 35 (20%) of 175 patients (65 ± 6 years old). The minimum left or right Scto2 was not associated with delirium. Cerebral desaturation defined by <90% baseline for left Scto2 (odds ratio [OR], 5.82; 95% confidence interval [CI], 2.12-19.2; corrected P =.008) and <85% baseline for right Scto2 (OR, 4.27; 95% CI, 1.77-11.0; corrected P =.01) was associated with an increased risk of delirium. Cerebral desaturation defined by other thresholds, cerebral hypersaturation, the AUT/AAT, and somatic desaturation and hypersaturation were all not associated with delirium.
Conclusions:
Cerebral desaturation defined by <90% baseline for left Scto2 and <85% baseline for right Scto2, but not the minimum Scto2, may be associated with an increased risk of postthoracotomy delirium. The validity of these thresholds needs to be tested by randomized controlled trials.

Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:22
Stages of General Anesthesia