Related Experiment Video
Updated: Nov 11, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Which thoracic curves are at the greater risk for distal adding-on: comparison between typical and atypical Lenke 1A
Rui Yin1, Xiaodong Qin1, Zhong He1
1Department of Spine Surgery, The Affiliated Drum Tower Hospital of Nanjing University Medical School, Zhongshan Road 321, Nanjing, 210008, China.

Purpose:
To identify the characteristics and the incidence of adding-on (AO) in atypical Lenke 1A adolescent idiopathic scoliosis patients, and to investigate whether atypical and typical Lenke 1A curve should follow the same lowest instrumented vertebra (LIV) selection strategy.
Methods:
A total of 251 Lenke 1A patients who underwent posterior spinal fusion were analyzed. The minimum follow-up was 2 years. Curves were classified into two groups according to the apex. At last, 42 atypical Lenke 1A patients (apex at T10/11-T11/12) were identified and divided into atypical group (G1). Meanwhile, 42 age, gender, and Cobb angle-matched typical Lenke 1A patients (apex at T7/8-T10) were enrolled into the typical group (G2). The radiographic characteristics were evaluated, and the incidence of AO was compared between the 2 groups.
Results:
The incidence of atypical Lenke 1A curves was 16.7%. Patients in G1 were found to have more left thoracic curves (P = 0.029), better flexibility of thoracic (P = 0.011) and lumbar curve (P = 0.014), and more preoperative coronal imbalance (P = 0.001). At the final follow-up, G1 developed more AO (38.1% vs. 19.0%). Specificity, for patients with LIV proximal to last substantially touching vertebra (LSTV), the incidence of AO was significantly higher in G1 (82.4% vs. 42.9%, P = 0.022).
Conclusion:
Atypical Lenke 1A curve had its own radiographic characteristics. It was more likely to develop AO when LIV was proximal to LSTV, which indicated different fusion levels should be considered in these two subtypes of Lenke 1A. We recommended LSTV as LIV in atypical Lenke 1A cases, while one level proximal to LSTV might be available in typical Lenke 1A curve.
Level Of Evidence:
3.

Related Concept Videos
 01:12
General Case of Eccentric Axial Loading
Consider a member subjected to equal and opposite forces that are applied along a line that does not coincide with the member's neutral axis. In unsymmetrical...
 01:12
Relative Risk
 01:16
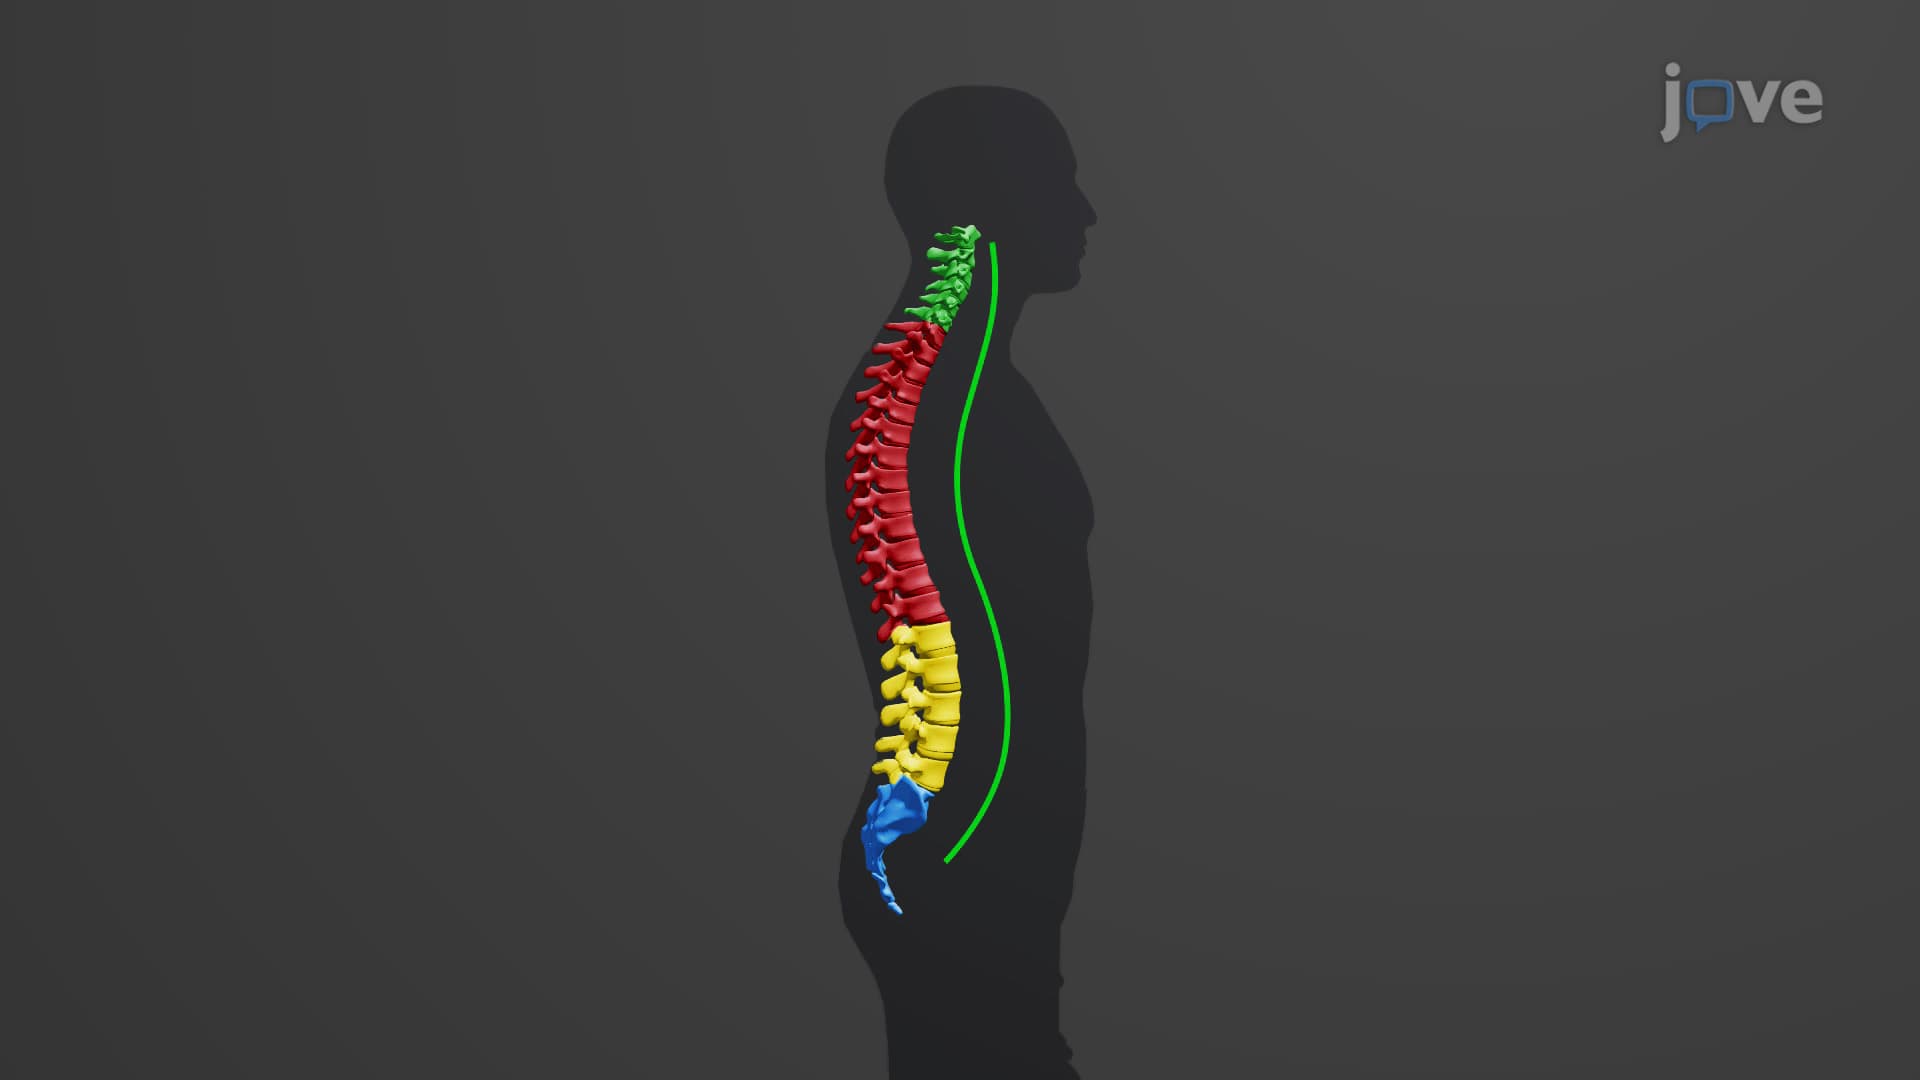
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:20
Normal Strain under Axial Loading
 01:15
Thoracic Aorta
 01:15
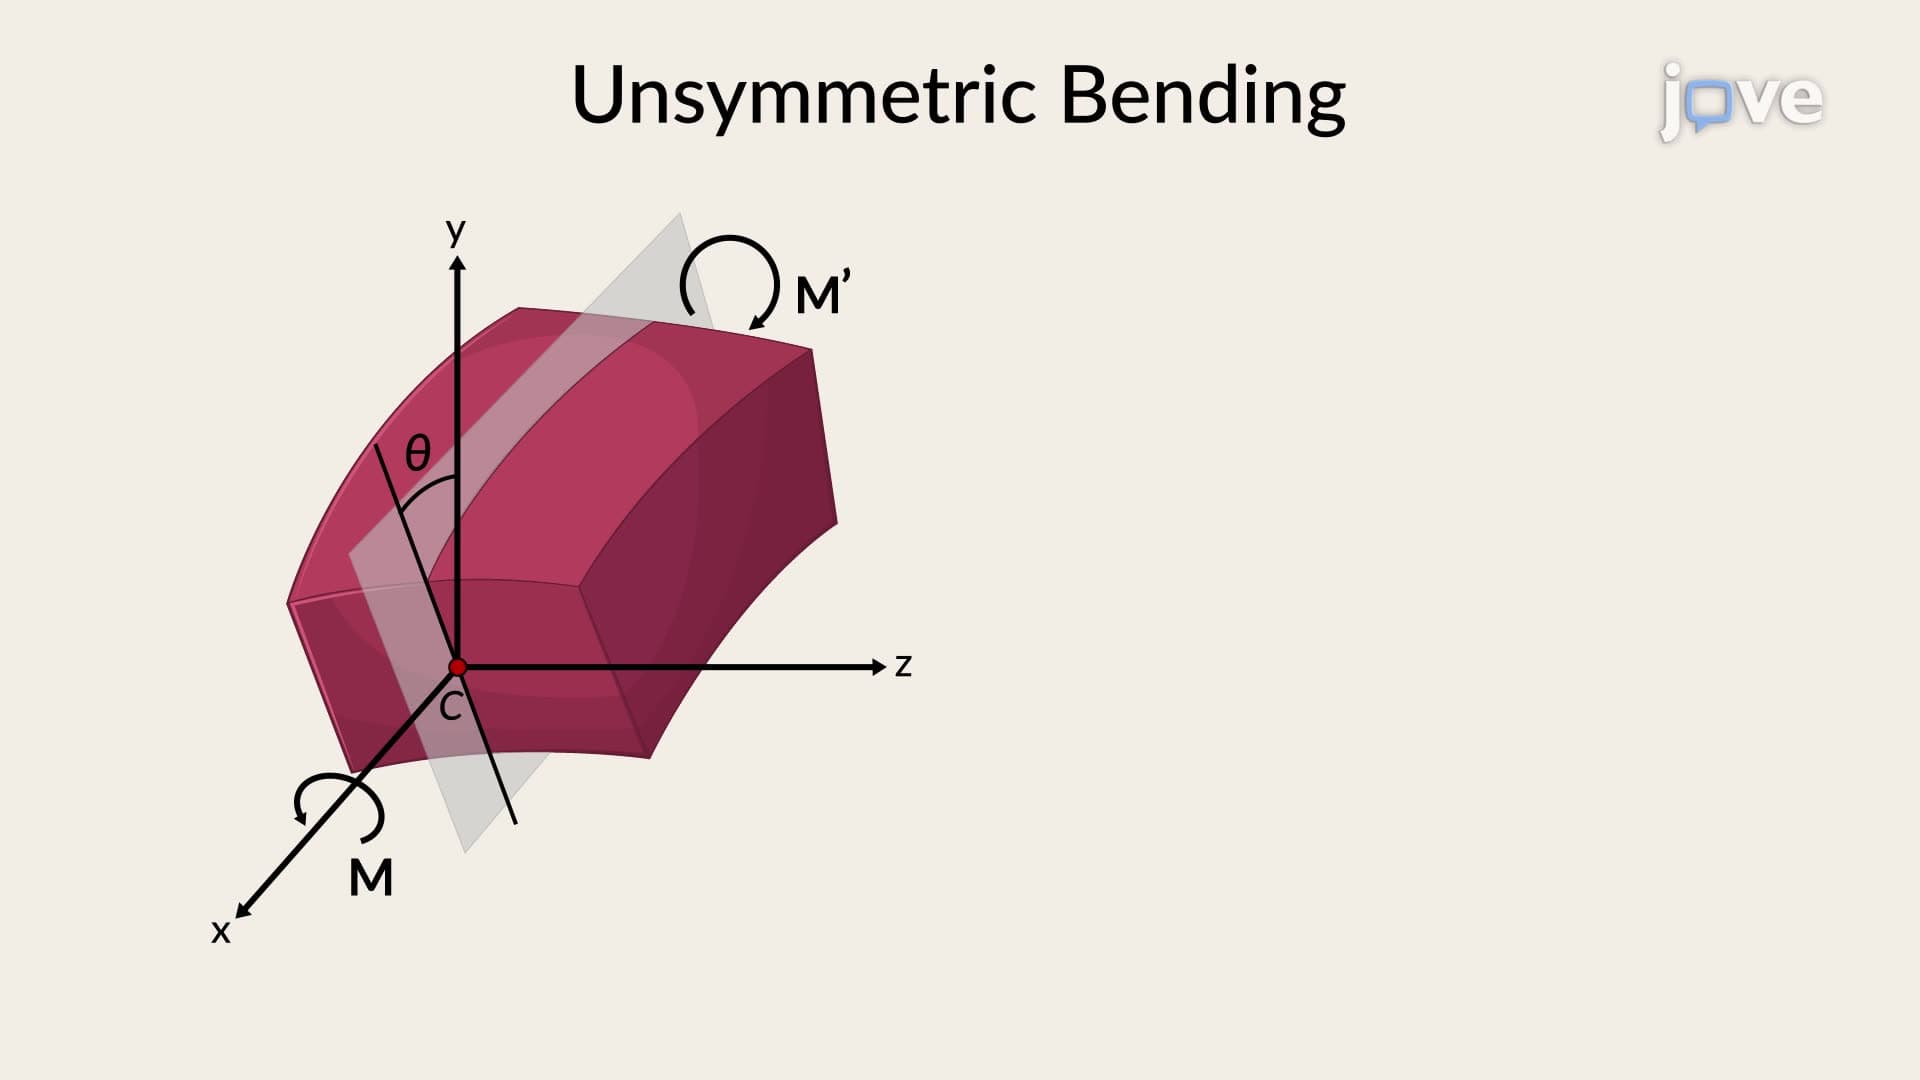
Unsymmetric Bending - Angle of Neutral Axis
When a bending moment is applied at an angle θ concerning the vertical axis of a symmetrical member, it can be resolved into components along the member's principal...