Related Experiment Video
Updated: Nov 10, 2025
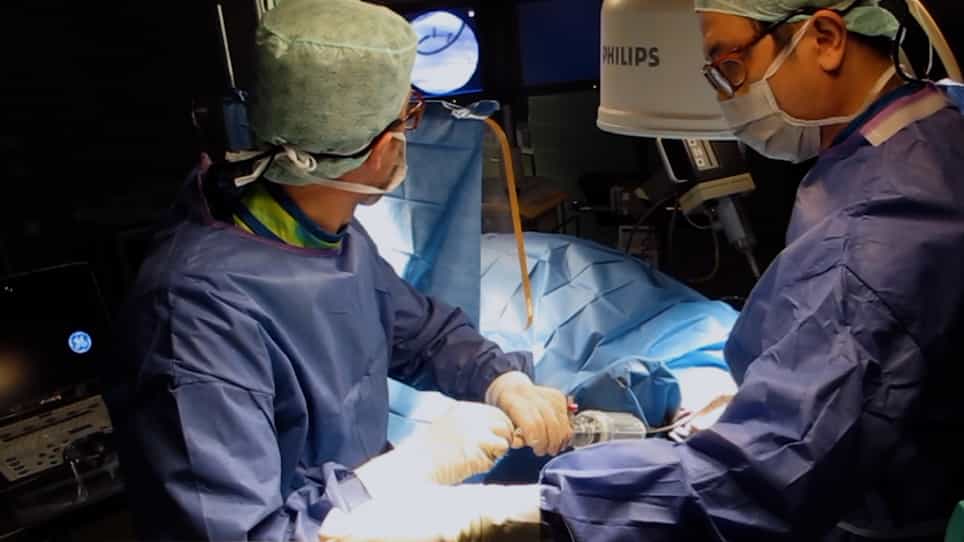
Transcatheter Pulmonary Valve Replacement from Autologous Pericardium with a Self-Expandable Nitinol Stent in an Adult Sheep Model
Published on: June 8, 2022
Non-contrast transoesophageal echo-guided transapical transcatheter aortic valve replacement: 10-year experience of a
Victor X Mosquera1,2, Alberto Bouzas-Mosquera2,3, Yago Vilela-González1
1Department of Cardiac Surgery, Complejo Hospitalario Universitario de A Coruña, A Coruña, Spain.

Objectives:
This study aims to evaluate the efficacy, safety and long-term outcomes of a renoprotective non-contrast, transoesophageal echocardiography-guided transapical (TA) transcatheter aortic valve replacement (TAVR) strategy with a balloon-expandable prosthesis, as well as to determine its impact on renal function.
Methods:
Between 2009 and 2019, 200 consecutive patients underwent a non-contrast, transoesophageal echocardiography-guided TA TAVR with a balloon-expandable prosthesis.
Results:
The device success rate was 95.5%. Transoesophageal echocardiography-guided deployment demonstrated a low rate of procedure-related complications: 9.5% of acute kidney injury, 8% postoperative bleeding, 6% low-cardiac output, 4.5% postprocedural aortic regurgitation ≥+2, 4% implantation of permanent pacemaker and 2% stroke. There were no significant differences between preoperative and on discharge estimated glomerular filtration rate (53.9 ± 22.2 vs 54.3 ± 22.9 ml/min/1.73 m2, P = 0.60). Logistic regression analysis confirmed postoperative bleeding as an independent predictor for acute kidney injury (odds ratio (OR) 11.148, 95% confidence interval 3.537-35.140, P < 0.001). In-hospital mortality was 7.5%. The mean follow-up was 48.5 ± 39.9 months. Renal function and patient's chronic kidney disease stage did not significantly vary during follow-up. Long-term cumulative survival at 1, 5 and 10 years was 84.2 ± 0.027%, 42.9 ± 0.038% and 32.5 ± 0.044%, respectively. Renal function affected on neither in-hospital mortality nor long-term survival.
Conclusions:
Non-contrast, transoesophageal echocardiography-guided TA TAVR is a safe and reproducible technique with a low incidence of periprocedural complications that avoids the use of contrast and mitigates the incidence of acute kidney injury.


Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:25
Aortic Regurgitation III: Medical Management