Related Experiment Video
Updated: Nov 9, 2025
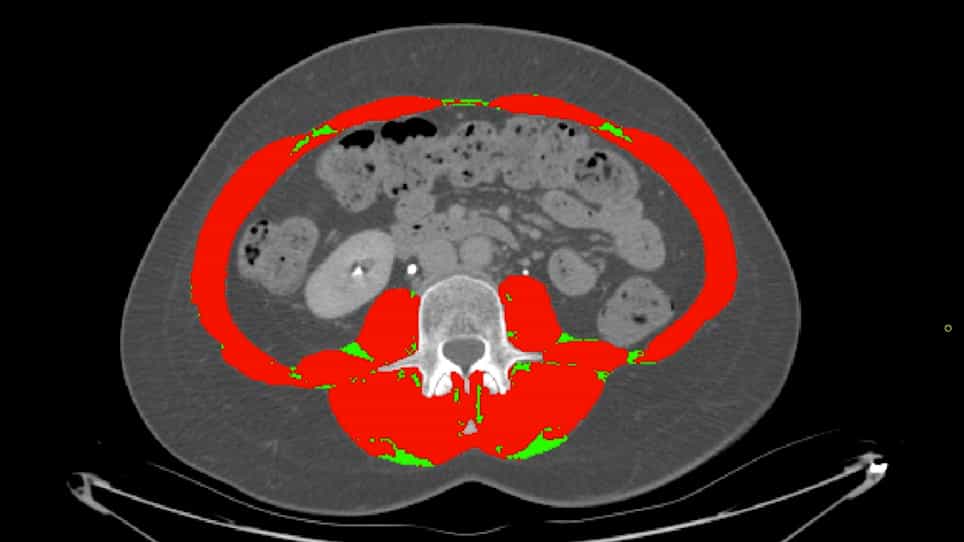

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Frequency of Sarcopenia, Sarcopenic Obesity, and Changes in Physical Function in Surgical Oncology Patients Referred
An Ngo-Huang1, Aliea Herbert2, Rhodora C Fontillas1
1The University of Texas MD Anderson Cancer Center, Houston, TX, USA.

Purpose:
Sarcopenia and suboptimal performance status are associated with postoperative complications and morbidity in cancer patients. Prehabilitation has emerged as an approach to improve fitness and muscle strength in patients preoperatively. We sought to describe the frequency of sarcopenia and sarcopenic obesity (SO) in a cohort of cancer patients referred for prehabilitation and the association between body composition and physical function.
Methods:
In this retrospective review of 99 consecutive cancer patients referred for prehabilitation prior to intended oncologic surgery, prehabilitation included physical medicine and rehabilitation (PM&R) physician evaluation of function and physical therapy for individualized home-based exercise. Sarcopenic A was defined using sex-adjusted norms of skeletal muscle (SKM), measured using the sliceOmatic software (TomoVision, 2012) on computed tomography images at baseline. Sarcopenic B was defined by abnormal SKM and physical function. SO was defined as sarcopenia with BMI ≥ 25. Six-minute walk test (6MWT), 5 times sit-to-stand (5×STS), and grip strength were obtained at consultation (baseline) and at preoperative follow-up (if available).
Results:
Forty-nine patients (49%) were Sarcopenic A, 28 (28%) SO, and 38 (38%) Sarcopenic B. Age was negatively correlated with SKM (P = .0436). There were no significant associations between Sarcopenic A/B or SO with baseline or changes in physical function. Assessed by sex, Sarcopenic A females had low 5×STS (P = .04) and Sarcopenic B females had low GS (P = .037). Sarcopenic B males had low preoperative GS (P = .026). 6MWT and grip strength at baseline were lower than age- and sex-related norms (both P < .001). Preoperatively, 6MWT distance and 5×STS time improved (both P < .001). Functional improvement in the sarcopenic and nonsarcopenic patients did not differ according to sex.
Conclusions:
In this cohort of prehabilitation surgical oncology patients, frequencies of sarcopenia and SO were high, and baseline physical function was abnormal but improved significantly regardless of body composition. These findings suggest that patients have considerable prehabilitation needs and are capable of improving with comprehensive care.

Related Concept Videos
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management