Related Experiment Video
Updated: Nov 8, 2025
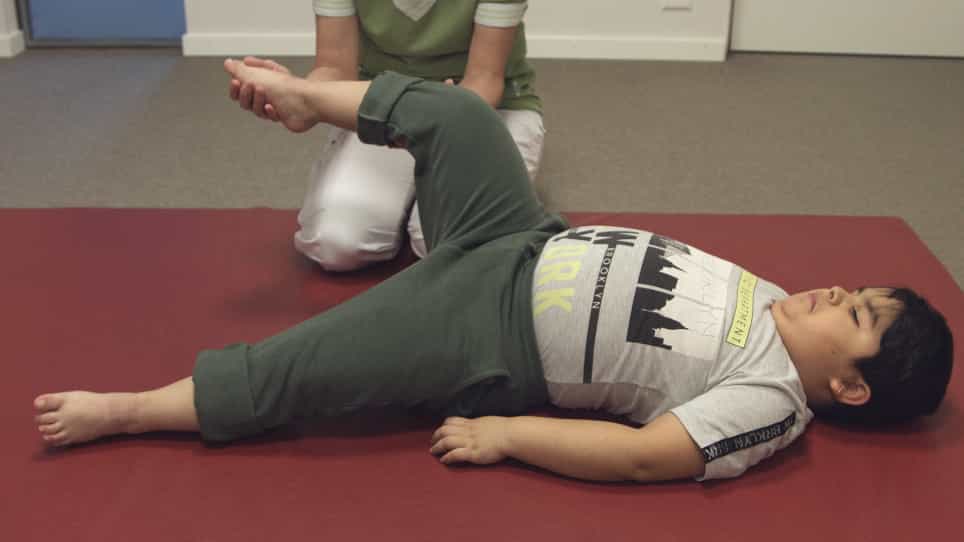

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Thoracoabdominal asynchrony and paradoxical motion in Duchenne muscular dystrophy and healthy subjects during cough:
Layana Marques1,2, Guilherme Augusto de Freitas Fregonezi1,2, Ana Aline Marcelino1,2
1Departamento de Fisioterapia, Pneumo CardioVascular Lab/HUOL, Hospital Universitário Onofre Lopes, Empresa Brasileira de Serviços Hospitalares (EBSERH), Universidade Federal do Rio Grande do Norte, Natal, Rio Grande do Norte, Brasil.

Objective:
To assess thoracoabdominal asynchrony (TAA) and inspiratory paradoxical motion at different positionings in subjects with Duchenne muscular dystrophy (DMD) versus healthy subjects during quiet spontaneous breathing (QB) and cough.
Methods:
This is a case control study with a matched-pair design. We assessed 14 DMD subjects and 12 controls using optoelectronic plethysmography (OEP) during QB and spontaneous cough in 3 positions: supine, supine with headrest raised at 45°, and sitting with back support at 80°. The TAA was assessed using phase angle (θ) between upper (RCp) and lower rib cage (RCa) and abdomen (AB), as well as the percentage of inspiratory time the RCp (IPRCp ), RCa (IPRCa ), and AB (IPAB ) moved in opposite directions.
Results:
During cough, DMD group showed higher RCp and RCa θ (p < .05), RCp and AB θ (p < .05) in supine and 45° positions, and higher RCp and Rca θ (p = .006) only in supine position compared with controls. Regarding the intragroup analysis, during cough, DMD group presented higher RCp and AB θ (p = .02) and RCa and AB θ (p = .002) in supine and higher RCa and AB θ (p = .002) in 45° position when compared to 80°. Receiver operating characteristic curve analyzes were able to discriminate TAA between controls and DMD in RCa supine position (area under the curve: 0.81, sensibility: 78.6% and specificity: 91.7%, p = .001).
Conclusion:
Subjects with DMD yields TAA with insufficient deflation of chest wall compartments and rib cage distortion during cough, by noninvasive assessment.


Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction