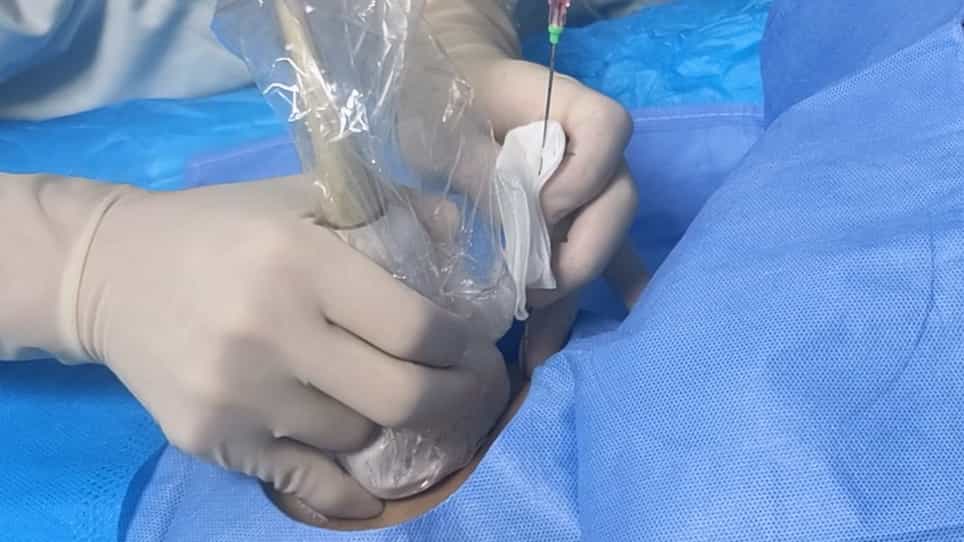
Related Experiment Video
Updated: Nov 7, 2025

Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
Comparison of metal stents versus plastic stents for preoperative biliary drainage: a meta-analysis of five
Wei Zhang1, Lin Xu2, Xu Che1,2
1Department of Pancreatic and Gastric Surgery, National Cancer Center/National Clinical Research Center for Cancer/Cancer Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Background:
Although routine preoperative biliary drainage (PBD) is generally not recommended for patients with malignant distal biliary obstruction (MDBO), it is still necessary in many cases. The objective of this study is to compare the effects of metal stents (MSs) and plastic stents (PSs) on PBD in patients with MDBO.
Methods:
All the randomized controlled trials (RCTs) that compared MS with PS for PBD and published from the date of database establishment to September 2020 were identified by searching the PubMed, EMBASE and Cochrane databases.
Results:
Five RCTs involving 445 patients were included. There were 201 cases in the MS group, with 244 in the PS group. Re-interventions (relative risk (RR) = 0.40, 95% confidence interval (CI) 0.21-0.75, P = 0.004), stent occlusions (RR = 0.36, 95% CI 0.18-0.75, P = 0.006), postoperative complications (RR = 0.76, 95% CI 0.59-0.97, P = 0.03) and preoperative cholangitis (RR = 0.19, 95% CI 0.05-0.78, P = 0.02) were lower in the MS group than in the PS group. Preoperative pancreatitis (RR = 2.11, 95% CI 1.06-4.19, P = 0.03) was higher in the MS group than in the PS group. No significant difference was observed in the overall preoperative complications, postoperative pancreatic fistulas, delayed gastric emptying, wound infections and postoperative bleeding between these two groups.
Conclusions:
MS and PS exerted a similar effect on PBD, but PS had a higher risk of preoperative stent obstruction and postoperative complications, requiring more frequent interventions preoperatively. However, larger sample and higher quality RCTs are necessary for further verification.