Related Experiment Video
Updated: Nov 7, 2025

A Modified Sonographic Algorithm for Image Acquisition in Life-Threatening Emergencies in the Critically Ill Newborn
Published on: April 7, 2023
The Association of Workload and Outcomes in the Pediatric Cardiac ICU
Michael P Fundora1, Jiayi Liu2, Christina Calamaro3
1Division of Cardiology, Department of Pediatrics, Children's Healthcare of Atlanta, Emory University School of Medicine, Atlanta, GA.

Insights
High healthcare workload, indicated by increased bed occupancy and lower frontline provider staffing, is linked to worse patient outcomes and more testing in pediatric cardiac ICUs. This highlights the impact of staffing levels on care quality and efficiency.
Area of Science:
- Pediatric Cardiac Critical Care
- Healthcare Operations
- Clinical Outcomes Research
Background:
- Healthcare workload is a critical factor influencing patient outcomes.
- Bed occupancy is often used as a surrogate for workload, but frontline provider workload is less studied.
- Understanding the impact of frontline provider workload is essential for optimizing care in intensive settings.
Purpose of the Study:
- To investigate the association between frontline provider workload, measured by bed occupancy and staffing levels, and patient outcomes in a pediatric cardiac intensive care unit (ICU).
- To determine if increased workload correlates with increased unnecessary testing and prolonged length of stay.
- To identify the impact of high occupancy and low staffing on mortality and resource utilization.
Main Methods:
- A retrospective analysis of patient data from a tertiary pediatric cardiac ICU was conducted.
- Time-stamped orders, provider data, and patient demographics were collected for admissions between January 2018 and December 2019.
- Regression analysis was used to assess the influence of bed occupancy and provider staffing on orders, length of stay, and mortality, controlling for various clinical factors.
Main Results:
- A 10% increase in bed occupancy was associated with a 7.2% rise in imaging orders, a 3% increase in laboratory turnaround time, and an additional 3 days to length of stay.
- Higher frontline provider staffing (>3 providers) correlated with a 6% decrease in imaging orders and a 3% decrease in laboratory orders.
- Periods of high bed occupancy (>89%) were significantly linked to longer ICU stays and increased mortality.
Conclusions:
- Increased bed occupancy and reduced frontline provider staffing are associated with adverse outcomes, including higher mortality and longer lengths of stay.
- High workload conditions in the cardiac ICU exacerbate system performance, negatively impacting patient care.
- Optimizing staffing and managing bed occupancy are crucial for improving patient outcomes and operational efficiency in pediatric cardiac ICUs.
Objectives:
Healthcare workload has emerged as an important metric associated with poor outcomes. To measure workload, studies have used bed occupancy as a surrogate. However, few studies have examined frontline provider (fellows, nurse practitioners, physician assistants) workload and outcomes. We hypothesize frontline provider workload, measured by bed occupancy and staffing, is associated with poor outcomes and unnecessary testing.
Design:
A retrospective single-center, time-stamped orders, ordering provider identifiers, and patient data were collected. Regression was performed to study the influence of occupancy on orders, length of stay, and mortality, controlling for age, weight, admission type, Society of Thoracic Surgery-European Association for Cardio-Thoracic Surgery Congenital Heart Surgery Mortality score, diagnosis, number of surgeries, orders, provider staffing, attending experience, and time fixed effects.
Setting:
Twenty-seven bed tertiary cardiac ICU in a free-standing children's hospital.
Patients:
Patients (0-18 yr) admitted to the pediatric cardiac ICU, January 2018 to December 2019.
Interventions:
None.
Measurements And Main Results:
There were 16,500 imaging and 73,113 laboratory orders among 1,468 patient admissions. Median age 6 months (12 d to 5 yr), weight 6.2 kg (3.7-16.2 kg); 840 (57.2%) surgical and 628 (42.8%) medical patients. ICU teams consisted of 16 attendings and 31 frontline providers. Mortality 4.4%, median stay 5 days (2-11 d), and median bed occupancy 89% (78-93%). Every 10% increase in bed occupancy had 7.2% increase in imaging orders per patient (p < 0.01), 3% longer laboratory turn-around time (p = 0.015), and 3 additional days (p < 0.01). Higher staffing (> 3 providers) was associated with 6% less imaging (p = 0.03) and 3% less laboratory orders (p = 0.04). The number of "busy days" (bed occupancy > 89%) was associated with longer stays (p < 0.01), and increased mortality (p < 0.01).
Conclusions:
Increased bed occupancy and lower staffing were associated with increased mortality, length of stay, imaging orders, and laboratory turn-around time. The data demonstrate performance of the cardiac ICU system is exacerbated during high occupancy and low staffing.
More Related Videos
 03:47
Author Spotlight: Workflow for Integrating POCUS Data into EHR for Managing Heart Failure Patients
Published on: July 12, 2024
 10:38
Observational Study Protocol for Repeated Clinical Examination and Critical Care Ultrasonography Within the Simple Intensive Care Studies
Published on: January 16, 2019
Related Concept Videos
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:19
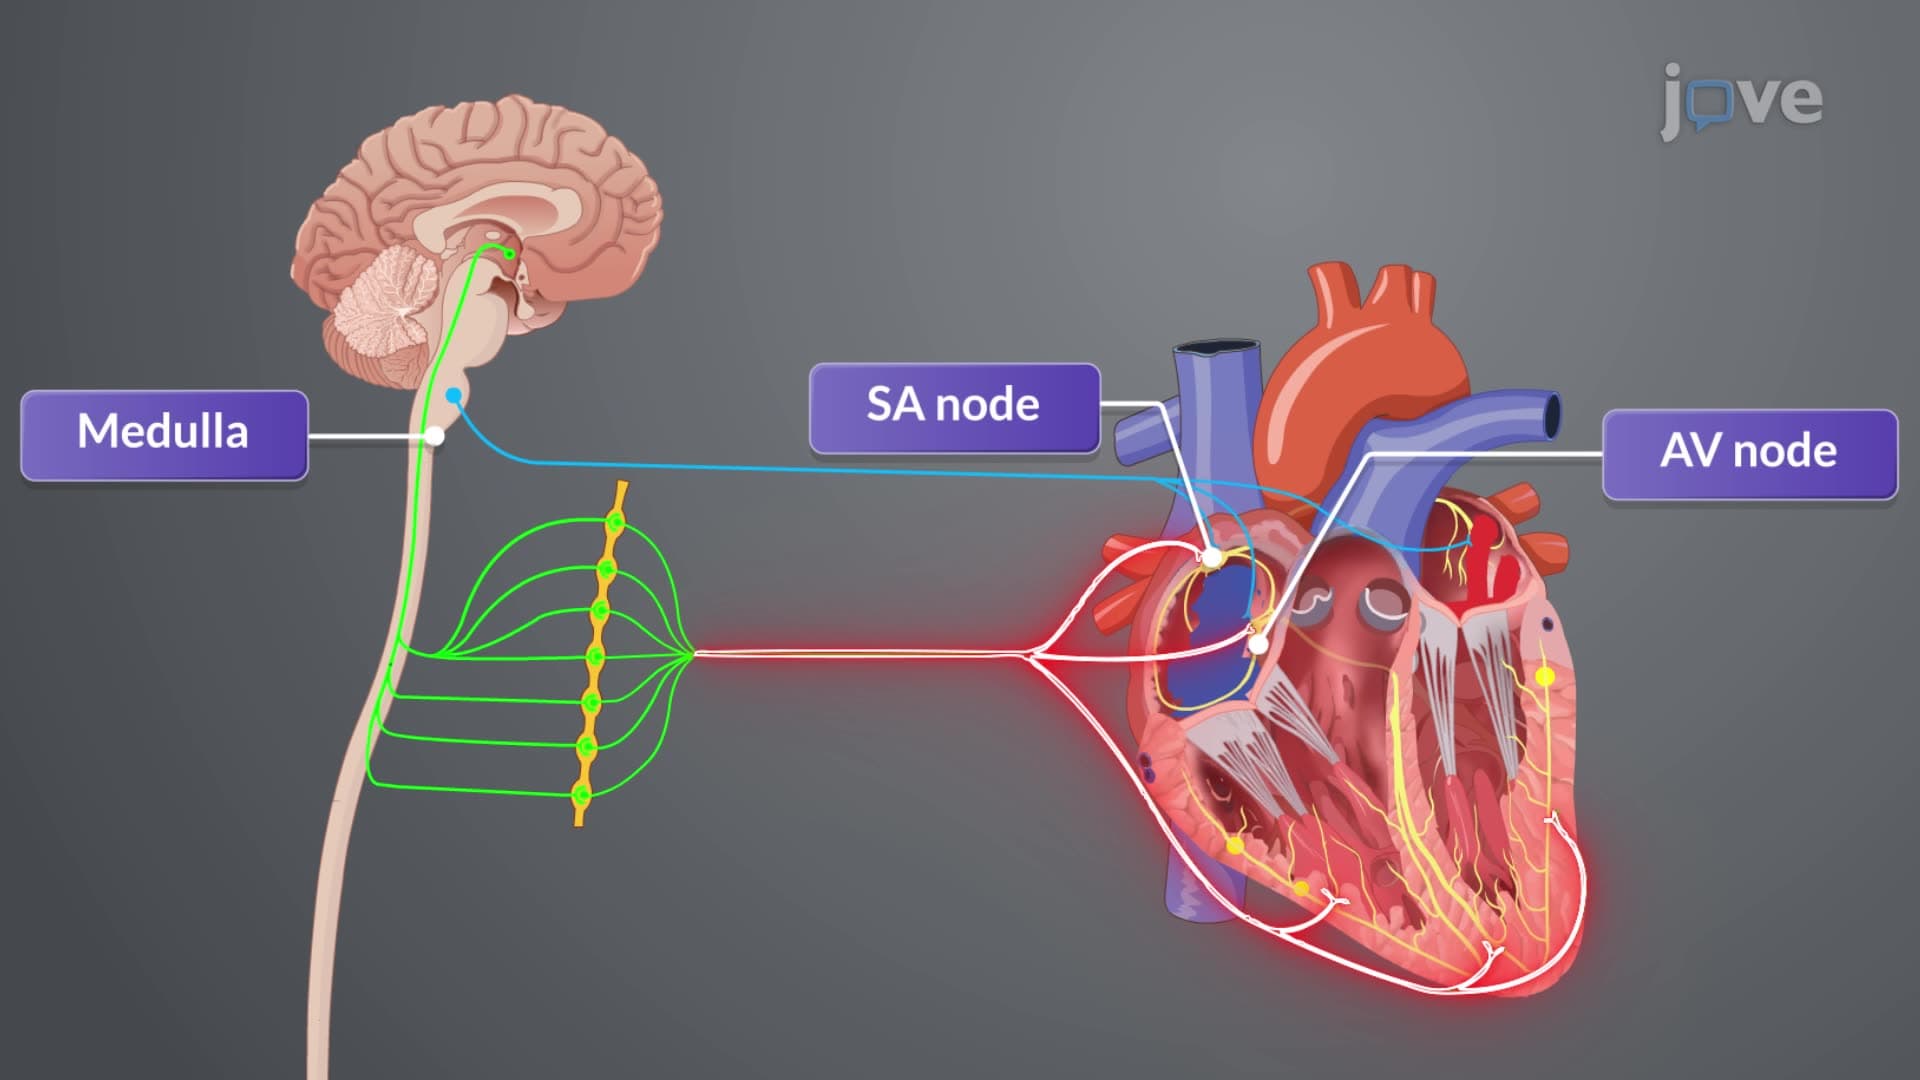
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:29
Cardiomyopathy V: Interprofessional Care
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:26
Cardiac Catheterization IV: Nursing Management