Related Experiment Video
Updated: Nov 6, 2025


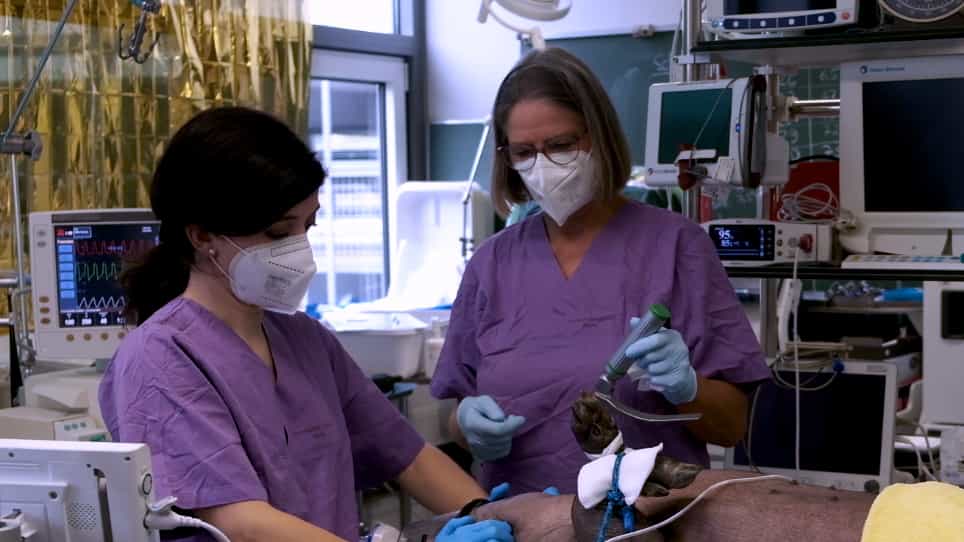
Endotracheal Intubation via Tracheotomy and Subsequent Thoracotomy in Rats for Non-Survival Applications
Published on: March 15, 2024
The impact of a barrier enclosure on time to tracheal intubation: a randomized controlled trial
Tim T H Jen1,2, Vionarica Gusti3, Charanjit Badh4,5
1Department of Anesthesia, St. Paul's Hospital/Providence Health Care, 1081 Burrard St, Vancouver, BC, V6Z 1Y6, Canada. timothy929@gmail.com.

Purpose:
Novel devices such as the barrier enclosure were developed in hopes of improving provider safety by limiting SARS-CoV-2 transmission during tracheal intubation. Nevertheless, concerns arose regarding a lack of rigorous efficacy and safety data for these devices. We conducted a randomized controlled trial to evaluate the impact of the barrier enclosure on time to tracheal intubation.
Method:
After Research Ethics Board approval, elective surgical patients with normal airway predictors were randomly allocated 1:1 to tracheal intubation with or without a barrier enclosure. The primary outcome was time to tracheal intubation. Secondary outcomes included first-pass success rate, total time of airway manipulation, anesthesiologists' perception of intubation difficulty, likelihood of use in SARS-CoV-2-positive patients, and patients' perception of comfort and acceptability.
Results:
There were 48 participants in the barrier enclosure group and 46 participants in the control group. The mean (standard deviation [SD]) time to tracheal intubation was 62 (29) sec with barrier closure and 53 (27) sec without barrier enclosure (mean difference, 9 sec; 95% confidence interval, - 3 to 20; P = 0.14). Anesthesiologists rated the difficulty of intubation higher with barrier enclosure (mean [SD] visual analogue scale score, 27 [26] mm vs 9 [17] mm; P < 0.001). There were no significant differences in other secondary outcomes.
Conclusion:
In healthy surgical patients with normal airway predictors, the use of a barrier enclosure during tracheal intubation did not significantly prolong time to intubation or decrease first-pass intubation success. Nevertheless, there was an increase in difficulty of intubation perceived by the anesthesiologists with use of a barrier enclosure.
Trial Registration:
www.clinicaltrials.gov (NCT04366141); registered 28 April 2020.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...