Related Experiment Video
Updated: May 31, 2026
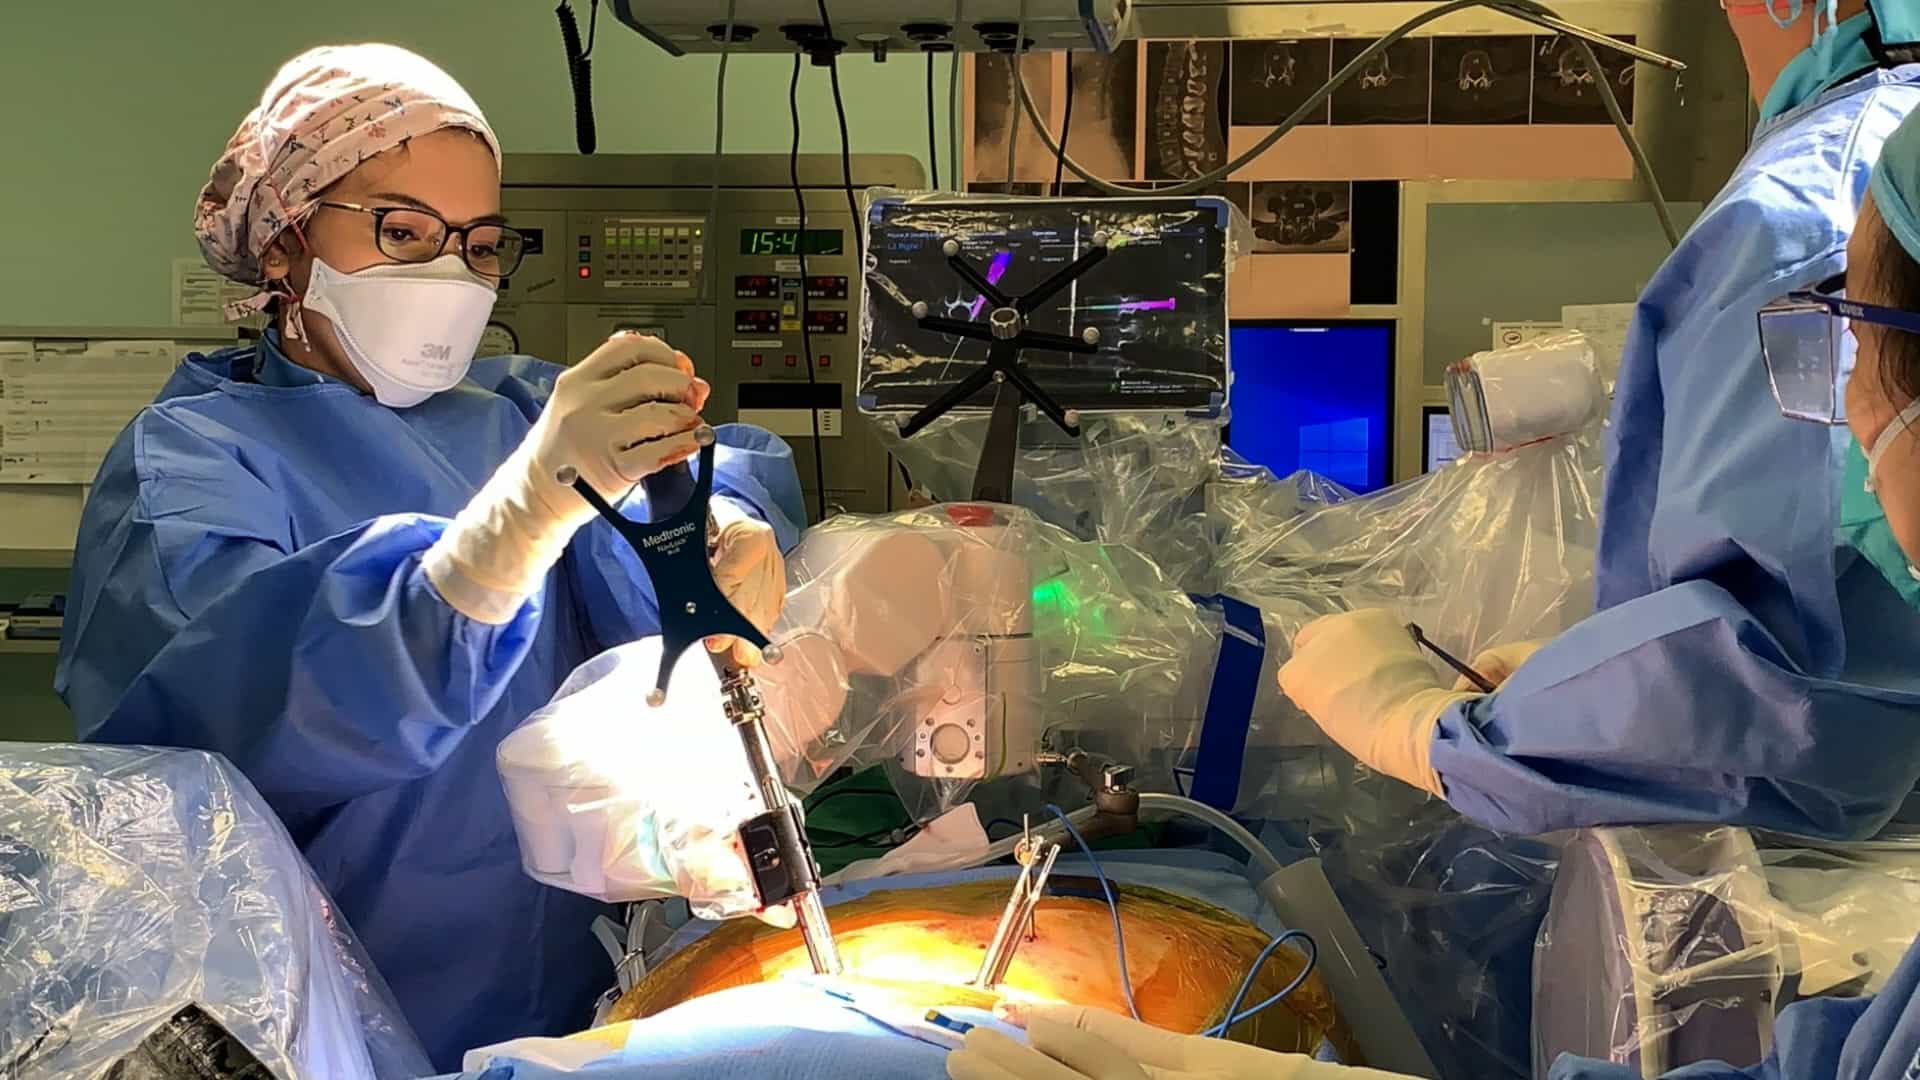

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Cluster analysis identifies high-risk phenotypic groups for revision following 1-3 level lumbar fusion in a
Regina Golding1, Sachin Mehta1, Priya Singh2
1School of medicine, Albert Einstein College of Medicine, 1300 Morris Park Ave, Bronx, NY 10461, United States.

Background:
The number of patients undergoing single- and multilevel lumbar fusion continues to rise. Although prior studies suggest that radiographic factors and preoperative patient-reported outcomes may predict surgical results, evidence regarding the predictive value of patient demographics on perioperative and postoperative outcomes remains limited. Using cluster analysis to define distinct demographic-based patient phenotypes, this study examines how patient demographics influence surgical outcomes in a disadvantaged, inner-city population.
Methods:
This is a retrospective, single-center cohort study including 459 patients who underwent a 1-3 level lumbar fusion between 2022 and 2024. The primary outcome was revision surgery at maximum follow-up. A 2-step cluster analysis was performed using SPSS 30 (IBM). Comparisons were performed between clusters using Chi-squared test for categorical variables and a one-way ANOVA with Tukey's posttest for continuous variables. Intra-cluster analysis was run using multivariate regression. p < .05 was considered significant.
Results:
A total of 459 patients underwent 1-3 level lumbar fusion (mean age 62.1 ± 10.9 years; 69.0% female; mean body mass index (BMI) 31.3 ± 5.6), with 92.4% identifying as non-white and 29.3% as non-English speaking. Mean operative time was 286 minutes, blood loss 206 mL, and hospital stay 4.7 days. Within 90 days, 19.2% visited the ER, 10.2% were readmitted, and 4.1% returned to the operating room (OR); 5.5% of patients ultimately required revision fusions, and 12.1% remained on chronic opioids at final follow-up. Cluster analysis identified 3 patient subgroups differing significantly by age, language, race, insurance, substance use, psychiatric medication, and prior laminectomy (all p < .001). Cluster 1 (younger, psychiatric/substance use) had higher revision rates (9.1% vs. 2.0-3.1%, p = .01).
Conclusions:
Distinct patient groups show differing lumbar fusion risks; younger patients with psychiatric and substance-use factors face higher revision rates and potentially worse recovery.