Related Experiment Video
Updated: Nov 4, 2025


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Robot-assisted total extraperitoneal para-aortic and pelvic lymphadenectomy
Shiori Yanai1, Kiyoshi Kanno1, Shintaro Sakate1
1Department of Obstetrics and Gynecology, Kurashiki Medical Center, Okayama, Japan.

Abstract:
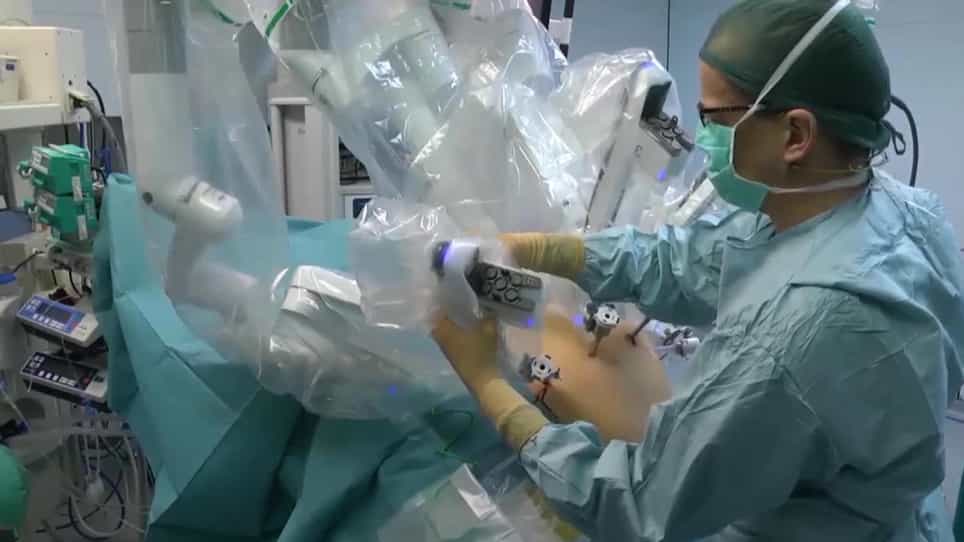
Robot-assisted extraperitoneal para-aortic lymphadenectomy has been reported to be feasible option for the surgical management of gynecologic malignancy previously (Narducci et al., 2009) (Hudry et al., 2019). We have reported the feasibility of laparoscopic extraperitoneal total para-aortic and pelvic lymphadenectomy (Andou, 2016). This article aims to show the safety of robot-assisted extraperitoneal "total para-aortic and pelvic" lymphadenectomy. The video is the staging surgery for 67-year-old woman suspected clinical stage IA ovarian clear cell carcinoma after abdominal hysterectomy and salpingo-oophorectomy. As abdominal adhesion was predicted, she was treated using robot-assisted extraperitoneal total para-aortic and pelvic lymphadenectomy. The patient was placed in the supine position and tilted 7 degrees to the right. Three robot arms were docked at the patient's left side. The center port was used for the scope. The bipolar cutting method was performed using the surgeon's right hand. An AirSeal® port (ConMed, Utica, NY, USA) was placed on the side near the assistant. After the extraperitoneal space was expanded, lymphadenectomy was performed up to the renal veins and below to the obturator muscles using the bipolar cutting method. This was followed by omentectomy. The operative time were 189 min, and the estimated blood loss was 75 ml. A total of 56 lymph nodes were harvested (22 para-aortic lymph nodes and 34 pelvic lymph nodes). Total extraperitoneal lymphadenectomy by robot-assisted surgery was a feasible procedure for this patient. The procedure, which does not require the Trendelenburg position and is not obstructed by bowel, may be suitable for patients with hypertension, glaucoma, obesity or abdominal adhesion.