Related Experiment Video
Updated: Nov 4, 2025


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
Pelvic floor function and morphological abnormalities in primiparas with postpartum symptomatic stress urinary
Yan Hongliang1, Li Pengfei2, Jin Cuiping1
1Obstetrics and Gynecology Department, Tianjin Hospital, Tianjin, China.

Introduction And Hypothesis:
The aim of this study was to assess pelvic floor muscle (PFM) morphology and function in primiparas with postpartum symptomatic SUI after different types of delivery.
Methods:
Retrospective analyses were carried out with individuals with postpartum symptomatic stress urinary incontinence (SUI). Among the women screened in our center from January 2018 to December 2019, participants were divided into elective cesarean section (eCS) and spontaneous vaginal delivery (sVD) groups, while being matched 1:1 on age (±5 years), body mass index (BMI; ±0.5 kg/m2), neonatal birth weight (±300 g), gestational age (±1 week), degree of pelvic organ prolapse quantification (POP-Q), International Consultation on Incontinence Questionnaire-Urinary Incontinence Short Form (ICIQ-UI SF) degree, Incontinence Impact Questionnaire short form (IIQ-7) score, and postpartum days (±10 days); all participants had no sphincter defects or levator ani muscle avulsion. The bioelectrical activity of the PFM was collected using an endovaginal electrode with the Glazer protocol. For the assessment of PFM function, PFM morphometry was evaluated with 3D/4D transperineal ultrasound.
Results:
A total of 78 matched pairs were recruited based on delivery mode. Regarding functional differences, both fast-twitch and slow-twitch fiber strengths in the eCS group were significantly higher than those in the sVD group, but PFMs were more hyperactive in the eCS group. Regarding morphometric differences, the retrovesical angle (RVA) and bladder neck position were not significantly different in the resting state between the two groups, nor was the RVA during the Valsalva maneuver (eCS group: 130.68 ± 17.08°, sVD group: 136.33 ± 23.93°), p > 0.05. There were differences in bladder neck descent (BND; eCS group: 16.51 ± 7.55 mm, sVD group: 23.92 ± 8.47 mm) and urethral rotation angle (URA; eCS group: 37.53 ± 26.05°, sVD group: 59.94 ± 25.87°), all p < 0.05. BND showed a negative correlation with PFM strength, p < 0.05. URAs and RVAs showed no correlation with PFM strength, p > 0.05.
Conclusion:
Pelvic floor muscle function disorder, hyperactivity, and instability also occurred after eCS, which resulted in postpartum symptomatic SUI. The effects of sVD compared with eCS on abnormalities in the lower urinary tract were related to bladder neck and urethral hyperactivity, without an RVA increase.
Related Concept Videos
 01:26
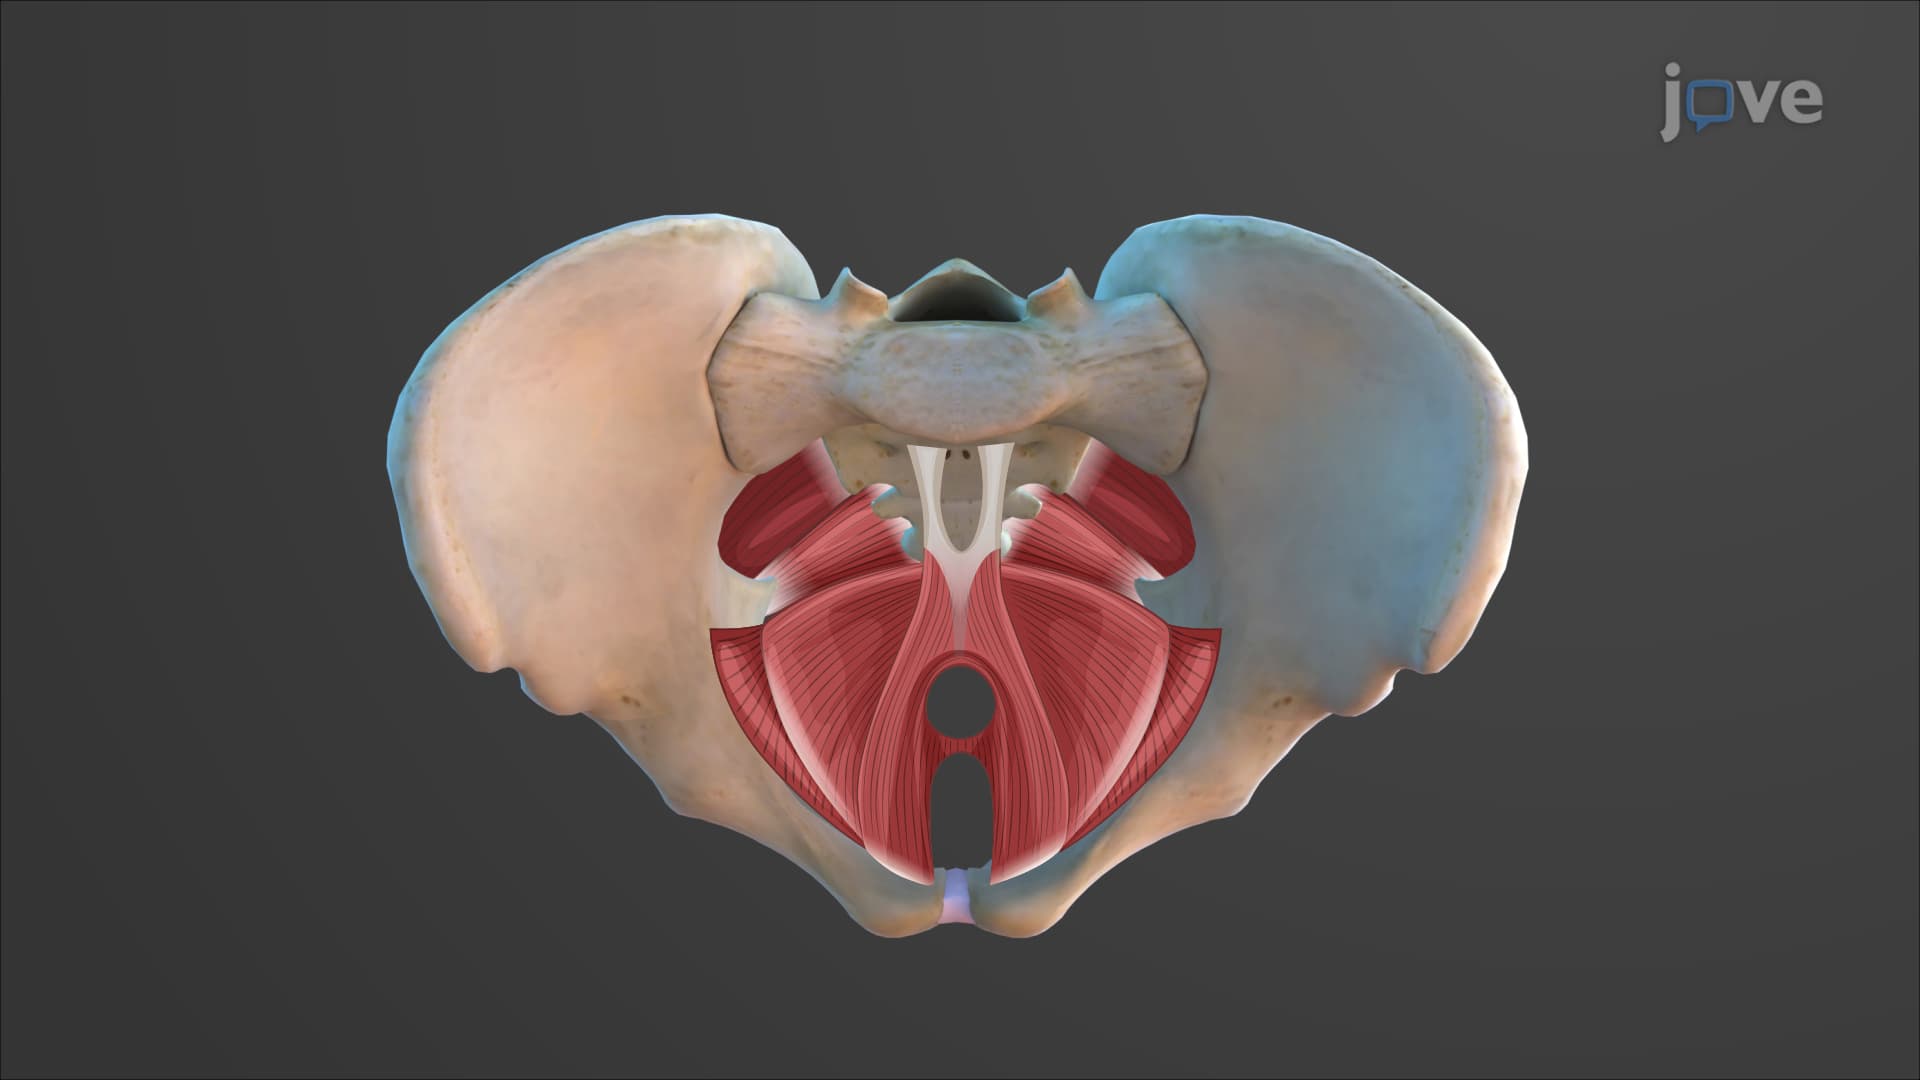
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
 01:19
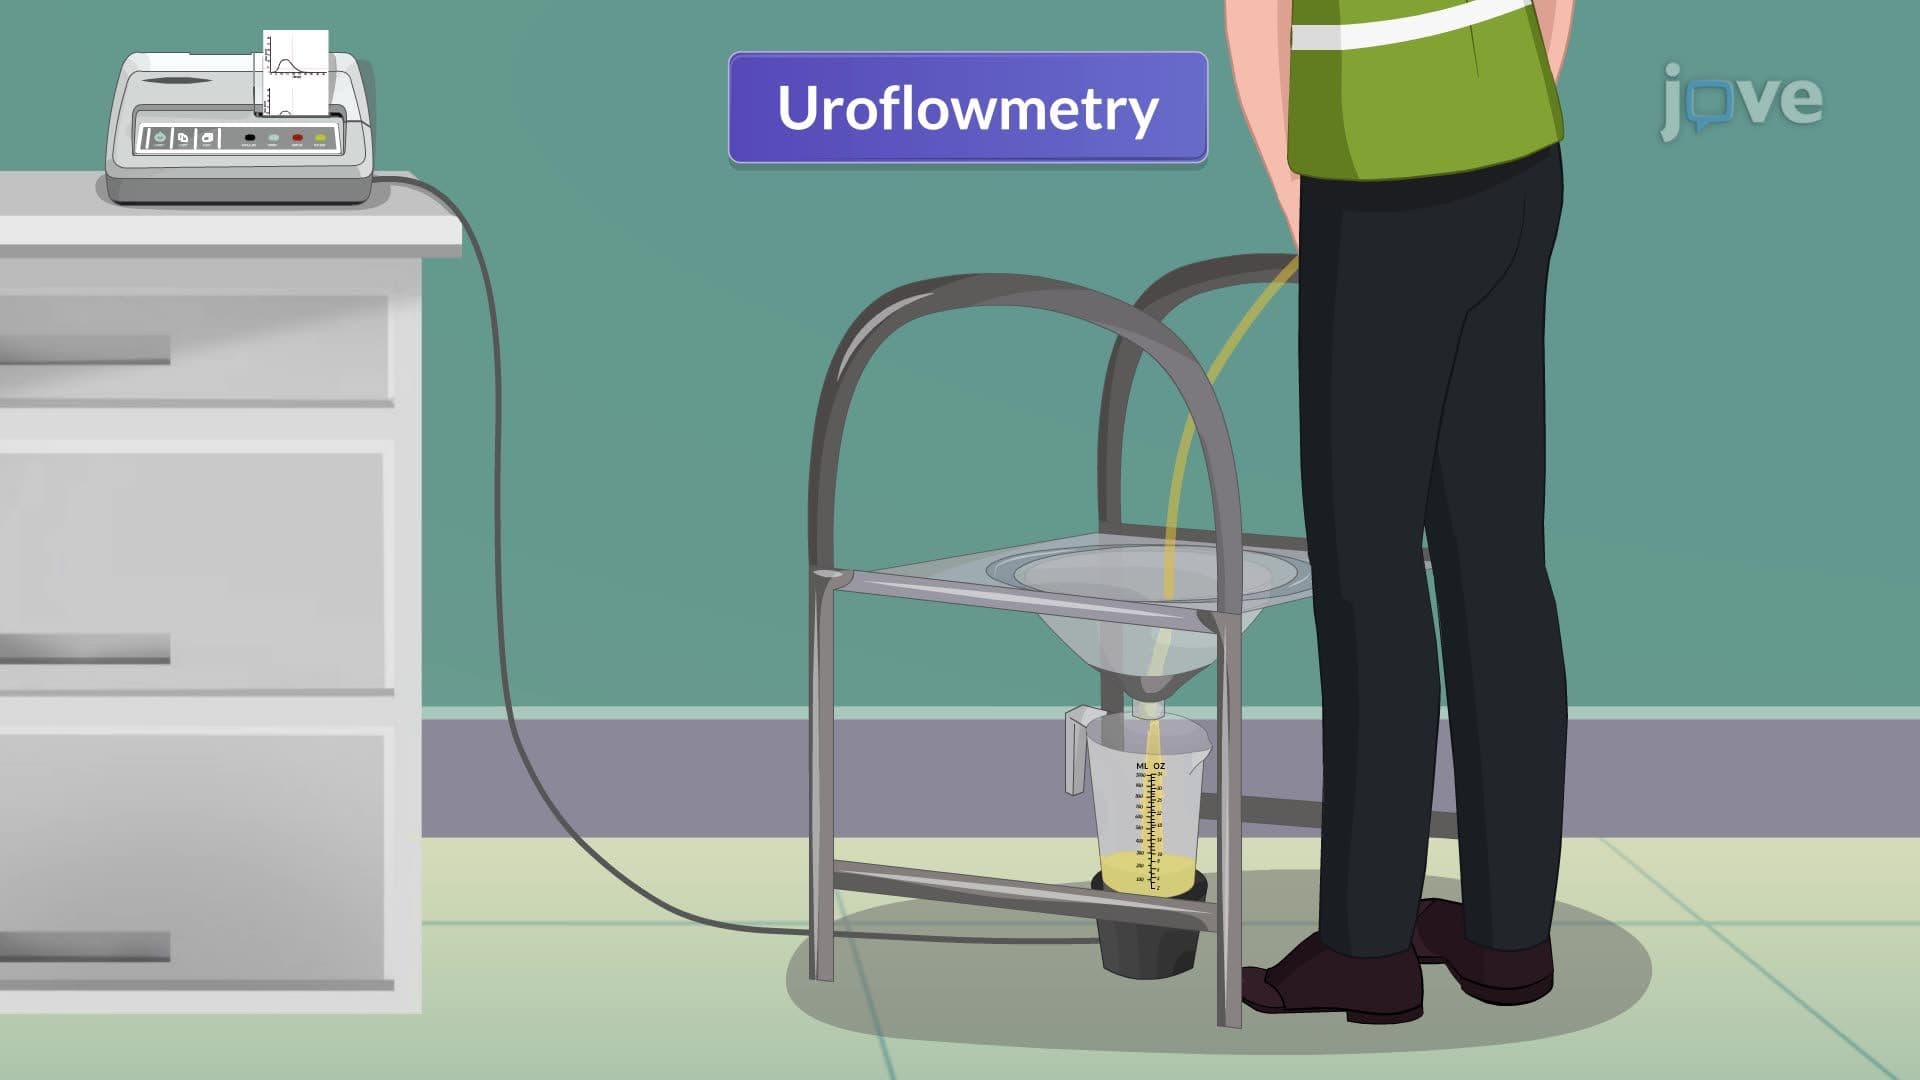
Urodynamic Studies: Uroflowmetry
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...