Related Experiment Video
Updated: Nov 4, 2025


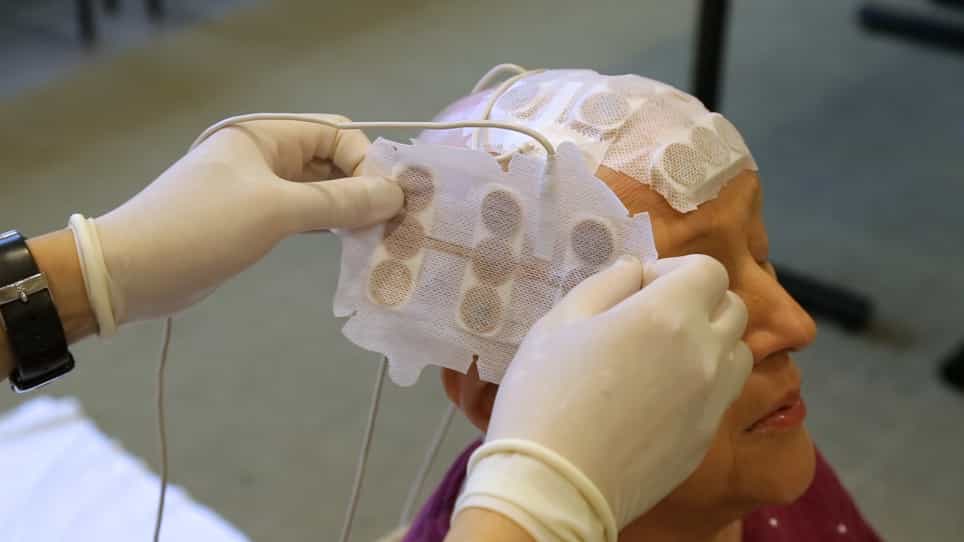
Tumor Treating Field Therapy in Combination with Bevacizumab for the Treatment of Recurrent Glioblastoma
Published on: October 27, 2014
Lessons learned from contemporary glioblastoma randomized clinical trials through systematic review and network
Shervin Taslimi1, Vincent C Ye1, Patrick Y Wen2
1Division of Neurosurgery, Department of Surgery, University of Toronto, Toronto, Ontario, Canada.

Background:
There exists no consensus standard of treatment for patients with recurrent glioblastoma (GB). Here we used a network meta-analysis on treatments from randomized control trials (RCTs) to assess the effect on overall survival (OS) and progression-free survival (PFS) to determine if any consensus treatment can be determined for recurrent GB.
Methods:
We included all recurrent GB RCTs with at least 20 patients in each arm, and for whom patients underwent standard of care at the time of their GB initial diagnosis. Our primary outcome was OS, with secondary outcomes including PFS and adverse reactions. Hazard ratio (HR) and its 95% confidence interval (CI) of the comparison of study arms regarding OS and PFS were extracted from each paper. For comparative efficacy analysis, we utilized a frequentist network meta-analysis, an extension of the classic pair-wise meta-analysis. We followed the Preferred Reporting Items for Systematic Reviews and Meta-analyses.
Results:
Fifteen studies were included representing 29 separate treatment arms and 2194 patients. In our network meta-analysis, combination treatment with tumor-treating field and Vascular endothelial growth factor (VEGF) inhibitor ranked first in improving OS (P = .80). Concomitant anti-VEGF and Lomustine treatment was superior to Lomustine alone for extending PFS (HR 0.57, 95% CI 0.41-0.79) and ranked first in improving PFS compared to other included treatments (P = .86).
Conclusions:
Our analysis highlights the numerous studies performed on recurrent GB, with no proven consensus treatment that is superior to the current SOC. Intertrial heterogeneity precludes drawing strong conclusions, and confidence analysis was low to very low. Further confirmation by future trials is recommended for our exploratory results.
Insights
No consensus treatment for recurrent glioblastoma (GB) exists. Network meta-analysis suggests tumor-treating fields with VEGF inhibitors may improve overall survival, while anti-VEGF and Lomustine improve progression-free survival.
Area of Science:
- Neuro-oncology
- Clinical trial analysis
- Evidence-based medicine
Background:
- Recurrent glioblastoma (GB) lacks a standard treatment protocol.
- Network meta-analysis of randomized control trials (RCTs) is employed to evaluate treatment efficacy.
- Assessing overall survival (OS) and progression-free survival (PFS) aims to identify a consensus treatment for recurrent GB.
Purpose of the Study:
- To determine a consensus treatment for recurrent glioblastoma (GB).
- To assess the effect of various treatments on overall survival (OS) and progression-free survival (PFS) using network meta-analysis.
- To evaluate treatments from randomized control trials (RCTs) in patients with recurrent GB.
Main Methods:
- Included RCTs for recurrent GB with at least 20 patients per arm.
- Extracted hazard ratios (HR) and 95% confidence intervals (CI) for OS and PFS.
- Utilized frequentist network meta-analysis, adhering to PRISMA guidelines.
Main Results:
- Fifteen studies with 29 treatment arms and 2194 patients were analyzed.
- Tumor-treating field combined with VEGF inhibitors showed the highest ranking for improving OS.
- Anti-VEGF plus Lomustine demonstrated superiority over Lomustine alone for PFS.
Conclusions:
- No definitive consensus treatment superior to standard of care (SOC) was identified for recurrent GB.
- Intertrial heterogeneity limits the strength of conclusions, with low to very low confidence.
- Further trials are recommended to confirm these exploratory findings.