
Anatomical study of the thoracic duct and its clinical implications in thoracic and pediatric surgery, a 70 cases
P Y Rabattu1,2, E Sole Cruz1,2,3, N El Housseini1
1LADAF, Anatomical Laboratory, Univ. Grenoble Alpes, Grenoble University Hospital, 38000, Grenoble, France.

Introduction:
Given the high variability and fragility of the thoracic duct, good knowledge of its anatomy is essential for its repair or to prevent iatrogenic postoperative chylothorax. The objective of this study was to define a site where the thoracic duct is consistently found for its ligation. The second objective was to define an anatomically safe surgical pathway to prevent iatrogenic chylothorax in surgery for aortic arch anomalies with vascular ring, through better knowledge of the anatomical relationships of the thoracic duct.
Methods:
Seventy adult formalin-fixed cadavers were dissected. The anatomical relationships of the thoracic duct were reported at the postero-inferior mediastinum, at levels T3 and T4.
Results:
The thoracic duct was consistently situated between the left anterolateral border of the azygos vein and the right border of the aorta between levels T9 and T10, whether it was simple, double, or plexiform. It was located medially, anteromedially, or posteriorly to the left subclavian artery in 51%, 21%, and 28% of the cases, respectively, at the level of T3. At T4, it was posteromedial in 27% of the cases or had no direct relationship with the aortic arch.
Conclusion:
These results favor mass ligation of the thoracic duct at levels T9-T10 between the right border of the aorta and the azygos vein, eventually including the latter. To prevent iatrogenic postoperative chylothorax in aortic arch anomalies with vascular ring surgery, we recommend remaining strictly lateral to the left subclavian artery at the level of T3 to reach the aortic arch anomalies with vascular ring at T4.


Related Concept Videos
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular...
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:19
Veins of Thorax
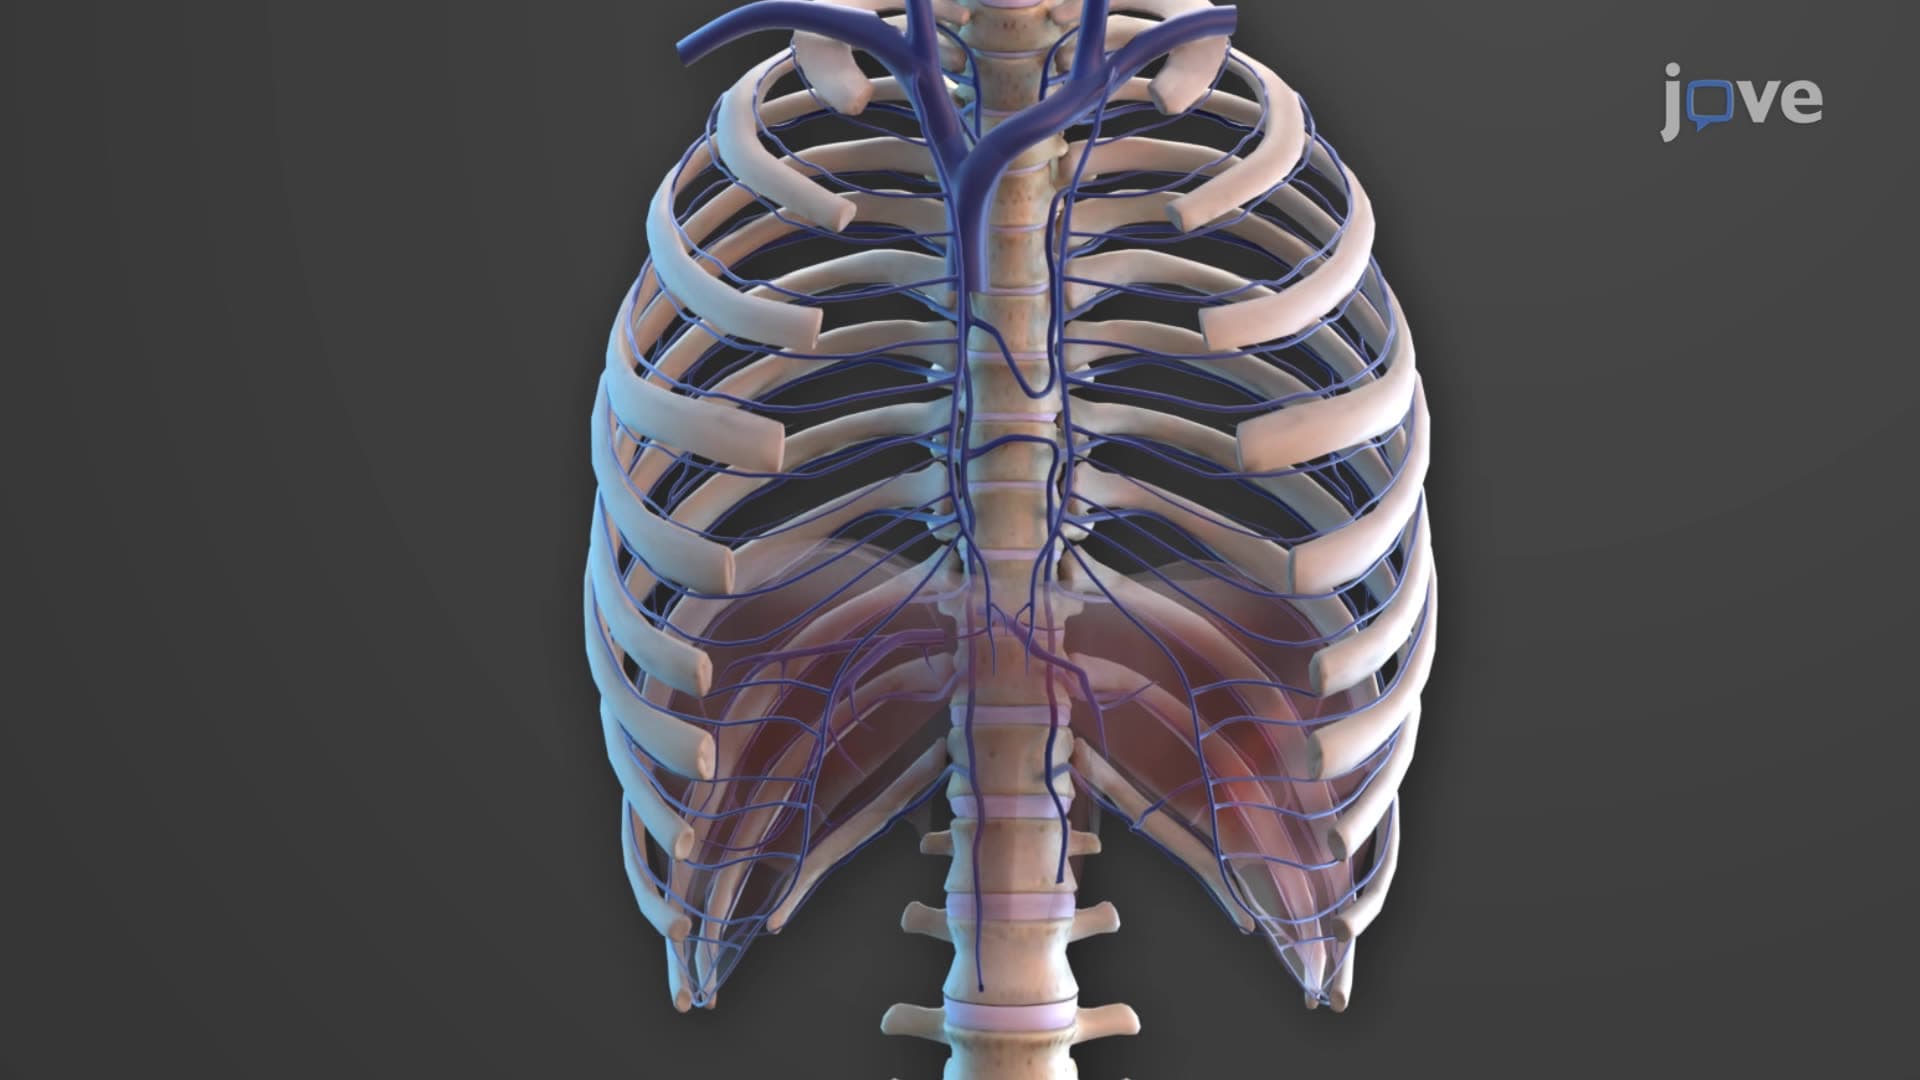
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:15
Development of the Lymphatic System
The first lymph sacs to form are the paired jugular lymph sacs located at the junction of the internal jugular and subclavian veins. From these sacs, lymphatic capillary plexuses extend to the thorax, upper limbs, neck, and head, eventually forming lymphatic vessels. Each jugular lymph sac maintains a...
 01:15
Thoracic Aorta