Related Experiment Video
Updated: Nov 3, 2025
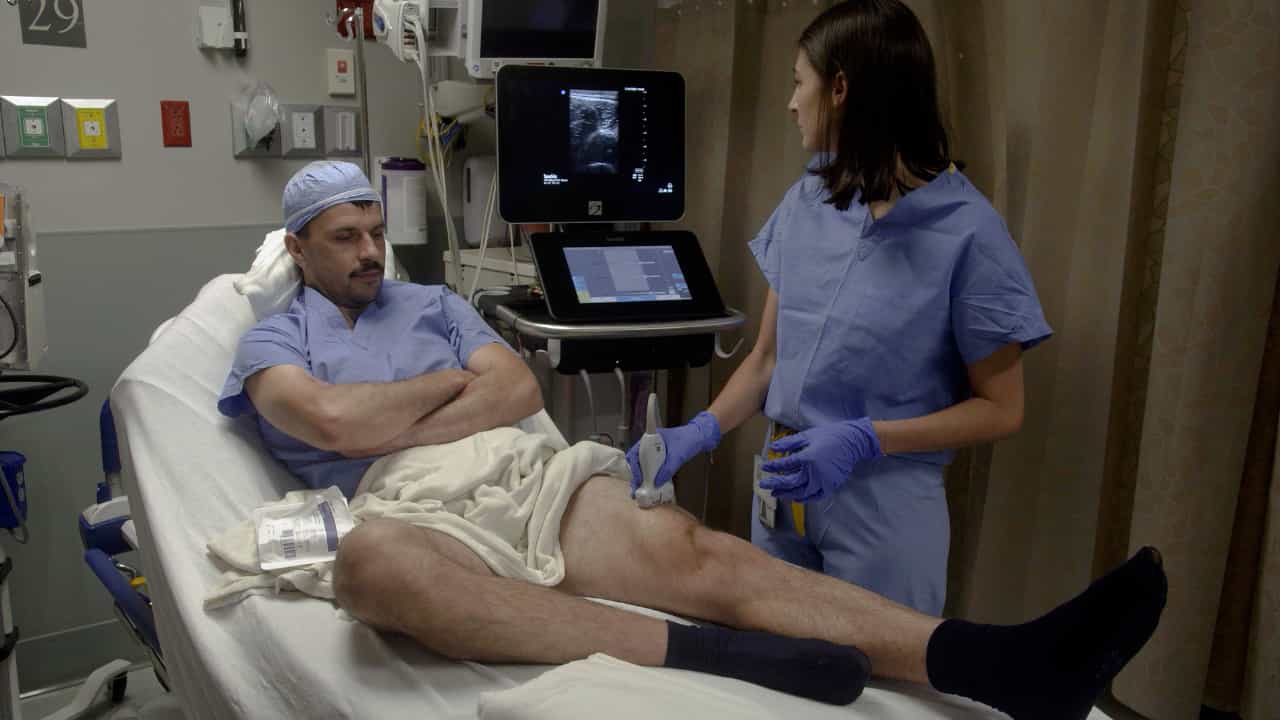

Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Routine Frailty Screening in Critical Illness: A Population-Based Cohort Study in Australia and New Zealand
Jai N Darvall1, Rinaldo Bellomo2, Eldho Paul3
1Department of Intensive Care, Royal Melbourne Hospital, Melbourne, VIC, Australia; Department of Critical Care, The University of Melbourne, Melbourne, VIC, Australia.

Insights
Population-scale frailty screening using the Clinical Frailty Scale (CFS) is feasible in critically ill adults and identifies patients at higher risk for poor outcomes, including mortality. Greater frailty, particularly a CFS score of 6 or higher, is linked to worse results.
Area of Science:
- Critical care medicine
- Geriatric medicine
- Public health
Background:
- Frailty is linked to adverse outcomes in critical illness.
- The feasibility and prognostic value of population-level frailty screening in intensive care units (ICUs) remain unclear.
Purpose of the Study:
- To determine if population-scale frailty screening using the Clinical Frailty Scale (CFS) is feasible for critically ill adults in Australia and New Zealand (ANZ).
- To assess the prognostic importance of frailty in predicting negative outcomes in this population.
Main Methods:
- A binational prospective cohort study was conducted in 175 ICUs across ANZ from July 2018 to June 2020.
- Frailty was assessed using the CFS on ICU admission for 234,568 critically ill adult patients.
- In-hospital mortality, length of stay, discharge destination, and complications were primary and secondary outcomes.
Main Results:
- 19% of patients (45,245) were identified as frail.
- Frail patients had significantly higher in-hospital mortality (16% vs. 5%), delirium rates (10% vs. 4%), and longer ICU/hospital stays compared to non-frail patients.
- Increasing CFS scores correlated with worse outcomes; patients with CFS score 8 had a 39% in-hospital mortality rate versus 2% for CFS score 1.
- Frailty independently predicted mortality, improving the predictive accuracy of the APACHE III-j score.
Conclusions:
- Population-scale frailty screening in critical illness is feasible and prognostically important.
- Higher degrees of frailty, especially CFS scores ≥ 6, are associated with worse outcomes, even in younger patients.
- The CFS is a valuable tool for identifying critically ill patients at risk.
Background:
Frailty is associated with poor outcomes in critical illness. However, it is unclear whether frailty screening on admission to the ICU can be conducted routinely at the population level and whether it has prognostic importance.
Research Question:
Can population-scale frailty screening with the Clinical Frailty Scale (CFS) be implemented for critically ill adults in Australia and New Zealand (ANZ) and can it identify patients at risk of negative outcomes?
Study Design And Methods:
We conducted a binational prospective cohort study of critically ill adult patients admitted between July 1, 2018, and June 30, 2020, in 175 ICUs in ANZ. We classified frailty with the CFS on admission to the ICU. The primary outcome was in-hospital mortality; secondary outcomes were length of stay (LOS), discharge destination, complications (delirium, pressure injury), and duration of survival.
Results:
We included 234,568 critically ill patients; 45,245 (19%) were diagnosed as living with frailty before ICU admission. Patients with vs without frailty had higher in-hospital mortality (16% vs 5%; P < .001), delirium (10% vs 4%; P < .001), longer LOS in the ICU and hospital, and increased new chronic care discharge (3% vs 1%; P < .001), with worse outcomes associated with increasing CFS category. Of patients with very severe frailty (CFS score, 8), 39% died in hospital vs 2% of very fit patients (CFS score, 1; multivariate categorical CFS score, 8 [reference, 1]; OR, 7.83 [95% CI, 6.39-9.59]; P < .001). After adjustment for illness severity, frailty remained highly significantly predictive of mortality, including among patients younger than 50 years, with improvement in the area under the receiver operating characteristic curve of the Acute Physiology and Chronic Health Evaluation III-j score to 0.882 (95% CI, 0.879-0.885) from 0.868 (95% CI, 0.866-0.871) with the addition of frailty (P < .001).
Interpretation:
Large-scale population screening for frailty degree in critical illness was possible and prognostically important, with greater frailty (especially CFS score of ≥ 6) associated with worse outcomes, including among younger patients.


Related Concept Videos
 01:15
Bioavailability Study Design: Healthy Subjects Versus Patients
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion