Related Experiment Video
Updated: Nov 2, 2025

In Vivo, Percutaneous, Needle Based, Optical Coherence Tomography of Renal Masses
Published on: March 30, 2015
Active surveillance in renal tumors: Clinical and oncological outcomes
Alfredo Aguilera Bazan1, Diego M Carrion2, Juan Gomez Rivas1
1Department of Urology, La Paz University Hospital; Universidad Autonoma de Madrid; La Paz University Hospital Institute for Health Research (IdiPAZ), Madrid, Spain.

Context:
Some patients diagnosed with small renal solid masses or complex cystic lesions may benefit from active surveillance (AS) instead of immediate treatment.
Aims:
Report our series of patients undergoing AS for small renal solid and complex cystic lesions, and compare growth rates and outcomes between both types of lesions.
Materials And Methods:
A retrospective review AS database for renal lesions was conducted. From 1995 to 2017, a total of 82 patients with 89 renal lesions were included. We describe our AS protocol, patient and tumor characteristics, comparisons between solid and cystic lesions, and final outcome of patients who underwent delayed intervention (DI).
Statistical Analysis Used:
Categorical and continuous data were analyzed by the Chi-square and the Student's t-test, respectively. The Wilcoxon/Kruskal-Wallis test was used for growth rate comparisons of solid and complex cystic lesions.
Results:
Median age of patients at the beginning of AS was 77-year-old, median size for solid and cystic lesions was 2.3 cm (0.08-3.8) and 2.6 cm (1.2-4.0), respectively. No differences in annual growth rate between solid and complex cystic lesions (0.04 cm [0.00-1.5] and 0.05 cm [0.01-1.7]) were observed at a similar median follow-up of 61 months for both groups (range: 15-182, and 14-254). Five patients with solid lesions underwent DI, 3 for rapid growth (>0.5 cm/year), 1 demanded treatment, and 1 due to hematuria. Adherence to AS protocol was high (94%). No cancer-related deaths or metastatic progression was observed, six patients died of another medical condition, being cardiovascular disease the most frequent cause.
Conclusions:
AS is a reasonable and safe option for the management of small renal masses. No difference was observed in the growth rate between solid and complex cystic lesions during AS. Centers offering AS should present a standardized protocol and give exhaustive information to patients regarding benefits and risks.
More Related Videos
 06:38
A Syngeneic Mouse Model of Metastatic Renal Cell Carcinoma for Quantitative and Longitudinal Assessment of Preclinical Therapies
Published on: April 12, 2017
 12:22
The Use of Reverse Phase Protein Arrays RPPA to Explore Protein Expression Variation within Individual Renal Cell Cancers
Published on: January 22, 2013
Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:06
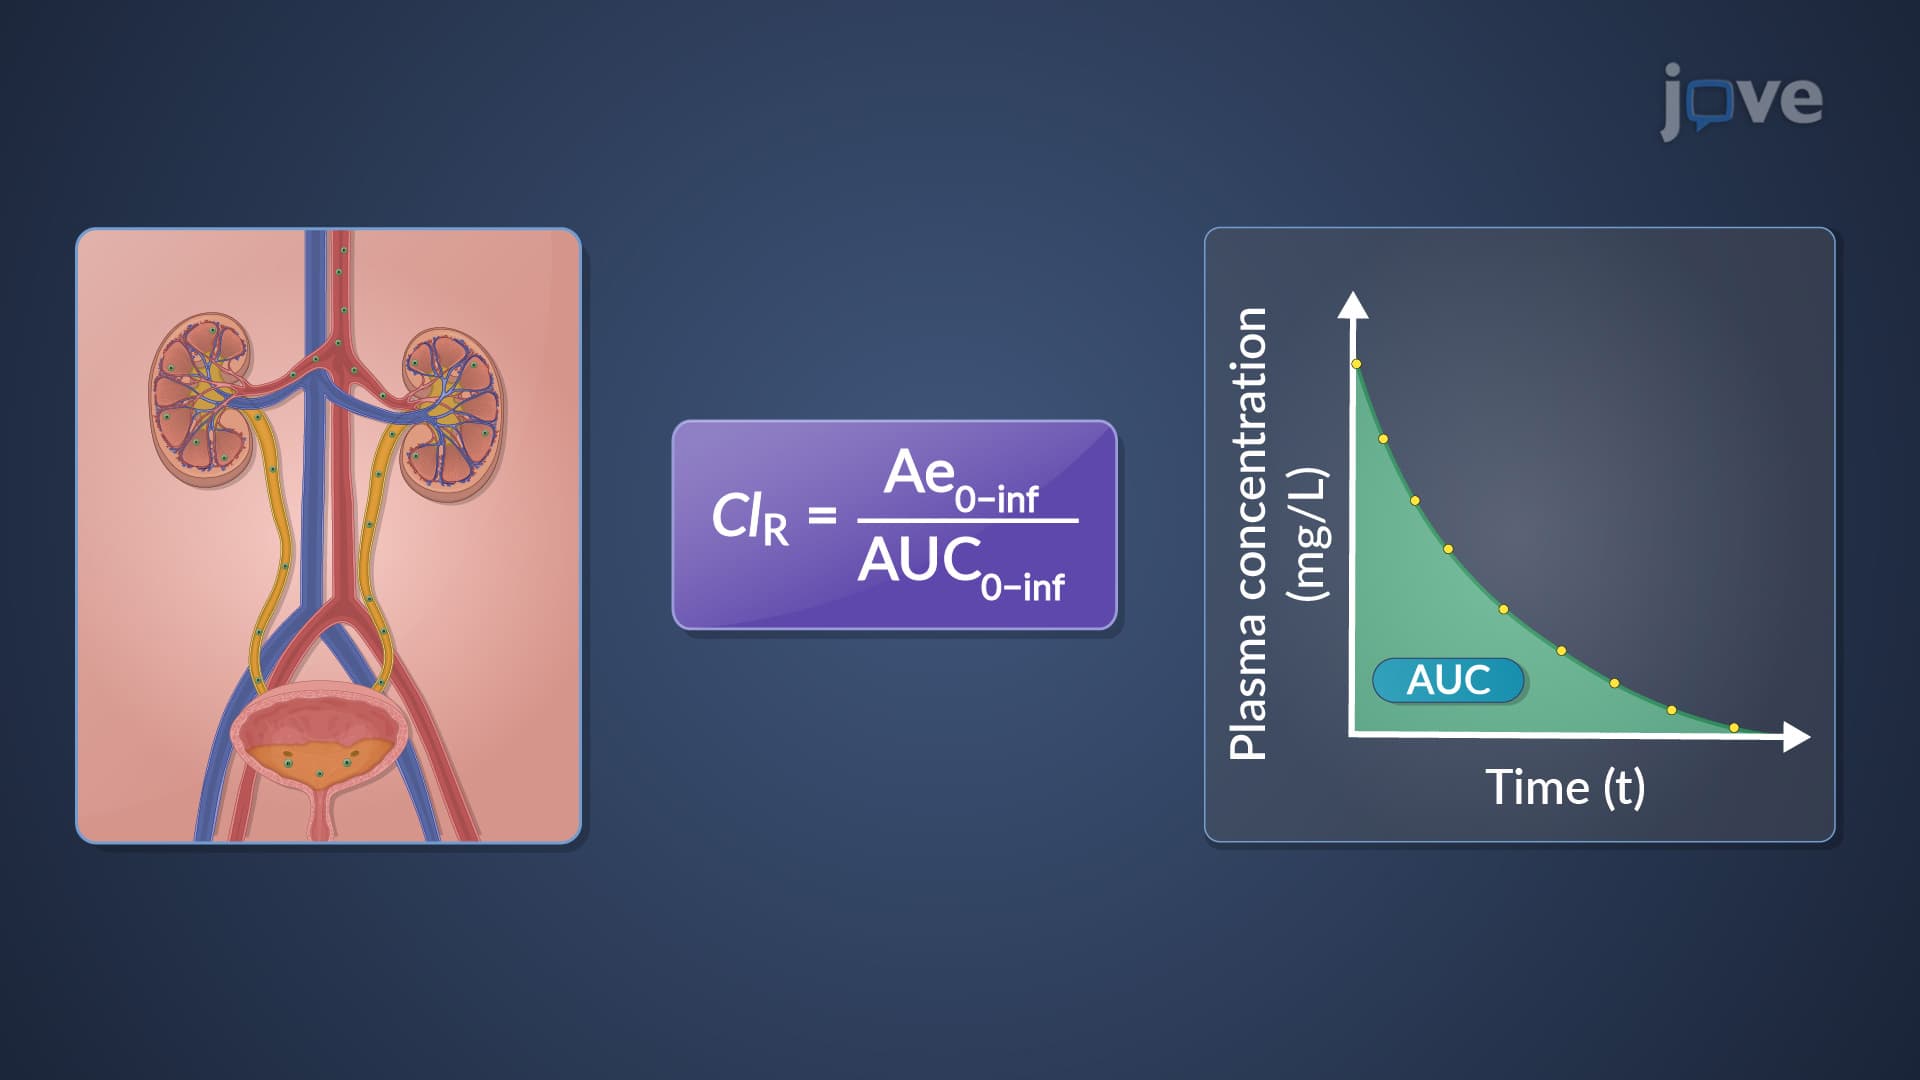
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Imaging Studies I: Kidney, Ureter, and Bladder Studies
 01:24
Imaging Studies II: Ultrasonography
 01:16
Kidney Transplant III: Nursing Management
 01:19
Imaging Studies VII: Vascular Imaging