Related Experiment Video
Updated: Nov 1, 2025
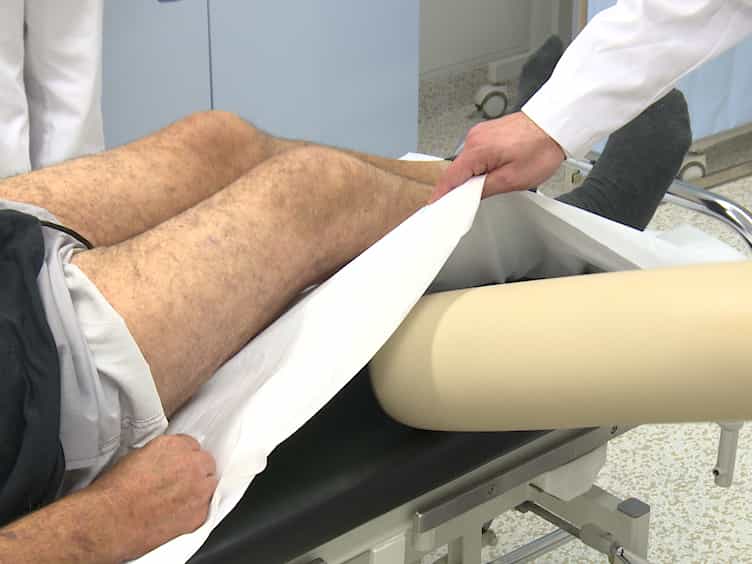
Novel Diagnostics in Revision Arthroplasty: Implant Sonication and Multiplex Polymerase Chain Reaction
Published on: December 3, 2017
Spontaneous HIT syndrome: Knee replacement, infection, and parallels with vaccine-induced immune thrombotic
Theodore E Warkentin1, Andreas Greinacher2
1Department of Pathology and Molecular Medicine, and Department of Medicine, McMaster University, Hamilton, Ontario, Canada; Hamilton Regional Laboratory Medicine Program (Transfusion Medicine), Hamilton, Ontario, Canada; Service of Benign Hematology, Hamilton Health Sciences (Hamilton General Hospital), Canada.

Heparin-induced thrombocytopenia (HIT) is characterized clinically by thrombocytopenia, hypercoagulability, and increased thrombosis risk, and serologically by platelet-activating anti-platelet factor 4 (PF4)/heparin antibodies. Heparin-"induced" acknowledges that HIT is usually triggered by a proximate immunizing exposure to heparin. However, certain non-heparin medications (pentosan polysulfate, hypersulfated chondroitin sulfate, fondaparinux) can trigger "HIT". Further, naturally-occurring polyanions (bacterial lipopolysaccharide, DNA/RNA) can interact with PF4 to recapitulate HIT antigens. Indeed, immunologic presensitization to naturally-occurring polyanions could explain why HIT more closely resembles a secondary, rather than a primary, immune response. In 2008 it was first reported that a HIT-mimicking disorder can occur without any preceding exposure to heparin or polyanionic medications. Termed "spontaneous HIT syndrome", two subtypes are recognized: (a) surgical (post-orthopedic, especially post-total knee arthroplasty, and (b) medical (usually post-infectious). Recently, COVID-19 adenoviral vector vaccination has been associated with a thrombotic thrombocytopenic disorder associated with positive PF4-dependent enzyme-immunoassays and serum-induced platelet activation that is maximal when PF4 is added. Vaccine-induced immune thrombotic thrombocytopenia (VITT) features unusual thromboses (cerebral venous thrombosis, splanchnic vein thrombosis) similar to those seen in spontaneous HIT syndrome. The emerging concept is that classic HIT reflects platelet-activating anti-PF4/heparin antibodies whereas spontaneous HIT syndrome and other atypical "autoimmune HIT" presentations (delayed-onset HIT, persisting HIT, heparin "flush" HIT) reflect heparin-independent platelet-activating anti-PF4 antibodies-although the precise relationships between PF4 epitope targets and the clinical syndromes remain to be determined. Treatment of spontaneous HIT syndrome includes non-heparin anticoagulation (direct oral Xa inhibitors favored over direct thrombin inhibitors) and high-dose immunoglobulin.
Heparin-induced thrombocytopenia (HIT) is characterized clinically by thrombocytopenia, hypercoagulability, and increased thrombosis risk, and serologically by platelet-activating anti-platelet factor 4 (PF4)/heparin antibodies. Heparin-"induced" acknowledges that HIT is usually triggered by a proximate immunizing exposure to heparin. However, certain non-heparin medications (pentosan polysulfate, hypersulfated chondroitin sulfate, fondaparinux) can trigger "HIT". Further, naturally-occurring polyanions (bacterial lipopolysaccharide, DNA/RNA) can interact with PF4 to recapitulate HIT antigens. Indeed, immunologic presensitization to naturally-occurring polyanions could explain why HIT more closely resembles a secondary, rather than a primary, immune response. In 2008 it was first reported that a HIT-mimicking disorder can occur without any preceding exposure to heparin or polyanionic medications. Termed "spontaneous HIT syndrome", two subtypes are recognized: (a) surgical (post-orthopedic, especially post-total knee arthroplasty, and (b) medical (usually post-infectious). Recently, COVID-19 adenoviral vector vaccination has been associated with a thrombotic thrombocytopenic disorder associated with positive PF4-dependent enzyme-immunoassays and serum-induced platelet activation that is maximal when PF4 is added. Vaccine-induced immune thrombotic thrombocytopenia (VITT) features unusual thromboses (cerebral venous thrombosis, splanchnic vein thrombosis) similar to those seen in spontaneous HIT syndrome. The emerging concept is that classic HIT reflects platelet-activating anti-PF4/heparin antibodies whereas spontaneous HIT syndrome and other atypical "autoimmune HIT" presentations (delayed-onset HIT, persisting HIT, heparin "flush" HIT) reflect heparin-independent platelet-activating anti-PF4 antibodies-although the precise relationships between PF4 epitope targets and the clinical syndromes remain to be determined. Treatment of spontaneous HIT syndrome includes non-heparin anticoagulation (direct oral Xa inhibitors favored over direct thrombin inhibitors) and high-dose immunoglobulin.
Related Concept Videos
 01:25
Endocarditis I: Introduction
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:29
Venous Thrombosis III: Interprofessional Care
 01:23
Rheumatic Heart Disease I: Introduction
 01:30
Venous Thrombosis I: Introduction
 01:29
Immune Response Against Viral Pathogens
NK Cells
NK cells are a crucial part of our innate immune system, acting as the first line of defense against viral infections. These cells can recognize and kill infected cells without prior exposure to the virus, effectively slowing down the spread of infection. Additionally, NK cells produce proinflammatory...