Related Experiment Video
Updated: Aug 19, 2026
Visualization of Vascular and Parenchymal Regeneration after 70% Partial Hepatectomy in Normal Mice
Published on: September 13, 2016
Simulation of portal/hepatic vein associated remnant liver ischemia/congestion by three-dimensional visualization
Xiao-Long Li1,2, Bin Xu1,2, Xiao-Dong Zhu1,2
1Department of Liver Surgery and Transplantation, Liver Cancer Institute, Zhongshan Hospital, Fudan University, Shanghai, China.

Background:
Remnant liver hypoperfusion is frequently observed after hepatectomy, and associated with a higher risk of postoperative complications and poorer survival. However, the development of remnant liver hypoperfusion was not fully understood.
Methods:
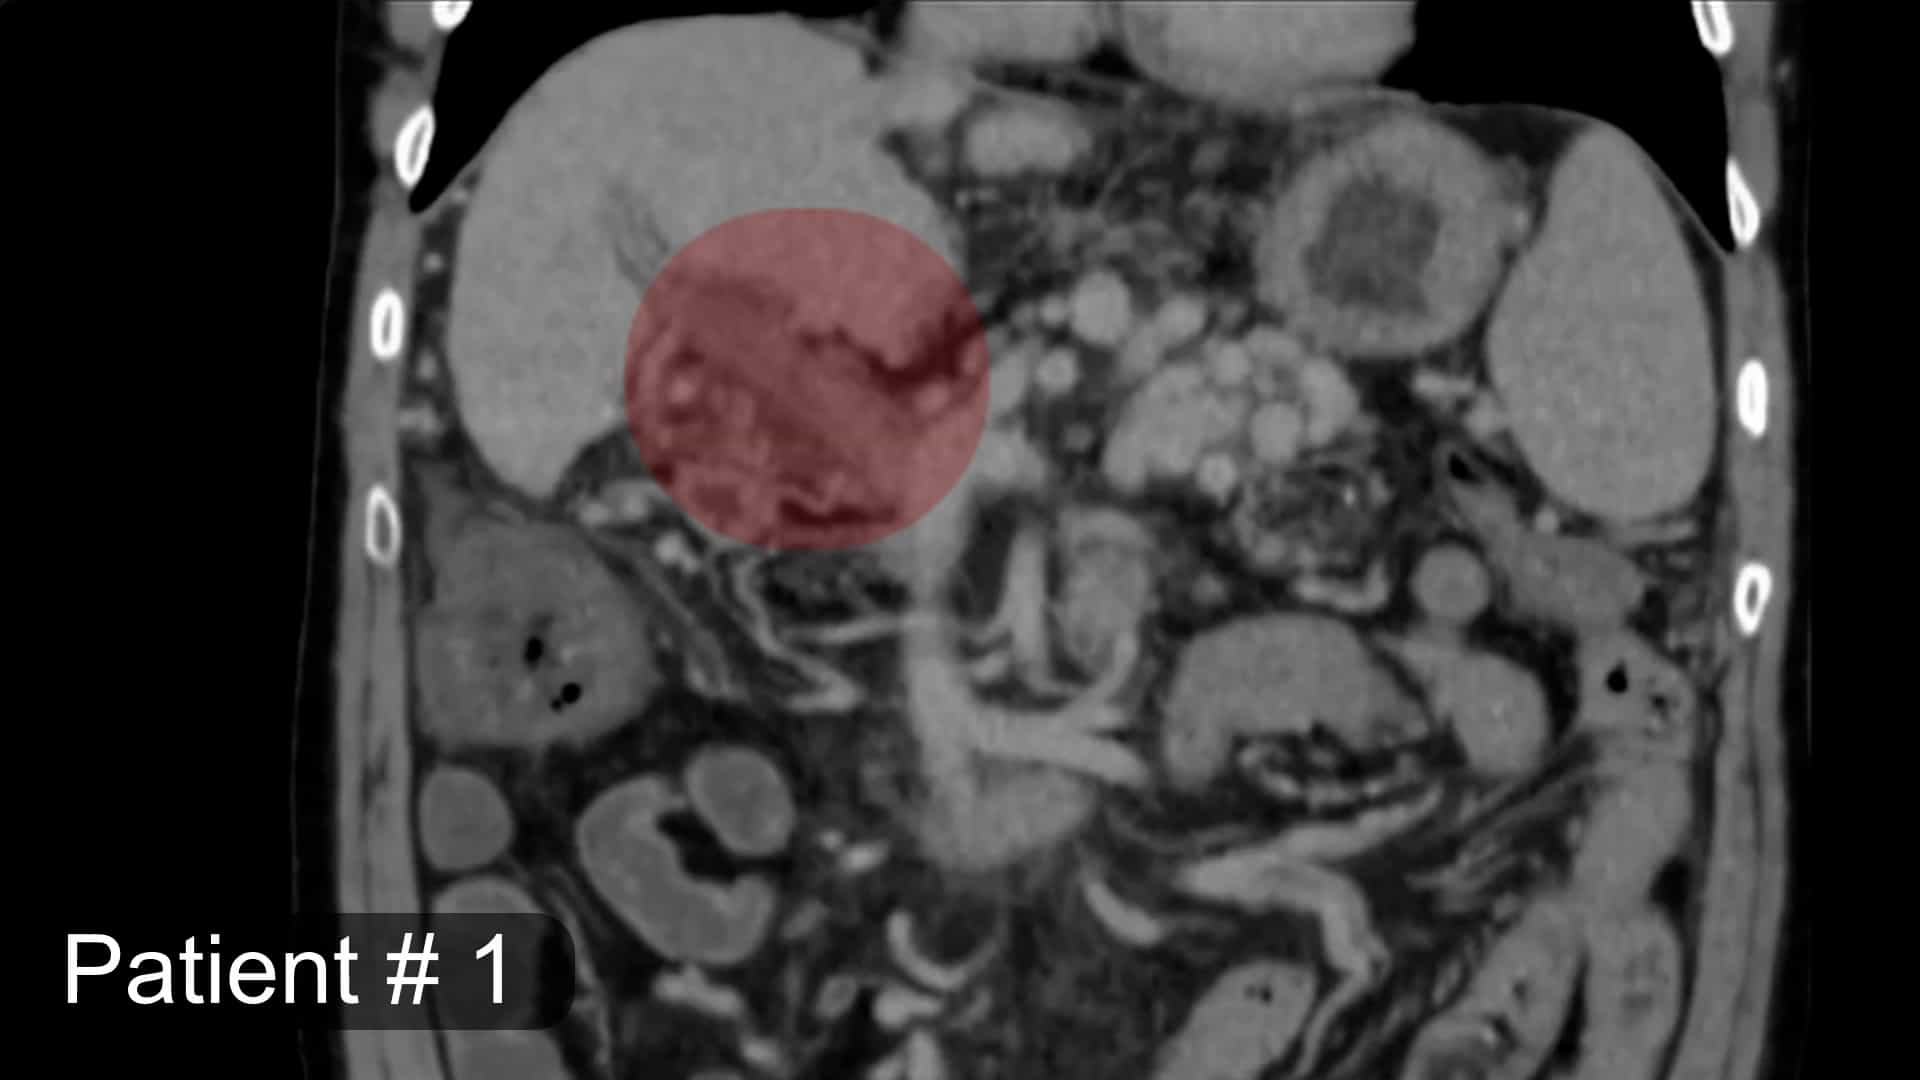
We retrospectively analyzed patients who received hepatectomy and took contrast-enhanced computed tomography (CT) scans before, 1-week (POW1) and 4-week (POW4) after resection in our department from June 2017 to July 2019. We simulated and estimated the occurrence of portal-vein-related remnant liver ischemia (RLI) and hepatic-vein-related remnant liver congestion (RLC) after hepatectomy via three-dimensional visualization technology (3DVT) according to blood vessels ligated in the resection; then we analyzed association between the estimated RLI, RLC, and postoperative clinical outcomes.
Results:
A total of 102 eligible patients were analyzed. Remnant liver hypoperfusion was observed in 47 (46%) patients in the POW1 CT scans and shrunk in the POW4 CT scans. RLC had better diagnostic significance than RLI in predicting remnant liver hypoperfusion [area under receiver operating characteristic (ROC) curve: 0.745 vs. 0.569, P=0.026]. Multivariate analysis showed that larger RLI [odds ratio (OR), 1.154; 95% confidence interval (CI), 1.075-1.240; P<0.001] was independent risk factor for post-hepatectomy liver failure (PHLF). Besides, larger RLC (OR, 1.114; 95% CI, 1.032-1.204; P=0.006) was independent risk factor for major postoperative complications.
Conclusions:
Remnant liver hypoperfusion can be predicted during the preoperative surgical plan by 3DVT. Portal vein related RLI was associated with PHLF, and hepatic vein related RLC was associated with major postoperative complications. Preservation of the hepatic vein and complete removal of the perfusion territory of ligated vessels are essential procedures to reduce RLI/RLC and the risk of PHLF or other surgical complications.