Related Experiment Video
Updated: Oct 27, 2025


A Method of Trigonometric Modelling of Seasonal Variation Demonstrated with Multiple Sclerosis Relapse Data
Published on: December 9, 2015
The GOUT-36 prediction rule for inpatient gout flare in people with comorbid gout: derivation and external validation
Kanon Jatuworapruk1,2, Rebecca Grainger1, Nicola Dalbeth3
1Department of Medicine, University of Otago, Wellington, New Zealand.

Insights
A new GOUT-36 rule helps identify hospitalized gout patients at high risk for flares. This simple tool aids clinical decisions for preventing inpatient gout flares.
Area of Science:
- Rheumatology
- Clinical Medicine
- Epidemiology
Background:
- Gout flares can occur in hospitalized patients with non-gout conditions.
- Effective risk stratification for inpatient gout flares is needed.
Purpose of the Study:
- To develop and validate a risk stratification tool for inpatient gout flares.
- To identify patients with gout at high risk for developing flares during hospitalization.
Main Methods:
- A prediction rule (GOUT-36) was derived from 625 hospitalized gout patients in New Zealand.
- The rule includes four factors: no pre-admission prophylaxis, no urate-lowering therapy, tophus, and high serum urate.
- Validation was performed in 284 hospitalized gout patients from Thailand and China.
Main Results:
- The GOUT-36 rule demonstrated 75% sensitivity and 67% specificity for high-risk classification.
- An area under the curve of 0.71 indicated good discriminative ability.
- In a population with 34% overall flare rate, very high-risk patients (3-4 items) had an 80% flare rate, versus 11% in low-risk patients (0 items).
Conclusions:
- The GOUT-36 rule is a simple and sensitive tool for identifying high-risk patients for inpatient gout flares.
- This rule can assist in clinical decision-making and guide future research on flare prevention.
Objectives:
To develop and validate a gout flare risk stratification tool for people with gout hospitalized for non-gout conditions.
Methods:
The prediction rule for inpatient gout flare was derived from a cohort of 625 hospitalized people with comorbid gout from New Zealand. The rule had four items: no pre-admission gout flare prophylaxis, no pre-admission urate-lowering therapy, tophus and pre-admission serum urate >0.36 mmol/l within the previous year (GOUT-36 rule). Two or more items are required for the classification of high risk for developing inpatient gout flares. The GOUT-36 rule was validated in a prospective cohort of 284 hospitalized people with comorbid gout from Thailand and China.
Results:
The GOUT-36 rule had a sensitivity of 75%, specificity of 67% and area under the curve of 0.71 for classifying people at high risk for developing inpatient gout flares. Four risk groups were developed: low (no items), moderate (one item), high (two items) and very high risk (three or four items). In a population with frequent (overall 34%) in-hospital gout flares, 80% of people with very high risk developed inpatient flares while 11% with low risk had inpatient flares.
Conclusion:
The GOUT-36 rule is simple and sensitive for classifying people with high risk for inpatient gout flares. The rule may help inform clinical decisions and future research on the prevention of inpatient gout flares.
More Related Videos
 02:15
Predictive Measurement for Windlass Change in Length and Selected Treatment Outcomes in Chronic Plantar Fasciitis
Published on: March 1, 2024
 06:55
Inverse Probability of Treatment Weighting Propensity Score using the Military Health System Data Repository and National Death Index
Published on: January 8, 2020
Related Concept Videos
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:02
Quantifying and Rejecting Outliers: The Grubbs Test
 01:30
Urinary Tract Calculi III: Medical Management
 01:11
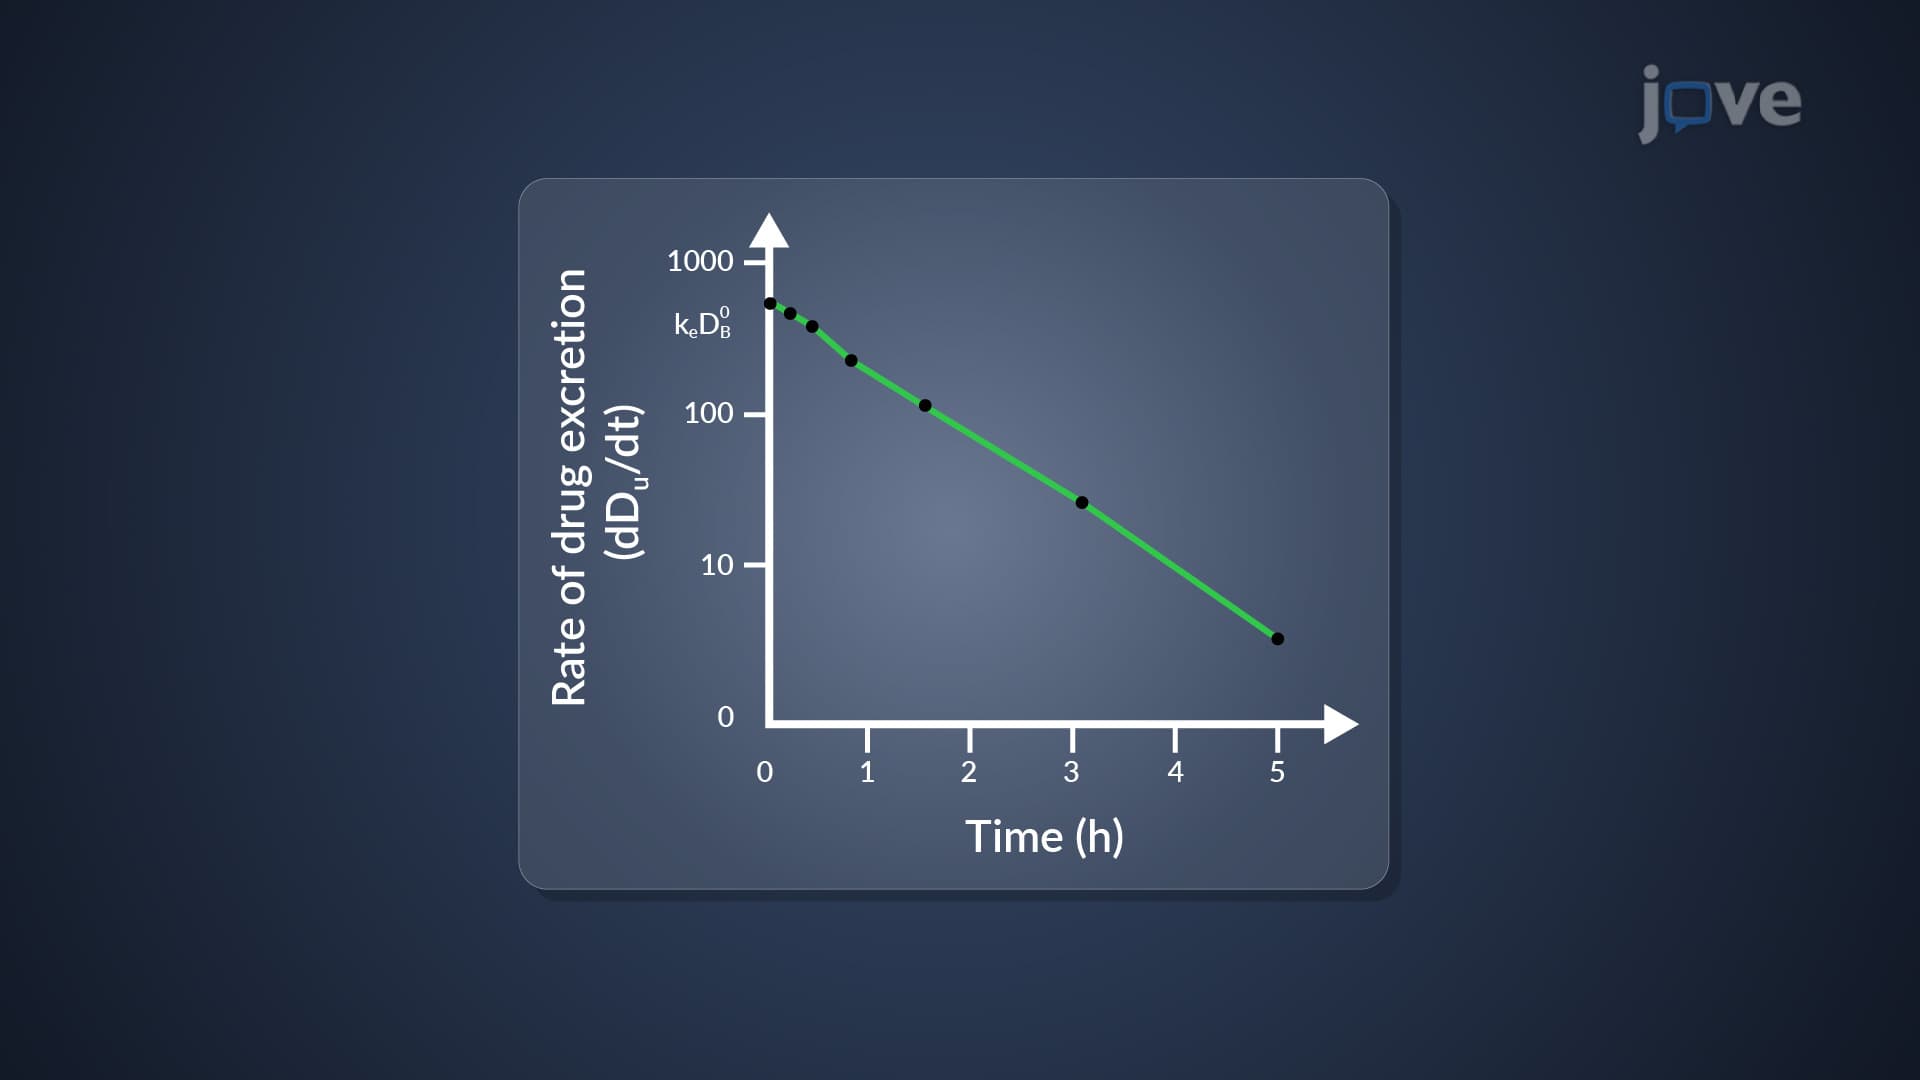
One-Compartment Open Model: Urinary Excretion Data and Determination of k
 01:23
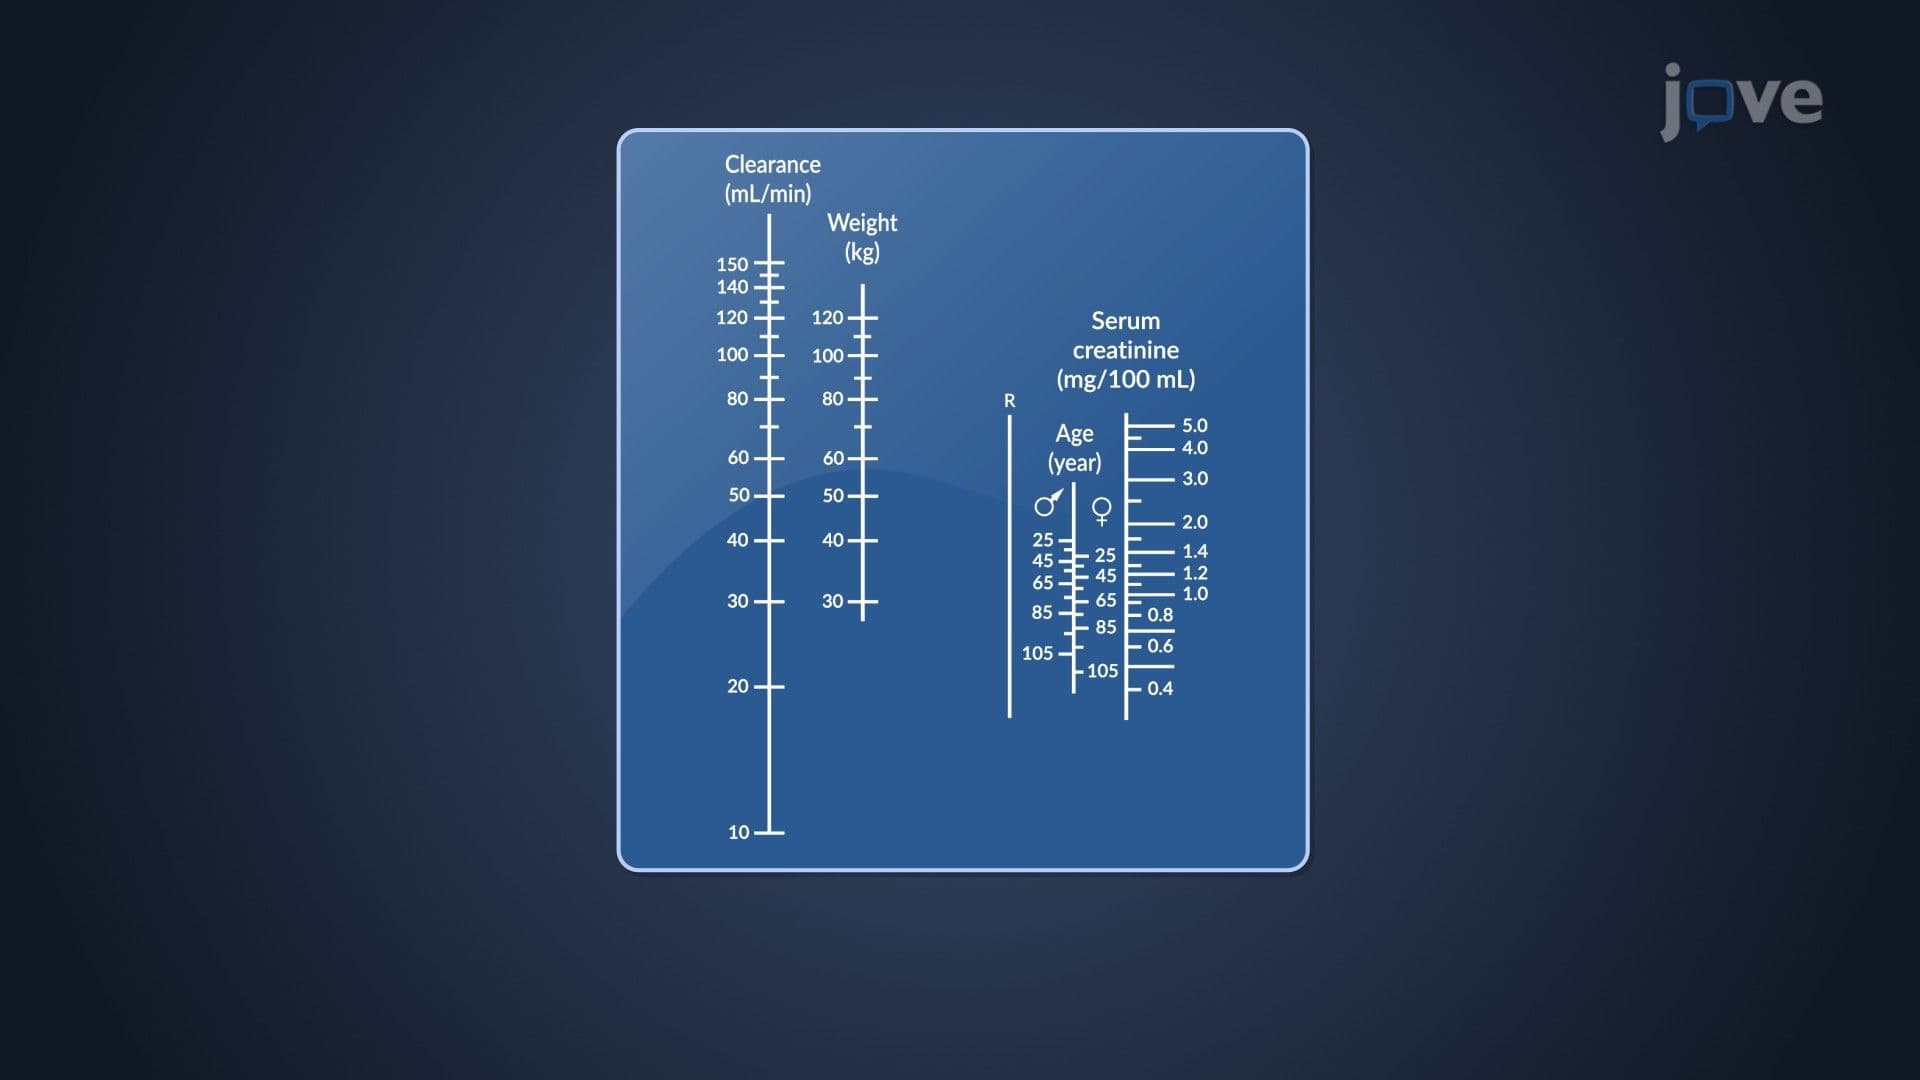
Dosage Regimen Designs: Nomograms and Tabulations
 01:03
Prediction Intervals
However, the point estimate is most likely not the exact value of the population parameter, but close to it. After calculating point estimates, we construct interval estimates, called confidence intervals or prediction intervals. This prediction interval comprises a range of values unlike the point estimate and is a better predictor of the observed sample value, y.