Related Experiment Video
Updated: Oct 24, 2025


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Understanding sagittal compensation in adult spinal deformity patients: relationship between pelvic tilt and
Takayoshi Shimizu1,2, Meghan Cerpa1, Lawrence G Lenke1
11Department of Orthopaedic Surgery, Columbia University Medical Center, Och Spine Hospital at NewYork-Presbyterian, New York, New York; and.

Objective:
In adult spinal deformity (ASD), quantifying preoperative lower-extremity (LE) compensation is important in formulating an operative plan to achieve optimal global sagittal alignment. Whole-body radiographs are not always available. This study evaluated the possibility of estimating LE compensation without whole-body radiographs.
Methods:
In total, 200 consecutive ASD patients with full-body radiographic assessment were categorized into the following three groups according to their cranio-hip balance (distance from the cranial sagittal vertical axis to the hip axis [CrSVA-H]): group 1, anterior-shift (A-shift) group (CrSVA-H > 40 mm); group 2, balanced group, -40 mm < CrSVA-H < 40 mm; and group 3, posterior-shift (P-shift) group, CrSVA-H < -40 mm. After analyzing the correlation between CrSVA-H, pelvic tilt (PT), and LE parameters, the cutoff PT and PT/pelvic incidence (PI) values that correlated with the presence of LE compensation were determined. Previously published data from asymptomatic volunteers were used as a baseline threshold (sacrofemoral angle [SFA] > 217.0° and knee flexion angle [KA] > 11.0°).
Results:
Among the hip, knee, and ankle, only KA showed a significant increase in the A-shift group compared to the other two groups (p < 0.01). With a wide threshold (SFA > 208.0° and KA > 5.0°), 84.9% of the A-shift group showed LE compensation (hip or knee or both), which was a significantly greater percentage than those in the balanced and P-shift groups (48.4% and 51.9%, p < 0.01). With a narrow threshold (SFA > 217.0° and KA > 11.0°), 62.2% of the A-shift group showed any LE compensation, which was also a higher percentage than the other two groups. The CrSVA-H was moderately correlated with KA (r = 0.502), but had no correlation with PT, SFA, and ankle dorsiflexion angle (AA). PT showed a moderate/strong correlation with SFA, KA, and AA (r = 0.846, 0.624, and 0.622, respectively). With receiver operating characteristic curves, the authors determined that a 23.0° PT with PT/PI > 0.46 predicts the presence of any type of LE compensation with use of the wide threshold.
Conclusions:
ASD patients with increased CrSVA-H, which represents cranio-hip anterior imbalance, demonstrated a higher prevalence of LE compensation, especially knee flexion, compared to those with neutral and posterior shift of CrSVA. PT represents the extent of LE compensation in patients with spinal sagittal malalignment. Using the cutoff value of PT determined in this study, surgeons can preoperatively estimate the extent of LE compensation without obtaining a full-body radiograph.
More Related Videos
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:16
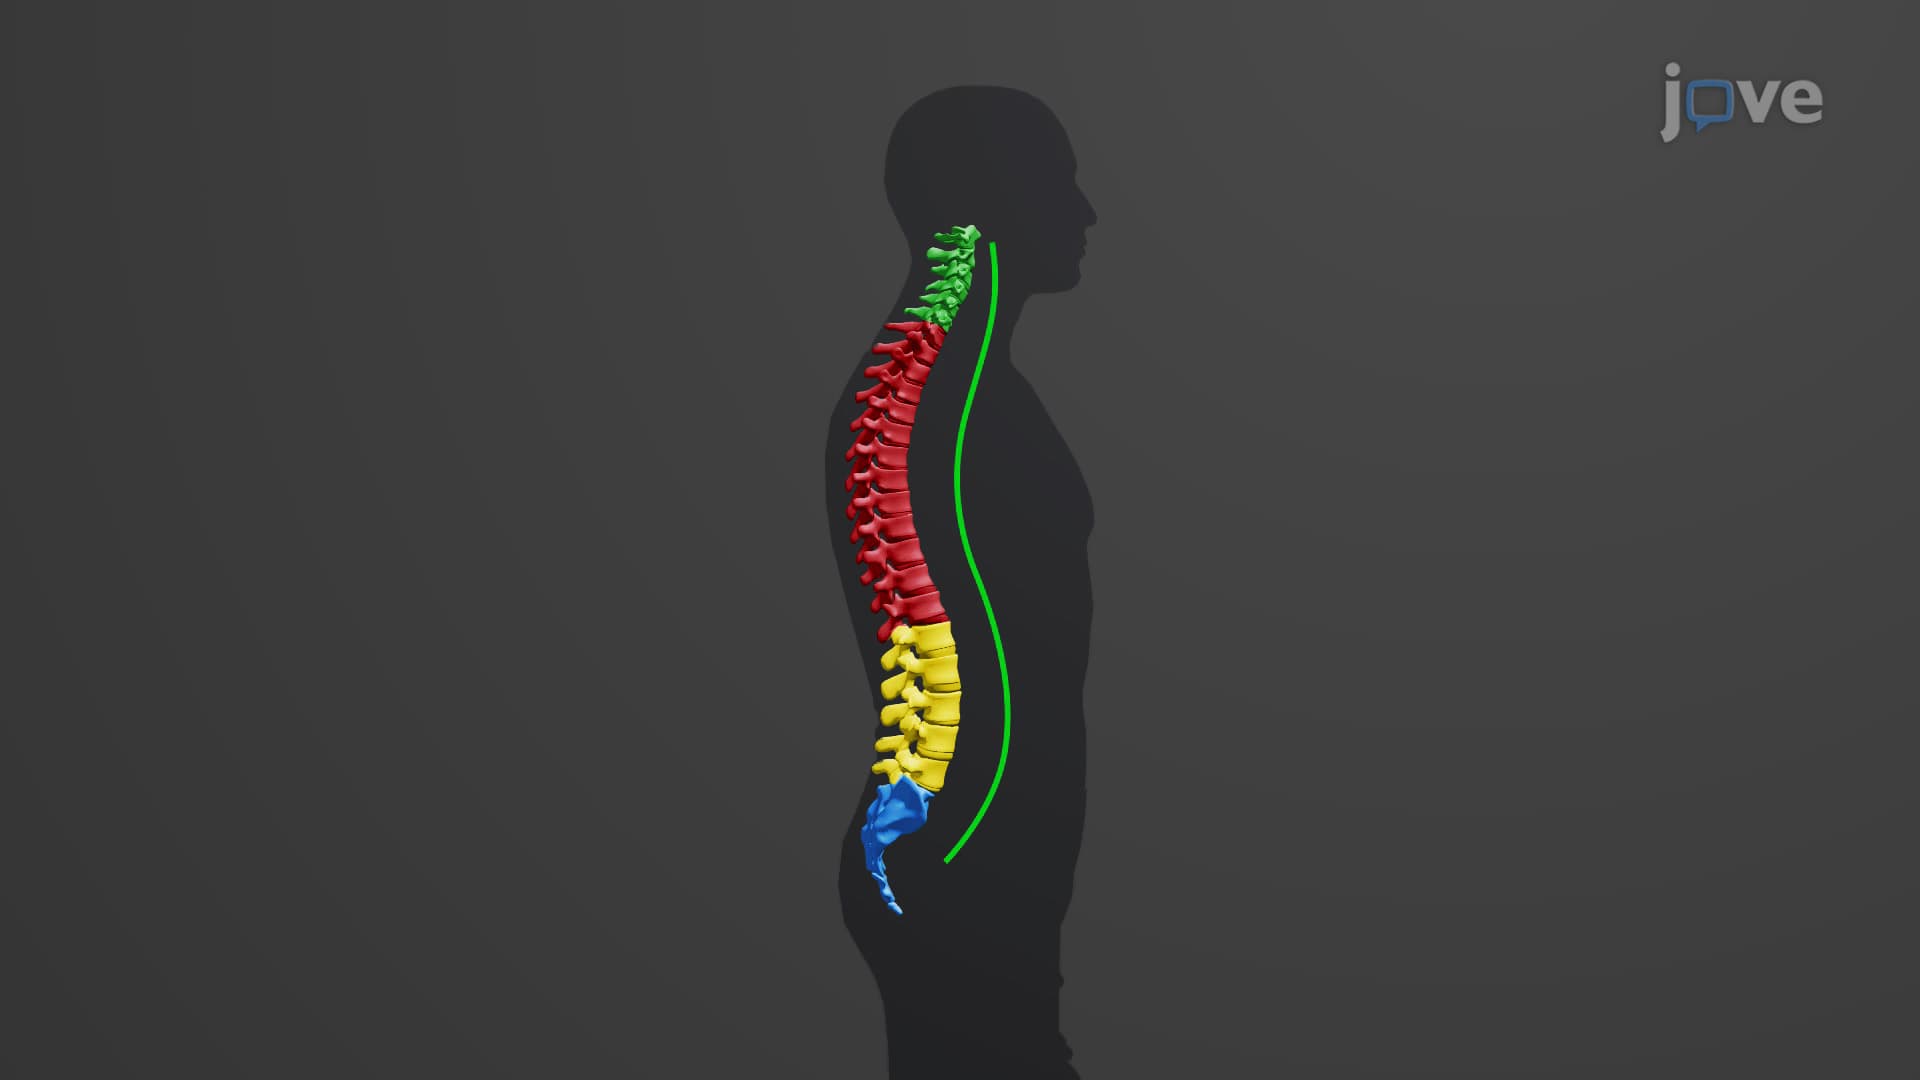
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...