Related Experiment Video
Updated: Oct 18, 2026
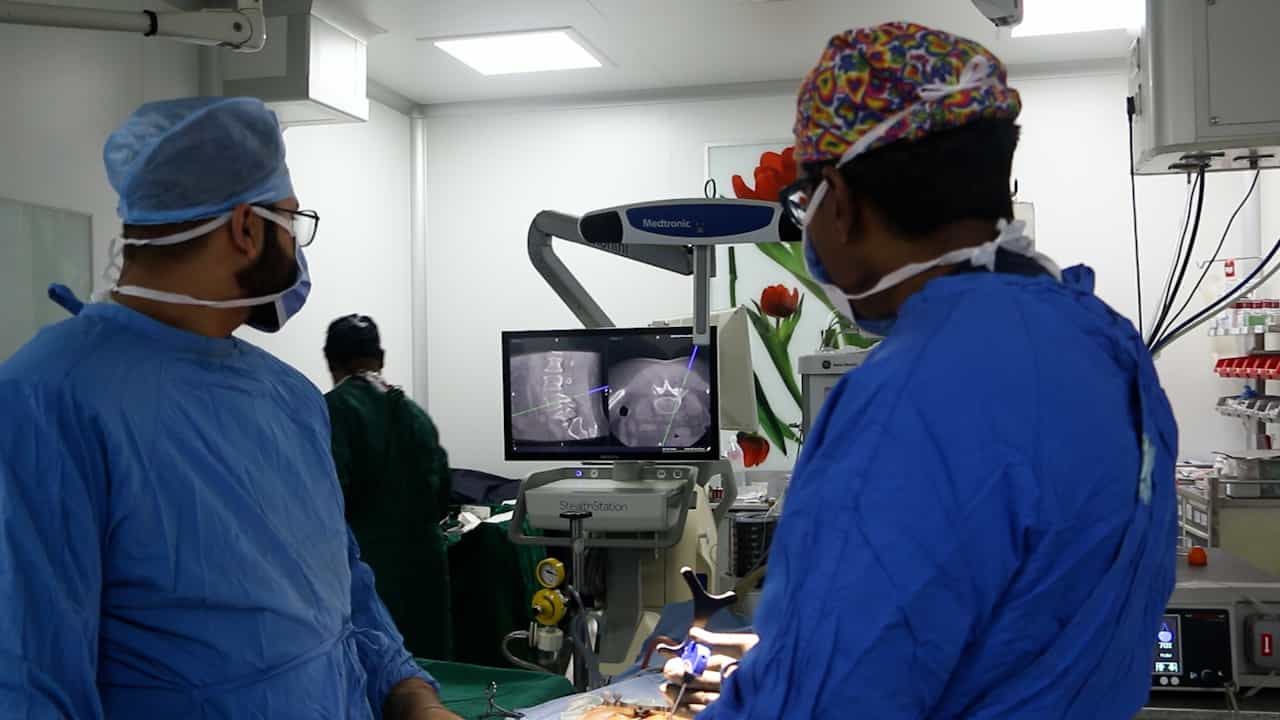
Optimizing Minimally Invasive Spine Surgery: A Fully 3D CT O-Arm Navigated Workflow in MIS TLIF
Published on: October 17, 2025
Mind the gap: discrepancies between planned and achieved screw trajectories in 3D-navigated spine surgery
Ulf Bertram1, Laure Weis1, Tobias P Schmidt1
11Department of Neurosurgery, RWTH Aachen University, Medical Center, Aachen.

Objective:
Intraoperative 3D image-guided navigation has improved the accuracy of posterior screw placement in spine surgery. However, discrepancies between planned and achieved screw trajectories remain underexplored. In this study, authors assessed these deviations across spinal regions and their potential correlation with screw misplacement.
Methods:
They prospectively analyzed patients undergoing posterior instrumented fusion surgery between 2021 and 2023. Screw placement accuracy was graded using the 2-mm increment basis of the Gertzbein and Robbins (GR) classification. Additionally, angulation discrepancies between planned and achieved trajectories were measured in the axial and sagittal planes. Statistical analyses included Kruskal-Wallis, Dunn's post hoc, and Spearman correlation tests.
Results:
The study included 725 pedicle and lateral mass screw trajectories in 121 patients. Overall, 95.0% of screws were placed with acceptable accuracy (cervical spine: GR grade A and B; all other spine regions: GR grade A-C). Axial screw trajectory divergence was highest in the subaxial cervical spine (4.2° ± 3.0°), significantly exceeding those in the atlantoaxial (2.6° ± 2.1°), thoracic (2.6° ± 2.2°), and lumbar (2.9° ± 3.2°) regions (p < 0.01). Sagittal divergence was greater in the subaxial cervical spine (4.1° ± 4.0°) than in the thoracic spine (2.8° ± 2.7°; p < 0.001). The correlation between trajectory deviations and screw misplacement was weak or absent.
Conclusions:
Screw trajectory deviations vary by spinal region, with the greatest axial discrepancies observed in the subaxial cervical spine. These findings highlight the importance of recognizing intraoperative navigation limitations and refining surgical techniques to optimize accuracy. Monitoring screw trajectories may enhance training and improve patient safety.